

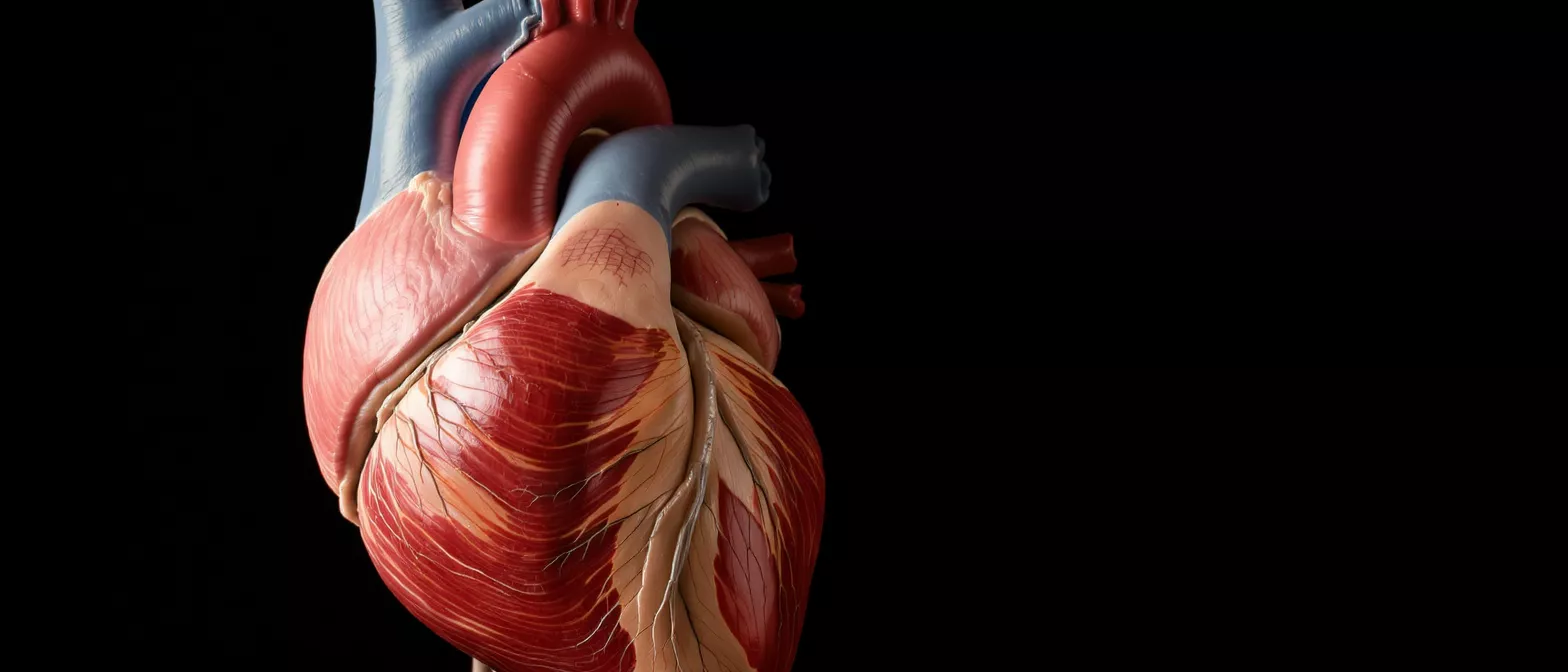
Left Ventricle
Discover how the left ventricle powers blood flow, its anatomy, common conditions like hypertrophy, and surgical options.
What is the left ventricle?
The left ventricle is one of the four main chambers of the human heart, specifically serving as the heart's primary and most muscular pumping chamber. When medical professionals discuss the heart's overall pumping efficiency, they are almost always referring directly to the performance of this specific chamber. It sits in the lower left portion of the heart and plays a foundational role in maintaining continuous blood circulation throughout your entire body. For patients facing cardiac surgery, understanding the basic anatomy of this chamber helps clarify why certain surgical interventions are required.
Why the left ventricle matters for heart surgery patients: Because this chamber is responsible for pushing oxygen-rich blood out to your entire body, any structural or functional issue here has immediate, whole-body consequences. Surgeons must meticulously evaluate the size, thickness, and pumping power of this chamber before proceeding with operations like valve repair or coronary bypass. Damage or stress to the left ventricle often dictates the complexity of the surgical plan, the duration of the operation, and the specific post-operative care protocols a patient will require.
Cardiac anatomy can seem overwhelming at first glance, but breaking it down into its core functions reveals a highly logical system. The left ventricle is essentially the grand central station of healthy circulation, receiving purified blood from the left atrium and forcefully ejecting it into the aorta. From there, the blood branches out to nourish every organ and tissue. Recognizing its central role allows patients and their families to better understand the specific mechanical challenges their surgical team is working to resolve.
What does the left ventricle do?
The primary function of the left ventricle is to receive oxygenated blood returning from the lungs and pump it with sufficient force to reach the furthest extremities of the body. Every time you feel your pulse, that distinct thump is the left ventricle contracting to push a fresh wave of blood into your arteries. This action requires immense pressure, which is why the walls of this specific chamber are significantly thicker than those of any other heart chamber. It must overcome the resistance of the entire systemic circulation to ensure vital organs receive continuous nourishment.
How left ventricle pumping changes during cardiac events: When the heart is under severe stress from blockages or valve disease, the left ventricle must work overtime to maintain adequate blood flow. If the muscle lacks sufficient oxygen itself, or if it has to push against a severely narrowed valve, its pumping efficiency drops drastically. This failure to maintain proper pressure and flow is what ultimately leads to symptoms like extreme fatigue, shortness of breath, and fluid retention, signaling that surgical intervention may be needed to restore normal hemodynamics.
Ensuring robust circulation is the ultimate goal of left ventricle pumping, and the chamber adapts its force based on the body's immediate physiological needs. During physical exertion or periods of high stress, it contracts more vigorously and frequently to supply muscles with extra oxygen. If this adaptive mechanism is compromised by structural heart disease, a patient may experience exercise intolerance or chest pain. Surgeons aim to restore this vital chamber's ability to flexibly and powerfully manage the body's varying blood flow demands.
Left ventricle anatomy and structure
The structural anatomy of the left ventricle is specifically engineered for high-pressure output, featuring thick, muscular walls known as the myocardium. This dense muscle tissue wraps around the chamber in a complex spiral pattern, allowing the heart to wring the blood out with a powerful, twisting motion during each heartbeat. The inner lining, called the endocardium, provides a smooth, frictionless surface that prevents blood from clotting as it rushes through the chamber. This precise anatomical architecture is essential for maintaining unimpeded flow.
Key anatomical boundaries of the left ventricle: The chamber connects to the left atrium via the mitral valve, which acts as a one-way door ensuring blood only moves forward into the ventricle. From there, blood exits through the aortic valve, which prevents blood from leaking backward into the heart between beats. The structural integrity of these connecting valves is directly tied to the function of the left ventricle; when a valve fails, the pumping chamber often dilates or thickens in response to the abnormal fluid dynamics.
Understanding this anatomy helps patients grasp why structural defects are so disruptive to cardiac function. If the muscular walls become too thick or rigid, the chamber cannot expand fully to fill with blood. If the walls become too thin or stretched due to dilation, the muscle loses its ability to contract with the necessary force. Cardiac surgeons meticulously assess this structural geometry, sometimes requiring the implantation of a biventricular pacemaker to resynchronize the left and right pumping chambers, ensuring the anatomical structure works in optimal harmony.
Left ventricle vs right ventricle
When comparing the left ventricle vs right ventricle, the most critical difference lies in the workload each chamber manages and the resulting structural adaptations. The right ventricle is responsible for pumping oxygen-depleted blood to the lungs, a journey that requires relatively low pressure because the lungs are delicate structures located very close to the heart. Consequently, the muscular walls of the right ventricle are thinner and more compliant, designed for volume management rather than high-pressure ejection.
Differences in wall thickness and pressure: The left ventricle, by contrast, must generate substantial pressure to push blood through the extensive, high-resistance network of the systemic circulation. This demand creates a massive disparity in wall thickness between the two lower chambers; the left ventricular myocardium is typically three times thicker than that of the right. This structural contrast is immediately visible on an echocardiogram and serves as a vital diagnostic marker for cardiologists evaluating heart health.
Comparing the left ventricle heart structure to the right reveals a masterful biological design where form perfectly follows function. While the right side manages the pulmonary loop, gently moving blood to the nearby lungs, the left side manages the entire systemic loop, forcefully driving blood from the brain down to the toes. When one side of this delicate balance fails, it often impacts the other, which is why comprehensive cardiac evaluations always assess the structural harmony and interdependence of both major pumping chambers.
What is left ventricular ejection fraction?
Left ventricular ejection fraction, commonly referred to as LVEF or simply EF, is a crucial medical measurement that indicates the percentage of blood the left ventricle pumps out with each contraction. Under normal, healthy circumstances, the ventricle does not empty completely; it pushes out roughly half to two-thirds of the blood it contains. An EF of 50% to 70% is generally considered normal, meaning the heart is squeezing efficiently and delivering an adequate supply of oxygenated blood to the body.
What low ejection fraction means for your heart: When the ejection fraction drops below 40%, it typically indicates that the left ventricle is weakened and struggling to pump forcefully, a condition often associated with heart failure. A lower EF number means less blood is reaching the body's organs with each beat, leading to symptoms of profound fatigue and weakness. For surgeons, a patient's EF is a vital preoperative metric used to gauge surgical risk and determine the most appropriate intervention to protect the remaining heart muscle.
Monitoring this metric is essential for both diagnosis and long-term cardiac care. Doctors track the ejection fraction closely using non-invasive imaging techniques to see if medications or surgical procedures are successfully restoring the heart's strength. If the left ventricle function is severely impaired, cardiologists may prescribe a tailored medication regimen or recommend the placement of an implantable cardioverter defibrillator to guard against dangerous, sudden arrhythmias caused by the weakened muscle tissue.
Common left ventricle conditions
Several structural and functional conditions can adversely affect the left ventricle, often requiring careful medical or surgical management to prevent long-term complications. Among the most common left ventricle conditions are left ventricular hypertrophy, which is an abnormal thickening of the heart muscle, and left ventricular dilation, where the chamber becomes overly enlarged and stretched. Both conditions significantly impair the heart's ability to pump efficiently and can arise from a variety of underlying cardiovascular diseases.
Recognizing symptoms of left ventricle failure: Patients experiencing left ventricle failure often notice a distinct pattern of symptoms, primarily extreme shortness of breath during physical activity or when lying flat. Other indicators include persistent swelling in the legs and ankles due to fluid backing up, chronic fatigue, and a reduced ability to tolerate exercise. Because these symptoms develop as the pumping chamber loses its forward force, they signal that blood is pooling in the lungs and peripheral tissues instead of circulating properly.
When assessing the overall health of the cardiac muscle, clinical evaluations are necessary to differentiate between structural thickening and functional weakening. The specific type of left ventricle condition a patient develops heavily influences their treatment pathway, ranging from daily medication management to complex surgical reconstruction. Understanding these distinctions helps patients comprehend why their cardiologist or surgeon recommends a specific diagnostic or therapeutic strategy over another.
- Left ventricular hypertrophy: Abnormal thickening of the muscle walls, often triggered by chronic high blood pressure.
- Left ventricular dilation: Enlargement and stretching of the chamber, frequently caused by valve leakage or prior heart attacks.
- Heart failure with reduced EF: A pumping weakness where the ejection fraction falls dangerously below normal limits.
Left ventricular hypertrophy causes
The primary causes of left ventricular hypertrophy center around chronic conditions that force the heart muscle to work harder than normal over an extended period. The most prevalent culprit is uncontrolled high blood pressure, or hypertension, which creates constant, elevated resistance in the arteries that the left ventricle must continuously push against. Just as lifting heavy weights causes skeletal muscles to grow larger, pumping against high arterial pressure causes the cardiac muscle fibers to thicken and enlarge.
How valve disease affects left ventricular size: Beyond hypertension, structural valve defects are a major driver of ventricular changes. In aortic stenosis, the valve leading out of the ventricle becomes stiff and narrowed, forcing the chamber to generate extreme pressure to force blood through the tiny opening. Conversely, in aortic regurgitation, the valve fails to close properly, causing blood to leak backward into the ventricle and forcing it to stretch to accommodate the extra volume, leading to left ventricle dilation rather than thickening.
Understanding what causes these structural changes is crucial for preventing irreversible damage to the cardiac muscle. If the underlying cause is addressed early, the thickened or dilated muscle can sometimes recover and return to a more normal size. However, if the condition remains untreated for years, the structural changes become permanent, severely increasing the risk of dangerous arrhythmias, complete heart failure, and the eventual need for invasive surgical correction.
When does left ventricle surgery become necessary?
Left ventricle surgery becomes necessary when structural disease within the chamber, or the valves directly connected to it, severely compromises cardiac function and cannot be managed by medication alone. If the ventricle is progressively enlarging to a dangerous degree, or if its pumping efficiency drops to critically low levels, surgical intervention is required to prevent irreversible heart failure. Surgeons evaluate the geometric changes of the chamber to determine if reparative procedures can restore normal mechanics and alleviate the excessive strain on the cardiac muscle.
Types of surgical procedures for the left ventricle: Depending on the specific structural issue, surgeons may perform a variety of targeted interventions. If the chamber is grossly dilated following a major heart attack, a surgeon might perform a ventricular restoration or aneurysmectomy to remove the scarred, non-functioning tissue and return the chamber to a more normal, efficient shape. In cases where the mitral or aortic valves are the root cause of the ventricular stress, repairing or replacing those valves is the primary surgical objective to halt further muscular damage.
The decision to operate on the left ventricle is never taken lightly, as the chamber is the core engine of systemic circulation. Surgical teams utilize advanced imaging before and during the operation to precisely map the internal geometry of the heart, ensuring their repairs optimize the flow dynamics. In scenarios where the muscle is beyond traditional repair, the surgical plan may pivot to supporting the heart's function entirely, sometimes requiring the consideration of a left ventricular assist device to mechanically take over the heavy workload of the failing chamber.
Diagnosing left ventricle heart issues
Diagnosing left ventricle heart issues requires a combination of clinical evaluation and advanced cardiac imaging to accurately assess the structure and pumping capability of the chamber. The cornerstone of this diagnostic process is the echocardiogram, a non-invasive ultrasound test that uses sound waves to create detailed, real-time moving images of the heart. This painless test allows cardiologists to measure the exact thickness of the ventricular walls, observe the chamber's size during relaxation and contraction, and calculate the critical ejection fraction with high precision.
Tools used to assess left ventricular function: Beyond standard echocardiography, doctors rely on a suite of diagnostic tools to build a complete clinical picture of ventricular health. Cardiac MRI provides highly detailed cross-sectional images of the heart muscle, capable of identifying microscopic scar tissue or subtle inflammation that an ultrasound might miss. Additionally, a coronary angiogram may be performed to inject a contrast dye into the heart arteries, determining if blocked blood supply is the root cause of the left ventricle's functional decline.
Accurate diagnosis is the critical foundation of any successful cardiac treatment plan, as different conditions require radically different approaches to surgical or medical management. By thoroughly mapping out the internal pressures, volumes, and mechanical efficiency of the left ventricle, the diagnostic team provides the surgical team with the exact roadmap they need. This meticulous preoperative analysis ensures that any recommended intervention directly targets the underlying structural defect.
Recovery and supporting left ventricular function
Recovery following left ventricle surgery is a gradual, highly monitored process that requires significant patience, cardiac rehabilitation, and a commitment to lifelong lifestyle adjustments. In the immediate days following the operation, the medical team closely monitors the patient in the intensive care unit, carefully tracking the chamber's renewed pumping strength and managing the heart's response to the surgical trauma. As the patient transitions home, the focus shifts entirely to long-term maintenance and protecting the structural repairs the surgeon has made.
Lifestyle changes after left ventricle surgery: Protecting the newly repaired left ventricle requires strict adherence to medical guidelines and significant daily habit modifications. Patients must diligently manage their blood pressure, adhere to a heart-healthy, low-sodium diet, and engage in closely supervised cardiac rehabilitation exercises to safely rebuild stamina. Furthermore, absolutely avoiding tobacco, carefully managing stress, and maintaining routine follow-up echocardiograms are essential to ensure the ventricle does not regress into a state of failure.
Supporting left ventricular function is a permanent, ongoing commitment that extends far beyond the walls of the operating room. With proper medication compliance, routine medical oversight, and dedicated personal lifestyle management, patients can enjoy a vastly improved quality of life and a highly functional heart. The ultimate goal of the surgical journey is to give the left ventricle a second chance, restoring its natural ability to powerfully and efficiently sustain the body's circulation for years to come.
- Consistent monitoring: Routine echocardiograms track ejection fraction and structural stability over time.
- Diet and medication: Strict blood pressure control and low-sodium diets prevent excess stress on the repaired muscle.
- Cardiac rehabilitation: Guided, progressive exercise strengthens the heart safely without overwhelming the surgical site.






