

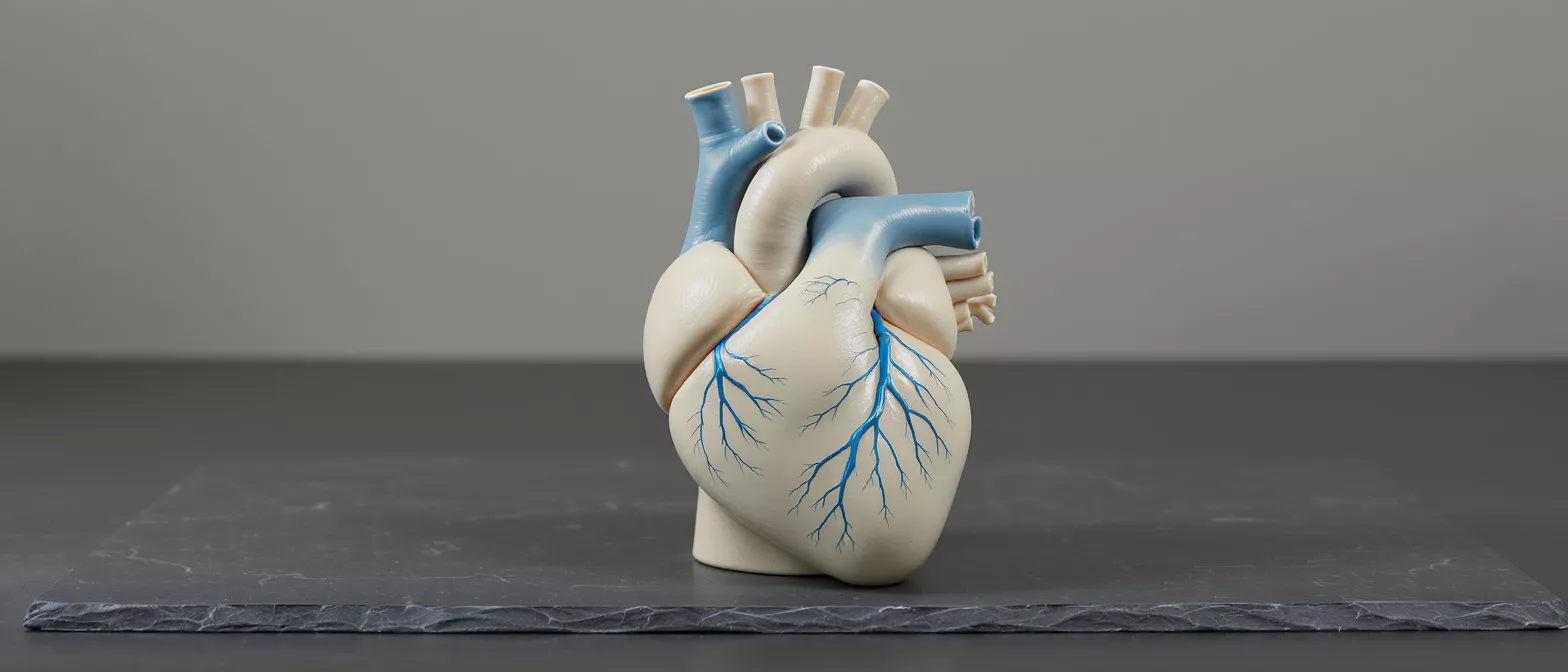
Total Anomalous Pulmonary Venous Drainage
Learn about total anomalous pulmonary venous drainage, a congenital heart defect, including TAPVR symptoms, diagnosis, surgery, and outcomes.
What is Total Anomalous Pulmonary Venous Drainage?
Total anomalous pulmonary venous drainage is a complex congenital heart defect present from birth. In a healthy heart, blood picks up oxygen from the lungs and returns to the left atrium through four pulmonary veins. From there, oxygen-rich blood is pumped to the rest of the body. In a patient with this condition, none of these pulmonary veins connect to the left atrium correctly.
Where do the pulmonary veins connect instead? Instead of returning to the left side of the heart, the pulmonary veins route the oxygenated blood to other areas, often connecting to veins returning to the right atrium or draining into other systemic veins. This redirection creates a mixing of oxygen-rich blood with oxygen-poor blood, depriving the body of the full oxygen supply it desperately needs.
Recognizing this diagnosis in a newborn can be incredibly frightening for families. Understanding the exact anatomy and how the condition alters heart function is the first step toward feeling empowered. Surgeons are highly experienced in correcting this routing issue, building a safe and effective pathway for blood to flow exactly as it should.
How Does TAPVR Affect Normal Blood Flow?
To understand how this defect impacts a patient, it helps to picture the heart as a transit system. In total anomalous pulmonary venous drainage, the train tracks carrying oxygenated blood from the lungs are mistakenly routed back to the right side of the heart instead of the left. This forces the right atrium and right ventricle to work harder, handling far more blood volume than they are designed to pump.
How does blood reach the body if the left atrium is empty? Because the left side of the heart receives no direct blood from the lungs, the only way oxygenated blood reaches the body is through a natural fetal opening called an atrial septal defect. This gap allows the mixed blood to cross from the right atrium into the left atrium, where it can then be pumped out to the body. Every patient with this condition relies on this opening to survive until surgical repair can be performed.
This constant mixing means the blood circulating to the brain and organs carries less oxygen than normal. The severity of this altered blood flow depends heavily on whether the abnormal drainage pathway is wide and unobstructed, or narrow and blocked. An unobstructed pathway allows blood to flow freely, though still improperly, while a blocked pathway creates dangerous pressure backups in the lungs.
What Are the Types of TAPVR?
The classification of this heart defect depends entirely on the path the pulmonary veins take as they drain away from the lungs. Surgeons categorize the condition based on where the veins ultimately connect, which dictates the specific surgical approach required for a successful repair.
What is supracardiac TAPVR? Supracardiac TAPVR is the most common variation, where the pulmonary veins converge into a single vessel that drains upward into a large vein near the heart, eventually returning blood to the right side. What is infracardiac TAPVR? In infracardiac TAPVR, the veins drain downward through the diaphragm, often connecting to the portal vein or liver, which frequently causes severe obstruction and requires urgent intervention.
- Supracardiac: Veins drain upward into a systemic vein above the heart, such as the superior vena cava.
- Cardiac: Veins drain directly into the right atrium or the coronary sinus, the vein that normally drains the heart muscle itself.
- Infracardiac: Veins drain downward below the diaphragm, often causing dangerous pressure backups in the lungs due to obstruction.
- Mixed: A rare form where the veins drain into multiple different locations, combining elements of the other types.
What Symptoms Indicate Pulmonary Venous Return Obstruction?
The clinical presentation of a newborn with this condition varies, but symptoms almost always appear within the first hours or days of life. The most common sign is cyanosis, a bluish tint to the skin, lips, and nail beds that indicates blood oxygen levels are critically low. This happens because the body is circulating blood that has not been properly oxygenated by the lungs.
What happens if the drainage pathway is obstructed? If the anomalous veins are blocked as they try to drain, blood backs up into the lungs. This causes severe respiratory distress, rapid breathing, and extreme fatigue. In these cases, a congenital pulmonary venous drainage repair must be performed urgently to relieve the lung pressure and restore normal circulation.
Doctors will often notice that a baby is struggling to feed, showing poor weight gain, or becoming lethargic. These systemic signs reflect the immense strain on the heart and lungs as they attempt to compensate for the faulty plumbing. Immediate medical evaluation and specialized cardiac care are essential to stabilize the newborn before surgery.
How is Congenital Pulmonary Venous Drainage Diagnosed?
Diagnosis of total anomalous pulmonary venous drainage usually begins in the delivery room, though advances in imaging sometimes allow for detection during routine pregnancy ultrasounds. After birth, if a baby shows signs of low oxygen or respiratory distress, a pediatric cardiology team will quickly step in. They measure oxygen levels and listen for characteristic heart murmurs or abnormal breathing sounds.
What imaging is used for an accurate diagnosis? The gold standard for confirming this newborn heart defect is an echocardiogram, a detailed ultrasound of the heart. This test allows the cardiologist to trace the exact route of the pulmonary veins, pinpoint the connection site, and assess whether the drainage pathway is blocked. It also clearly visualizes the atrial septal defect and overall heart function.
In complex cases where the echocardiogram does not provide enough detail, advanced imaging like cardiac MRI or CT scans may be utilized to give surgeons a precise three-dimensional map. These diagnostic tools are crucial for the surgical team to plan their approach, ensuring they know exactly how to reroute the blood safely before the operation begins.
Why Does TAPVR Cause Cyanotic Congenital Heart Disease?
Total anomalous pulmonary venous drainage is classified as a cyanotic congenital heart disease because it directly causes cyanosis, the visible bluing of the skin. The term cyanotic specifically refers to conditions where oxygen-poor blood bypasses the lungs and mixes with oxygen-rich blood, resulting in systemic circulation that lacks adequate oxygen delivery to the body's tissues.
How does mixing blood lead to low oxygen saturation? Because all the oxygenated blood returning from the lungs dumps into the right side of the heart, it mixes with the deoxygenated blood returning from the body. This mixed blood is then pumped out to the body through the atrial septal defect. The body receives blood that is only partially oxygenated, leading to the characteristic blue coloration and respiratory distress.
Understanding this mechanism helps families realize why surgery is the only definitive treatment. Medical therapy alone cannot fix the plumbing error; only surgical reconnection of the pulmonary veins to the left atrium can permanently separate the oxygen-rich and oxygen-poor blood, resolving the cyanosis and restoring normal, healthy circulation to the growing child.
What Are TAPVR Treatment Options?
The only effective treatment for total anomalous pulmonary venous drainage is surgical repair. Before surgery, medical teams focus on stabilizing the newborn, which often involves medications to support heart function and sometimes a specialized procedure called balloon atrial septostomy. This procedure enlarges the natural opening between the atria to ensure blood can flow to the left side of the heart until surgery can take place.
When should surgical repair be performed? Surgical repair is typically performed urgently, especially in patients where the anomalous veins are obstructed. The timing depends heavily on the anatomy and the patient's clinical stability. In cases of severe obstruction, the cardiac surgeon will operate within the first few days of life to relieve the pressure on the lungs and secure a healthy blood supply.
The goal of treatment is to permanently reroute the pulmonary veins back to the left atrium. By creating a direct connection, the surgeon ensures that oxygen-rich blood flows correctly into the left side of the heart, ready to be pumped to the body. To support recovery and monitor heart function during this critical period, families often seek a newborn heart defect monitor for post-operative care.
What Happens During TAPVR Surgery?
During the operation, the surgical team uses cardiopulmonary bypass, a heart-lung machine, to temporarily take over the job of the heart and lungs. This allows the surgeon to stop the heart safely and open it to perform the delicate reconnection. The procedure requires immense precision and a deep understanding of complex congenital heart anatomy.
How are the pulmonary veins reconnected to the heart? The surgeon creates a wide opening in the back wall of the left atrium and connects it directly to the confluence of pulmonary veins. If the veins are draining into a vertical vein, that vein is carefully closed off so blood can no longer flow the wrong way. This new connection establishes a direct, unobstructed pathway for oxygenated blood to enter the left side of the heart.
Additionally, the surgeon will close the atrial septal defect that was keeping the baby alive before the repair. Closing this gap prevents any future mixing of blood. Using advanced cyanotic heart surgery repair equipment, the team ensures the structural integrity of the heart is fully restored before weaning the patient off the heart-lung machine and allowing the heart to resume its normal beating.
What Are Long-Term TAPVR Surgical Outcomes?
Following a successful repair, the long-term outlook for patients with this condition is generally excellent, particularly when the surgery is performed by an experienced congenital cardiac surgical team. The heart rapidly begins functioning with correct hemodynamics, and the dangerous pressure on the lungs is immediately relieved. Most children grow and develop normally, participating in standard childhood activities.
What complications require long-term monitoring? While the surgical repair corrects the primary issue, patients require lifelong follow-up with a cardiologist. The primary concern is the development of pulmonary vein stenosis, a narrowing of the veins at the surgical connection site. This rare but serious complication can occur years later and may require additional catheter procedures or surgeries to widen the pathway.
Routine echocardiograms are essential to track the growth of the heart and ensure the repaired veins remain wide and unobstructed. Parents should maintain regular cardiac checkups and report any signs of breathing difficulties or exercise intolerance. With modern surgical techniques, the vast majority of patients live full, active, and healthy lives without significant physical limitations.
Navigating Life After TAPVR Repair
Bringing a child home after surgery for total anomalous pulmonary venous drainage is a joyous milestone, but it requires careful attention to recovery. Parents are trained to monitor their child's breathing, appetite, and energy levels. The medical team will provide specific guidelines for wound care, medications, and gradual increases in physical activity as the heart heals and strengthens.
How do families manage cardiac care at home? Families establish a routine with their pediatric cardiologist, attending scheduled follow-up appointments to ensure the heart is adapting well. Open communication with the medical team is vital, especially during growth spurts or when the child enters school. Knowing when to seek medical advice empowers parents to confidently manage their child's unique cardiac history.
Understanding the journey from diagnosis through surgery and recovery helps families face the future with hope. While the diagnosis initially brings intense fear, the success of modern congenital heart surgery transforms a life-threatening defect into a manageable condition. Children who undergo this repair typically thrive, proving that early diagnosis and expert surgical intervention offer a bright, healthy future.






