

EXCEL
EXCEL trial findings explained: how stents compare to bypass for left main coronary artery disease.
The EXCEL trial is one of the most widely discussed studies in modern heart care. It asked a simple question: for disease of the left main coronary artery, do medicated stents work as well as bypass surgery? If your team has mentioned left main disease, this trial very likely shapes the options they present to you.
What was the EXCEL trial in cardiology?
The EXCEL trial was a large randomised controlled trial published in 2016. It enrolled roughly 1,900 patients with narrowing of the left main coronary artery. Each patient was assigned by chance to one of two treatments: a stent placed through a catheter, or coronary artery bypass grafting.
Why randomisation matters: Assigning patients by chance removes bias from the comparison. Both groups contained similar people, with similar anatomy and similar risk profiles. That makes the final results far more trustworthy than simple observation.
Importantly, the trial only studied left main disease of low or intermediate anatomical complexity. It did not include the most complex forms of left main disease, and that limit shapes everything the trial can tell you.
What is left main coronary artery disease?
The left main coronary artery is the short vessel that feeds blood to most of the left pumping chamber. Because it supplies such a large territory, a significant narrowing here is treated more seriously than a blockage in a smaller branch.
Why the location matters: Coronary artery disease narrows the vessels that carry blood to the heart muscle, as Healthline explains in its patient materials. When the narrowed vessel is the left main artery, the muscle at risk is simply much larger.
This is exactly why left main decisions are never made by one specialist alone. Guidelines from international societies recommend that a heart team, not a single doctor, reviews the anatomy and agrees on the safest route for that specific patient.
What is PCI with a drug-eluting stent?
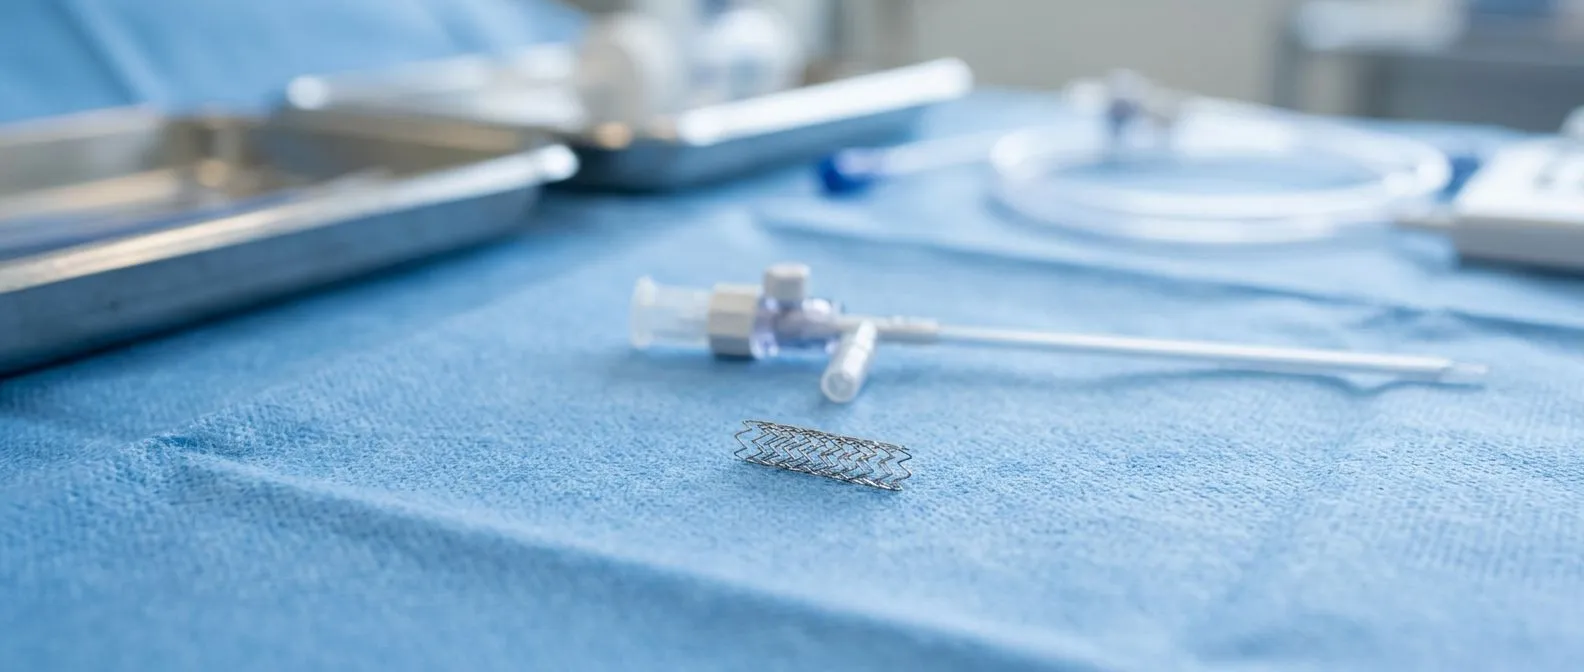
Percutaneous coronary intervention, or PCI, treats a blockage without opening the chest. A thin catheter is guided into the heart artery, a balloon opens the narrowing, and a small mesh tube called a stent holds it open.
The everolimus-eluting stent: In the EXCEL trial, the stent used was coated with everolimus, a medication that is released slowly to keep the artery from scarring shut. This type of device is standard in modern catheter laboratories.
The appeal is obvious. Patients usually go home within a day or two and feel better quickly. The trade-off is that the stent treats the narrowed segment, while the underlying disease process in the artery continues to need medication and follow-up.
What is coronary artery bypass grafting?
Coronary artery bypass grafting, or CABG, is the surgical alternative. The surgeon takes a healthy vessel, often an artery from inside the chest wall or a vein from the leg, and attaches it beyond the blockage so blood flows around it.
A durable detour: A bypass does not remove the blockage. It creates a new route around it, and many grafts, particularly the internal mammary artery, have shown excellent long-term performance over decades of follow-up.
The trade-off is recovery. Bypass surgery traditionally requires opening the breastbone, a hospital stay of several days, and weeks of healing. Less invasive surgical approaches exist, but they are chosen carefully rather than for everyone.
What did the EXCEL trial find?
At three years, the rate of the trial's combined endpoint, which counted death from cardiovascular causes, stroke, and heart attack together, was similar between the stent group and the surgery group. Neither strategy separated clearly from the other on that primary measure.
Different kinds of events: The pattern of complications was not identical. Heart attacks occurring around the time of the procedure were more common in the surgery group, while spontaneous heart attacks in the months and years afterwards were more common in the stent group.
The published conclusion was that, in experienced centres, PCI with an everolimus-eluting stent is a reasonable option for patients with left main disease of low or intermediate complexity.
Why did the EXCEL trial spark debate?
Much of the controversy concerns how a "heart attack" was defined and counted. The trial used a definition that includes small heart injuries caused by the procedure itself, and critics argued this favoured the stent arm in the final comparison.
The long-term question: Extended follow-up analyses kept the discussion alive, because some observers read the later data as suggesting a possible survival difference. Others interpreted the same data differently, and the two camps still disagree.
What is often lost in this debate is who the findings apply to. The EXCEL trial says nothing about complex left main disease. Its conclusions belong to a specific group: lower-complexity anatomy treated by experienced teams.
How does the EXCEL trial compare with the SYNTAX trial?
The SYNTAX Trial was the earlier landmark study of the same question, and it included the full range of left main complexity. Its results showed a clear advantage for bypass surgery in patients with the most complex anatomy.
Complexity is the dividing line: The EXCEL trial was deliberately designed for simpler anatomy. Taken together, the two studies draw the boundary: complex left main disease leans towards surgery, simpler disease opens the door to stents.
Modern guidelines are built on both trials. When your team discusses your anatomy, they are effectively placing you on that spectrum and recommending the treatment with the best evidence for your position on it.
What do the EXCEL trial results mean for patients?
For a patient with lower-complexity left main disease, the trial means stenting is a legitimate, guideline-supported choice, not a compromise. For more complex anatomy, surgery remains the option with the stronger long-term evidence.
Your anatomy decides, not the trial: Factors such as the distribution of the blockage, disease in other vessels, diabetes, and the strength of the heart muscle all shift the balance one way or the other.
Every case is reviewed by our multidisciplinary team against international practice guidelines before a recommendation is made, and the patient receives a clear proposal with the alternatives, because the final decision always belongs to the patient.
When is bypass surgery still the better option?
Surgery tends to remain the recommended route when the anatomy is complex, when several vessels are diseased, or when the heart muscle is already weakened. In these situations, a complete bypass of the diseased system offers more durable protection.
Situations that usually favour surgery:
- Complex left main anatomy: heavy calcification, involvement where the artery splits, or a high anatomical complexity score.
- Multivessel disease with diabetes: bypass has shown more durable results across the whole artery system.
- Weakened pumping function: a complete revascularisation is generally better tolerated by the heart long term.
Our team performs conventional, minimally invasive, robotic and transcatheter procedures, and we recommend the less invasive route only where the evidence supports it for that specific patient.
Key takeaways on the EXCEL trial
The EXCEL trial found that, for left main disease of low or intermediate complexity, stents and bypass surgery produced comparable results on its main combined endpoint. It did not settle the question for complex anatomy, and its counting methods remain debated among specialists.
- Comparable for simpler disease: in selected patients, stenting is a guideline-supported option, not a second choice.
- Surgery keeps the edge in complexity: the more complex the anatomy, the stronger the case for bypass.
- The heart team decides: trials set the framework, but your own anatomy sets the recommendation.
If left main disease has entered your life, the most useful step is a proper heart team discussion. The first contact with our team is a free video consultation, where we talk through your condition, explain what your studies show in plain words, and say which tests are genuinely still needed, because a second opinion is a normal part of deciding about heart surgery.






