

Circulatory Arrest in Heart Surgery: How Organs Are Protected
Circulatory arrest heart surgery protects your brain and organs during aortic procedures.
Some heart operations ask the surgeon to do something that sounds impossible: stop the circulation entirely. Circulatory arrest in heart surgery means deliberately pausing blood flow so delicate structures — most often the aortic arch, the great vessel at the top of the heart — can be repaired in a completely still, bloodless field. It is a carefully planned, carefully timed part of certain operations, not an emergency. This guide explains what it involves, how your brain and organs are protected while the pump is off, what the real risks are, and what recovery actually looks like, so you can walk into any conversation about surgery understanding the words your team uses.
What Is Circulatory Arrest in Surgery?
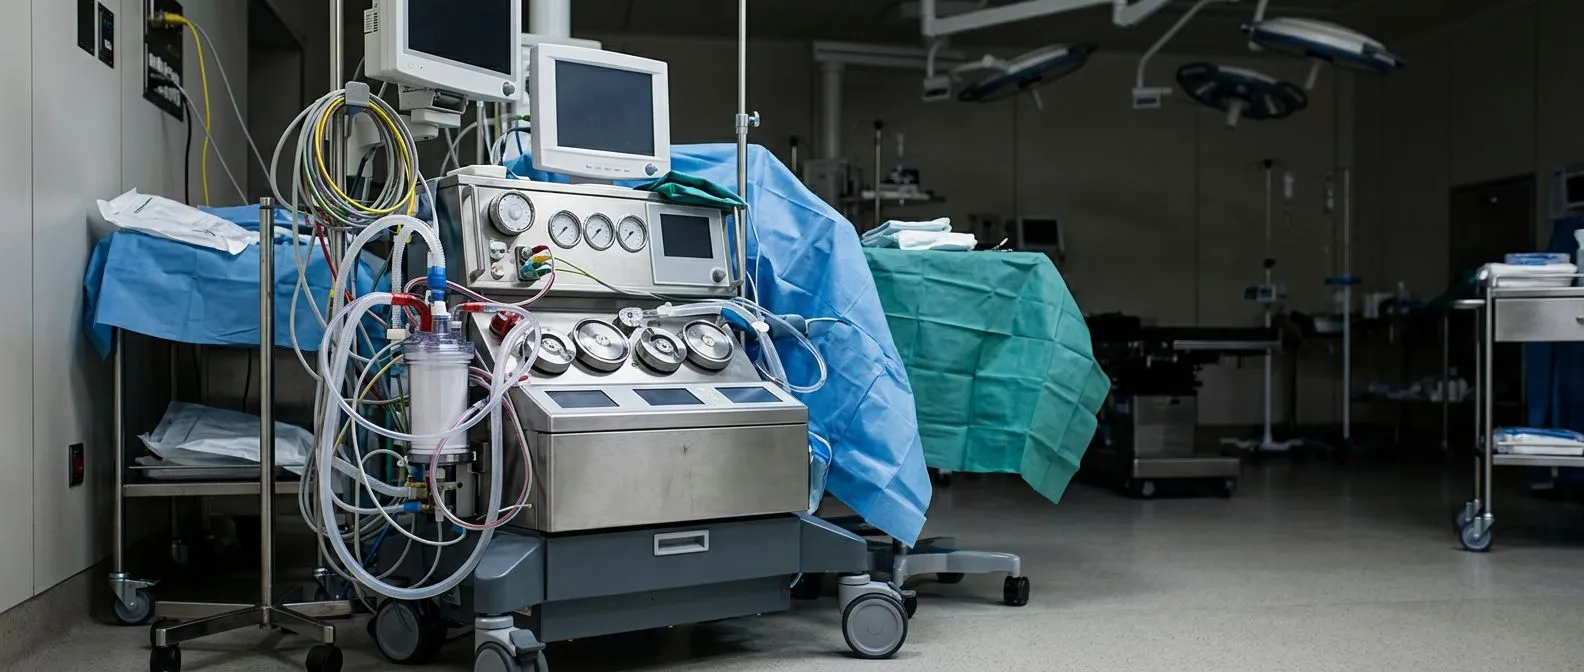
The basic idea. When people ask what is circulatory arrest in surgery, the answer starts with the heart-lung machine. In most open-heart operations, this machine takes over the work of the heart and lungs, circulating and oxygenating blood while the heart is intentionally stopped. For certain operations, the surgeon goes one step further: the pump is stopped, the clamps are released, and blood flow through the body pauses completely for a defined period.
Why it is ever necessary. Some repairs cannot be done while blood is moving. The aortic arch branches into three vessels that supply the brain and arms, and sewing a new graft into that area while blood streams past is unsafe and technically impossible. A quiet, bloodless field lets the surgeon see every stitch, remove plaque or clot, and reconstruct the vessel precisely.
It is always planned. Circulatory arrest is never something that happens to a patient by surprise. It is chosen in advance, discussed with the whole team, and supported by cooling, protective drugs and perfusion strategies. In our practice, every case is reviewed by the multidisciplinary team against international practice guidelines before a recommendation is given, and the patient receives a clear proposal with the alternatives — the final decision is always theirs.
Circulatory Arrest vs Cardiac Arrest: What's the Difference?
One is controlled, one is not. The distinction in circulatory arrest vs cardiac arrest is fundamental. Cardiac arrest is an emergency: the heart stops unexpectedly, blood flow ceases without warning, and every minute without resuscitation causes damage. Circulatory arrest during surgery is the opposite — a deliberate, controlled pause, performed in an operating theatre with the patient cooled, monitored and supported, and with a team ready to restart circulation the moment the surgeon needs to.
Protection is the dividing line. In a spontaneous cardiac arrest, organs are warm and unprotected, so damage accumulates quickly. In surgical circulatory arrest, the body is cooled first and the brain is protected by specific techniques described below, which changes the mathematics entirely.
Why the confusion matters. Patients sometimes read the word "arrest" on their surgical plan and panic. Understanding that this is a planned, protected step — not a medical crisis — is one of the most reassuring things a surgical team can explain. In consultations we take the time to explain in plain words what the studies and the plan actually show, and to answer every question before any decision is made.
Why Aortic Surgery Needs Circulatory Arrest
The arch problem. The aorta is the body's main artery, and its arch — the curved segment just above the heart — gives rise to the vessels feeding the brain. When the aorta dilates beyond safe limits (a diameter of 5.5 cm is a common surgical threshold for the ascending aorta), tears, or becomes lined with fragile plaque, that segment must be replaced. There is no way to open the arch and work inside it while blood surges through.
Other indications. Circulatory arrest also serves in some complex valve operations, removal of tumors or thrombus, certain congenital repairs, and cases where a severely atherosclerotic aorta cannot be safely clamped at all — clamping a diseased aorta can shower debris toward the brain, so pausing circulation is actually the safer option.
Deciding if you need it. Not everyone having aortic surgery does. A straightforward ascending aorta replacement can often be done with a simple cross-clamp while the machine circulates normally. Whether your operation requires circulatory arrest depends on the anatomy, the extent of disease, and the operative strategy — and that is exactly what a multidisciplinary review is for. We encourage second opinions and treat seeking one as a normal part of deciding about heart surgery.
How Does the Hypothermic Circulatory Arrest Technique Work?
Cooling comes first. The hypothermic circulatory arrest technique rests on a simple biological fact: cold tissue consumes far less oxygen. Before the pump is stopped, the heart-lung machine gradually cools the patient's blood, lowering the body's core temperature — commonly into the range of deep hypothermia, around 18–20°C. At these temperatures, the brain's metabolic demand falls dramatically, buying the surgeon a safe window of stillness.
The arrest itself. Once the target temperature is reached and confirmed by measurements (a cooling period is never rushed), circulation is stopped. The aorta is opened, and the surgeon works in a bloodless field. This is why such operations are sometimes called "standstill" surgeries — and yes, they are very real, refined over decades of aortic and congenital practice.
Controlled rewarming. When the repair is complete, circulation is resumed and the patient is warmed gradually back to normal temperature. Rewarming is managed deliberately and slowly, because it is a physiologically delicate phase. The whole sequence — cool, arrest, repair, rewarm — is choreographed by the surgeon, the perfusionist (the specialist running the pump) and the anesthesiologist together. Precision in the operating room is trained, not improvised; in our team, Dr Molina performed the first robotic heart surgery in Guadalajara.
Springer publishes extensive clinical literature on the perioperative management of deep hypothermic circulatory arrest, documenting how cooling protocols and temperature management have been standardized across cardiac surgery centers.
How Is Brain Protection During Heart Surgery Achieved?
Cooling alone is not enough. Modern brain protection during heart surgery layers several strategies. Hypothermia slows metabolism, but surgeons also use selective cerebral perfusion: while the body's circulation is paused, the perfusion machine continues to send cool, oxygenated blood directly into the arteries that supply the brain, usually through cannulas placed in the arm or neck vessels. The brain keeps receiving blood while the rest of the body rests.
Monitoring the brain continuously. Throughout the operation, the team watches brain function in real time using EEG (brain wave monitoring) and near-infrared spectroscopy, which measures oxygen levels in the cerebral tissue through sensors on the forehead. If any value drifts, the team acts before a problem develops.
Additional safeguards. Carbon dioxide management during cooling, careful control of blood pressure during rewarming, and anti-embolism measures — filters, careful cannula placement, and "de-airing" routines before restoring flow — all reduce the risk of stroke from air or debris. This combination of hypothermia organ protection surgery plus selective perfusion is what transformed aortic arch operations from high-risk experiments into standard care.
What Is the Safe Duration of Circulatory Arrest?
The time question every patient asks. Safe duration circulatory arrest is a real, studied question. At deep hypothermic temperatures, most centers consider arrest periods of up to roughly 30 minutes to carry low additional risk, and the clinical literature shows that risk of neurological complications rises meaningfully once circulatory arrest time extends beyond about 30 minutes. Shorter is always better, and surgical planning aims to complete the repair well inside that window.
Selective perfusion extends the clock. Because selective cerebral perfusion keeps blood flowing to the brain, many teams now use it routinely, which relaxes the time pressure on the repair itself. The surgeon is not racing a clock while the brain goes unperfused.
What determines your window. The safe duration depends on temperature, patient factors such as age and pre-existing vascular disease, and the specific technique used. This is a surgical decision, not a fixed number to memorize — your team should be able to explain their expected arrest time for your operation and what they do to stay within safe limits.
What Are the Risks of Circulatory Arrest Surgery?
The honest risk picture. Circulatory arrest surgery risks center on the brain and the recovery period. The main concerns are stroke (typically low in modern series but not zero), temporary confusion or memory changes in the days after surgery, kidney stress during the low-flow period, and bleeding — operations on the aorta involve extensive suture lines. The risk of multi-organ failure is rare with modern cooling and perfusion techniques, but it is a recognized possibility in prolonged or complex cases, which is why every detail of the plan matters.
What reduces those risks. Experience of the team, correct patient selection, meticulous temperature and time management, and continuous neuromonitoring all demonstrably improve outcomes. Patients with pre-existing carotid disease, prior stroke, or advanced age are discussed with extra care, and sometimes an alternative strategy is chosen precisely to lower neurological risk.
Rarely, a deeper pause. In the most complex operations — massive bleeding, deep hypothermia for trauma or rescue — teams sometimes combine circulatory arrest with techniques adjacent to mechanical circulatory support, which can take over heart and lung function afterward while the body recovers. In our practice, we recommend the less invasive route only where the evidence supports it for that patient; where a full arch repair with circulatory arrest is genuinely required, we say so plainly, and where a less invasive option exists, we present it.
For context on how expert teams structure these decisions, the 2019 EACTS Expert Consensus on long-term mechanical circulatory support reflects the kind of guideline-driven review that international practice expects for complex circulatory support and arrest strategies.
What Happens During Aortic Arch Replacement With Circulatory Arrest?
The operation step by step. Aortic arch replacement circulatory arrest procedures follow a recognizable sequence. First, standard open-heart preparation: anesthesia with a breathing tube (you are always fully intubated during heart surgery — the anesthesiologist manages your breathing throughout), monitoring lines, and connection to the heart-lung machine. The patient is cooled; EEG and cerebral oxygen monitors confirm readiness.
During the arrest. Circulation is stopped, the arch is opened, and the surgeon replaces the diseased segment with a fabric graft, reattaching the branch vessels to it. Selective cerebral perfusion continues to the brain through cannulas. Once the graft is secure and de-aired, full circulation is restored and rewarming begins.
Getting the rest of the heart done. Often the same operation addresses the aortic valve or the ascending aorta in the same sitting. Combining repairs means one anesthetic, one recovery, and one hospital stay — a significant benefit when the anatomy calls for it.
How Is Pediatric Circulatory Arrest in Heart Surgery Different?
Congenital repairs need it more often. Pediatric circulatory arrest heart surgery is a cornerstone of congenital heart surgery. Many complex congenital defects — involving the arch, the great vessels, or single-ventricle physiology — simply cannot be repaired in a beating-heart field. Children tolerate cooling and rewarming well, and their recovery from deep hypothermia is generally robust.
Children cool faster. Because of their smaller body mass and higher surface-area-to-weight ratio, infants and children cool and rewarm more quickly than adults, which shortens the induction and recovery phases. Techniques and temperature targets differ from adult practice, and congenital teams follow dedicated pediatric protocols.
Long-term outcomes. Decades of follow-up data exist on children who underwent deep hypothermic arrest as infants, and the majority of children with appropriately brief arrest times develop normally. Modern techniques that include regional cerebral perfusion have further reduced risk, which is why outcomes for congenital arch surgery have improved steadily.
What Is the Recovery Time After Circulatory Arrest Surgery?
The first days. Circulatory arrest recovery time follows the same broad arc as other open-heart operations, with a few specifics. Most patients wake from anesthesia in the intensive care unit within hours, though the team may keep sedation briefly overnight if rewarming or bleeding management needs time. Temporary hoarseness or swallowing difficulty can occur after arch surgery because the nerve to the vocal cord runs alongside the arch — it usually resolves.
Memory and cognition. Some patients notice mild short-term memory slips or slower word-finding in the first weeks after surgery. This is common after any prolonged heart-lung machine use and typically improves over weeks to months. Persistent major deficits are uncommon with modern techniques.
The weeks after. Hospital stay is commonly around a week, followed by weeks of progressive activity at home, cardiac rehabilitation, and gradual return to normal life over roughly two to three months. The rewarming and cooling process itself does not usually add weeks to recovery — the extent of the repair drives the timeline. What matters most is that you know your own plan and milestones.
Getting care in Mexico. For patients considering circulatory arrest heart surgery in Mexico, the logistics matter as much as the surgery: a clear preoperative plan, sensible travel timing, and follow-up arrangements you can rely on remotely. Our first contact is a free video consultation: we get to know the patient, talk through the condition, and say which studies are still needed so no unnecessary ones are ordered; a face-to-face visit at the consulting rooms follows when the patient decides to go ahead. We work from consulting rooms in Guadalajara, Querétaro and Hermosillo.

Choosing Your Heart Surgery Team for Complex Operations
Questions worth asking. When a proposed operation includes circulatory arrest, you are entitled to clear answers. Ask how often the team performs the specific operation, what their arrest times typically are, whether selective cerebral perfusion will be used, what monitoring they rely on, and what their approach is if the repair takes longer than planned.
Why training breadth matters. Complex aortic work rewards a team that has trained across the full spectrum of techniques. Dr Molina trained in cardiothoracic surgery at the Universidad de Guadalajara, in cardiac, minimally invasive, robotic and structural surgery at the University of Montreal, and in structural cardiology and TAVR at CHU Bordeaux, and the team also trained at Jena, Bad Berka and Buffalo. That breadth means the recommendation you receive is not shaped by having only one tool available.
How the decision gets made. A good team reviews your imaging and studies together, explains the options in plain language, names the trade-offs honestly, and supports your right to a second opinion. We do exactly that — every case is reviewed by our multidisciplinary team against international practice guidelines, and the final decision is always the patient's.
- Checklist for your consultation: bring your recent imaging (CT or echocardiogram reports), your medication list, and written questions.
- Ask about brain protection: cerebral perfusion technique, neuromonitoring, and expected arrest time.
- Ask about alternatives: a clear team will explain what a less invasive option would and would not achieve for you.
Key Takeaways on Circulatory Arrest in Heart Surgery
What to remember. Circulatory arrest in heart surgery is a controlled, planned pause in circulation used mainly for aortic arch and complex repairs, made safe by deep cooling, selective cerebral perfusion and continuous neuromonitoring. It is entirely different from a cardiac arrest, which is an uncontrolled emergency. Modern techniques keep the arrest window short and the brain protected, and risk falls further with experienced teams, careful patient selection and guideline-based planning.
What good care looks like. You should expect a transparent explanation of why your operation needs this step, honest discussion of risks and alternatives, and a team comfortable with both conventional and minimally invasive approaches. If any part of the plan is unclear, keep asking until it is.
Your next step. If you or a family member are facing surgery that may involve circulatory arrest, do not try to self-diagnose or decide from articles alone. Talk it through with a qualified cardiac team — we are a multidisciplinary team of cardiac surgeons led by Dr Alejandro Molina, with consulting rooms in Guadalajara, Querétaro and Hermosillo, and the first contact is a free video consultation where we get to know the patient, talk through the condition, and say which studies are actually needed. Book a consultation and bring your questions; we will answer every one.
What Is Traumatic and Cerebral Circulatory Arrest?
Two terms you may encounter. Traumatic circulatory arrest is a rare emergency-room scenario, usually after severe chest trauma or profound hypothermia (for example, cold-water drowning), where circulation has stopped and the body is cold enough that prolonged resuscitation — sometimes with the heart-lung machine used for emergency rewarming — can be attempted. Deep hypothermia before cardiac arrest can be protective in a paradoxical way: the cold slows metabolism, which is precisely why resuscitation from accidental hypothermia sometimes succeeds after remarkably long pauses. This is a different situation from surgical circulatory arrest, but it shares the same principle of hypothermia organ protection.
Cerebral circulatory arrest. Cerebral circulatory arrest is a different term again — it refers to the complete cessation of blood flow to the brain, most often diagnosed after severe brain injury, and it is part of the medical determination of brain death. It is unrelated to planned surgical arrest and important to keep distinct when you read medical reports.
Keeping the terms straight. Planned circulatory arrest in the operating theatre, cardiac arrest as an emergency, and cerebral circulatory arrest after brain injury are three separate things that unfortunately share a phrase. When your surgical team writes "circulatory arrest" on your plan, they mean the controlled, protective kind described throughout this article — and they should always be willing to explain exactly how it applies to you.
Your Circulatory Arrest Questions, Answered
Will I be aware during the arrest period? No. You are fully anesthetized, with brain monitoring confirming adequate depth of anesthesia and cerebral oxygen levels throughout. The arrest period passes for you as a single moment of sleep.
Does the cooling damage my body? No. Controlled hypothermia is one of medicine's oldest protective tools, used deliberately for decades. The body is cooled slowly, held at temperature only as long as needed, and rewarmed carefully under continuous monitoring.
How long does the circulatory phase typically last? In modern practice, usually well under 30 minutes for the pure arrest period, and often less. When the repair needs more time, selective cerebral perfusion keeps blood flowing to the brain so the time is not spent unprotected.
What if my operation turns out not to need it? Surgical plans are made from your imaging, but the final judgment belongs to the surgeon in the operating room. Teams prepare for circulatory arrest in many aortic cases and simply may not use it if the anatomy allows a simpler approach — that is the plan working, not failing.






