

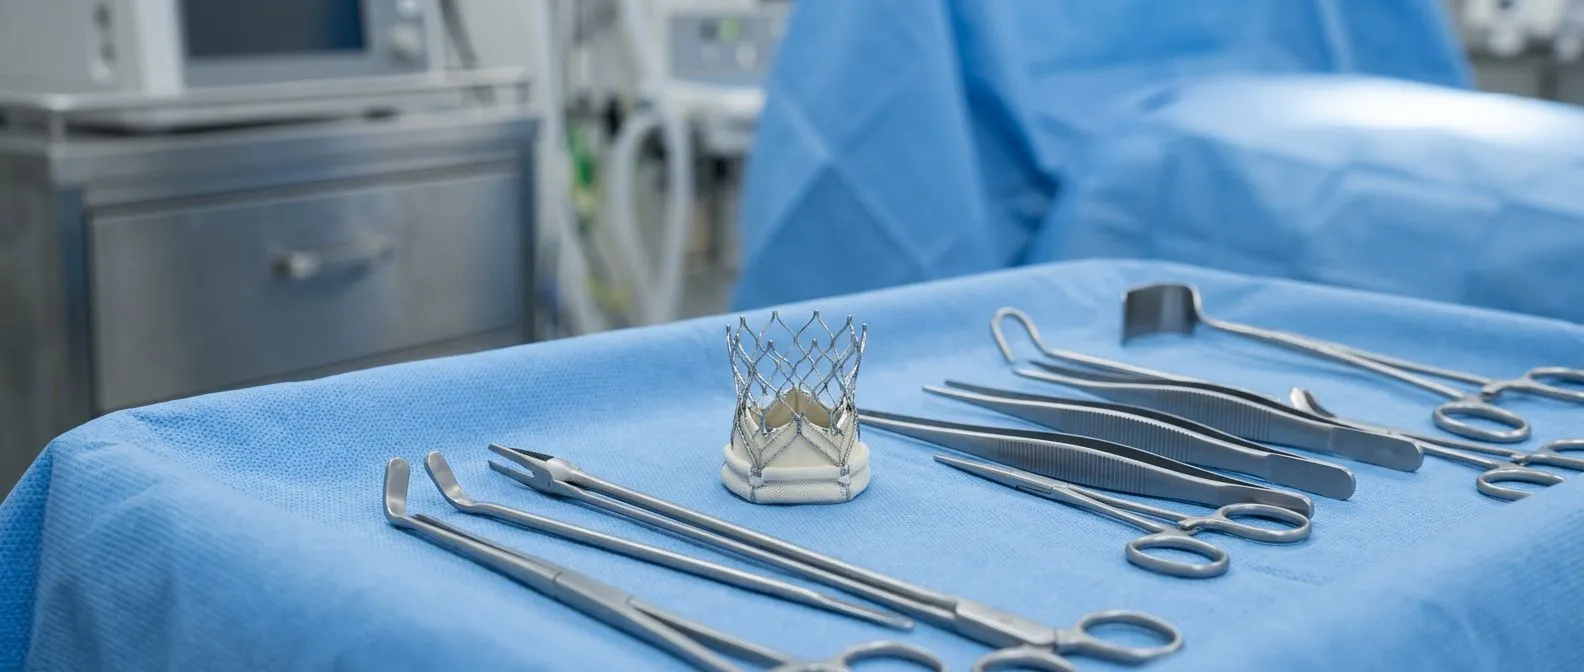
Right Anterior Thoracotomy for Aortic Valve Replacement
A right anterior thoracotomy valve replacement avoids splitting the breastbone.
Aortic valve replacement through a right anterior thoracotomy valve approach is one of the most important advances in modern cardiac surgery, and it is the reason many patients facing valve surgery can now avoid the traditional "cracked" breastbone. If you have been told you have aortic stenosis or another aortic valve problem, you are probably weighing two things at once: the need to fix the valve, and the fear of a long, painful recovery. This guide walks you through what a right anterior thoracotomy actually is, how the operation compares to open-heart surgery through the sternum, what recovery really looks like, and how to decide whether this less invasive route is right for you.
What Is Right Anterior Thoracotomy?
Right anterior thoracotomy is a surgical approach to the heart through a small incision on the front and right side of the chest, between the ribs, rather than through the breastbone. The surgeon works through a window that is usually just a few centimeters wide, positioned directly over the aortic valve — the heart's main outflow gate, which sits between the right and left sides of the chest. Because the incision does not divide the sternum, the chest wall stays structurally intact.
Is thoracotomy the same as open-heart surgery? This is one of the most common questions we hear, and the answer is nuanced. A right anterior thoracotomy is still genuine open-heart surgery in the technical sense: the heart is opened, the heart-lung machine takes over circulation, and the valve is repaired or replaced. What changes is the access route — the incision is smaller and the breastbone is not cut, so the term "minimally invasive" refers to the approach, not to a lesser operation.
It is also worth knowing where this technique sits among the alternatives. In Springer's surgical literature, the right anterior mini-thoracotomy is described alongside ministernotomy as a validated access route for aortic valve replacement, and it has become the standard approach for minimally invasive mitral valve surgery as well. For aortic valve disease specifically, the key point is that the incision is placed directly over the valve, which gives the surgeon excellent exposure without sacrificing the stability of the chest wall.
How Right Anterior Thoracotomy Aortic Valve Replacement Works
Right anterior thoracotomy aortic valve replacement follows the same surgical principles as a conventional operation, but the access is different. Before understanding the steps, it helps to know what the aortic valve does: it is the one-way valve between the left ventricle — the heart's main pumping chamber — and the aorta, the large artery that carries blood to the whole body. When it narrows (aortic stenosis) or leaks (aortic regurgitation), the heart has to work harder, and the definitive treatment is replacing the valve.
How the operation unfolds. The patient is placed under general anesthesia, fully asleep and intubated with a breathing tube, as in any major cardiac operation. The surgeon makes a small incision in the third or fourth space between the ribs on the right side of the chest. The heart-lung machine is connected through smaller cannulae — often one in the groin and one near the incision — so that the heart can be stopped and protected while the surgeon works. The diseased valve is removed, and a new valve, either tissue or mechanical, is sewn into place.
Which valves can be used. The choice of prosthesis is the same as in any Surgical Aortic Valve Replacement: tissue valves from animal or human donors, mechanical valves, or in some cases an Intra-annular Valve designed to sit within the natural valve ring. The choice depends on your age, your anticoagulation preferences, and your valve anatomy. In our practice, every case is reviewed by the multidisciplinary team against international guidelines before a recommendation is made, and you receive a clear proposal with the alternatives — the final decision is always yours.
Thoracotomy vs Sternotomy: What the Outcomes Show
The most common alternative to a right anterior thoracotomy is a full sternotomy, in which the breastbone is divided down the middle. It is the classic approach for aortic valve replacement, and it gives the surgeon complete exposure of the heart. But it comes with trade-offs that matter enormously to patients.
What the comparison studies found. When researchers compared ministernotomy with right anterior mini-thoracotomy for aortic valve replacement, both approaches achieved excellent valve outcomes with far less surgical trauma than full sternotomy. The mini-thoracotomy offers specific advantages: the incision avoids the bone entirely, which eliminates the risk of sternal wound complications and the long sternal healing restrictions. Reported series of this approach show that, in experienced hands, results for mortality and valve performance match conventional surgery, with the added benefits of faster recovery and less pain.
How it fits alongside TAVR. Transcatheter Aortic Valve Implantation — known in Mexico and the United States as TAVR (Transcatheter Aortic Valve Replacement) — is the other less invasive option, delivered through a catheter in the groin without opening the chest. TAVR is usually preferred for older or higher-risk patients; a mini-thoracotomy valve replacement is often preferred for younger or middle-aged patients who need a durable, surgically implanted valve. Some patients also need a Hemiarch Replacement or other work on the aorta, which may favor one approach over another. Your surgical team should explain why one route is proposed over the others for your specific anatomy.
Benefits of Minimally Invasive Aortic Valve Surgery
Why do patients and surgeons choose a small incision heart valve operation when the conventional one works? The reasons fall into three categories: recovery, comfort, and appearance.
- Less surgical trauma: no divided breastbone means no sternal wound infection risk and no sternal wires healing under your chest.
- Faster recovery: patients are typically back to driving and normal daily activity sooner because the chest wall itself is not injured.
- Smaller incision: a scar of a few centimeters on the right side of the chest, hidden under the breast fold, instead of a long sternal scar.
- Less bleeding: published series of mini-thoracotomy aortic valve replacement report less blood transfusion and fewer wound complications than full sternotomy.
Recovery milestones that matter most to patients. In our team's experience, patients who undergo right anterior thoracotomy valve procedures are usually able to breathe deeply and cough more comfortably within days, which directly reduces the risk of lung complications. That single advantage — a chest wall that moves normally — is what makes the difference in the first weeks of thoracotomy valve surgery recovery.
It is worth noting that the benefits are surgical, not medical: the operation itself is the same heart surgery in every way that counts. The published evidence does not show that the valve lasts longer or works better because of the incision; the benefit is in how you get there and how you come back.
Who Is a Candidate for a Right Thoracotomy Valve Replacement?
Not every patient with aortic valve disease is a candidate for a right anterior thoracotomy. The decision depends on several factors that your team will evaluate together.
Factors that favor this approach. Isolated aortic valve disease — meaning the valve is the problem and the other valves and coronary arteries are healthy — is the ideal scenario. A patient who has had a previous sternotomy is often a strong candidate for a mini-thoracotomy, because it avoids re-entering the old scar. Reasonable lung function and the ability to tolerate single-lung ventilation briefly during surgery also matter.
Factors that may point elsewhere. Patients with severe lung disease, significant chest wall deformity, or a dilated aortic root needing an Aortic Root Replacement may be better served by a sternotomy or by a transcatheter route. If you also need a Mitral Valve Replacement or coronary bypass, the surgical plan may change. Some patients with prior valve surgery become candidates for a Valve-in-valve procedure through a catheter instead of any new operation.
How the decision is made. In our practice, the first step is a free video consultation: we get to know the patient, talk through the condition, and identify exactly which studies are still needed so no unnecessary ones are ordered. A face-to-face visit at the consulting rooms follows when the patient decides to go ahead. In that consultation we take the time to explain what the studies actually show, in plain words, and to answer every question before any decision is made.
What Happens During the Mini-Thoracotomy Valve Procedure?
Knowing the sequence of the operation can calm a great deal of preoperative anxiety, so here is what a typical small incision aortic valve replacement looks like from the patient's side.
The day of surgery. You arrive at the hospital, meet the anesthesia team, and are taken to the operating room. After you are asleep, a breathing tube is placed — you will be intubated during open-heart surgery, whether the approach is thoracotomy or sternotomy, and you will not remember it. The surgeon makes the small incision on the right chest, spreads the ribs gently, and connects the heart-lung machine.
During the operation. The heart is stopped and protected with a cold solution, and the surgeon opens the aorta above the valve. The old valve is removed and the new one is sewn in, exactly as in a conventional Surgical Aortic Valve Replacement. The aorta is closed, the heart is restarted, and the incision is closed in layers with no sternal wires.
Specialized instruments. Because the incision is small, the team uses long-shafted instruments, special retractors, and often videoscope assistance to see inside the chest. In our operating rooms, Dr Molina and the team — trained in cardiac, minimally invasive, robotic and structural surgery at the University of Montreal, and in structural cardiology and TAVR at CHU Bordeaux — also perform robotic-assisted thoracotomy valve procedures where the anatomy supports it. Dr Molina performed the first robotic mitral valve repair in the Ángeles Health System and the first robotic heart surgery in Guadalajara, and that experience with the same small-incision approach carries directly into this operation.
Thoracotomy Valve Surgery Recovery: What to Expect Week by Week
Recovery is the part of this journey that patients ask about most, and the honest answer is that a right anterior thoracotomy shortens the road — but it does not eliminate it.
The first days. You will spend one to two nights in the intensive care unit and then move to a regular ward. You will have a chest tube, which is removed within a few days. Pain is managed with medication; most patients describe the pain as a soreness around the small incision, significantly easier to tolerate than sternal pain because the breastbone is intact.
The first weeks. Walking is the main activity, and it usually starts the day after surgery. You will be asked to avoid heavy lifting for a few weeks, but the restrictions are far less strict than after a sternotomy, where patients are barred from lifting for six to eight weeks to protect the healing bone. The published consensus on aortic valve replacement via mini-thoracotomy consistently notes faster functional recovery and earlier return to work compared with sternotomy.
The first months. Most patients return to office work and driving within a few weeks, and to fuller activity over one to three months. Cardiac rehabilitation — supervised exercise and education — is encouraged and helps enormously. In our experience, patients who follow the rehabilitation program and keep their follow-up appointments recover with confidence and rarely need more than the scheduled visits. If you feel chest pain, breathlessness at rest, or a fever, you should contact your surgical team immediately rather than waiting for the next appointment.
Aortic Valve Replacement Scar Size: What the Incision Looks Like
For many patients, especially women and younger people, the cosmetic question is a real one, and it deserves a straight answer rather than a dismissal.
Where the scar sits. The aortic valve replacement scar from a right anterior thoracotomy is a single incision of roughly 5 to 8 centimeters at the right edge of the sternum, in the second or third intercostal space — the natural crease between the ribs. Positioned this way, it is usually hidden under clothing or the breast fold, and for many patients it becomes nearly invisible within a year.
How it compares to other scars. A full sternotomy leaves a vertical scar the length of the breastbone, plus the bone itself takes months to heal fully. A transaxillary or TAVR approach leaves a scar in the groin or under the arm. The right thoracotomy scar sits in the middle of that spectrum: it is a real surgical incision, but it is small, single, and placed where the chest wall is naturally forgiving.
What the scar will feel like. The incision heals in layers, and most patients report numbness around the scar for several months, which gradually improves. Rib spreading during the operation can cause mild soreness between the ribs that resolves over weeks. If the cosmetic result matters to you, raise it with your surgeon before surgery — placement and closure technique are choices that can be discussed.
Are Thoracotomy Heart Surgery Risks Different?
Any honest discussion of heart surgery must include risk, and the question "what is the riskiest open-heart surgery?" and "is a thoracotomy a major surgery?" deserve careful answers.
Is it a major surgery? Yes. A right anterior thoracotomy is a major cardiac operation with the same fundamental risks as conventional surgery: bleeding, stroke, infection, arrhythmia, and the need for a second operation. The incision is smaller, but the heart is still opened and stopped. What the mini-thoracotomy changes is the profile of the risk — it lowers the risk of sternal wound complications and bleeding from the bone, but it introduces a small learning curve for the surgeon and a different kind of exposure.
Risks specific to the thoracotomy approach. The main technique-specific concerns are related to cannulation through the groin and the rib-spreading itself, plus the possibility of converting to a full sternotomy if the anatomy proves difficult. Published series describe conversion rates that are low in experienced centers, and the outcomes of the REPRISE II trial of the Lotus valve system — a study of the broader transcatheter valve landscape — help illustrate how the standards for less invasive valve therapy are continuously measured against surgical ones.
Even rare complications have solutions. A striking example is hemostasis management: a published case report describes achieving control of bleeding after a Transcatheter Aortic Valve Replacement in a patient with an aortobifemoral bypass graft using a perclose device, showing that even the most unusual vascular complications can be managed with novel techniques when the team is prepared. In our practice, every case is reviewed by the multidisciplinary team against international practice guidelines before a recommendation is given, precisely so that the approach chosen is the one with the lowest risk for your situation.
How to Choose a Heart Surgeon for a Minimally Invasive Valve Replacement
Choosing the right surgeon and the right team is probably the single most important decision you will make, and it matters more than which incision you choose.
- Volume and training: ask how many mini-thoracotomy aortic valve replacements the surgeon performs per year, and where they trained in the technique.
- Multidisciplinary review: the best programs review every case with a full team — surgeons, cardiologists, imaging specialists — before recommending an approach.
- Clear communication: you should understand why the recommended approach is proposed, what the alternatives are, and what happens if something goes wrong.
- Transparency about second opinions: a confident team will welcome a second opinion and treat it as a normal part of deciding about heart surgery.
What to ask about the team. In our practice, we are a multidisciplinary team of cardiac surgeons led by Dr Alejandro Molina, with consulting rooms in Guadalajara, Querétaro and Hermosillo. We encourage second opinions and treat seeking one as a normal part of the process. Our work covers valve disease, coronary disease, the aorta and structural heart conditions, and we perform conventional, minimally invasive, robotic and transcatheter procedures — we recommend the less invasive route only where the evidence supports it for that patient. That means some patients are steered toward TAVR, some toward a thoracotomy, and some toward conventional surgery, and the reason is always explained in plain words.
Questions worth bringing to any consultation. Ask which valve will be used and why; ask about the surgeon's experience with the exact technique; ask how long the recovery will be for someone your age and health; and ask what follow-up will look like. A good team will welcome every question, and if the answer to "do I really need surgery at all?" is not clear, you should keep asking until it is.
Deciding on heart surgery is one of the most consequential choices a person makes, and the good news is that you no longer have to choose between a durable surgical valve and a big incision. Right anterior thoracotomy valve surgery offers the best of both worlds for the right patient: a fully implanted valve through a small, rib-sparing incision. If you have aortic stenosis or another aortic valve condition, the most useful next step is not to self-diagnose but to talk with a qualified cardiac team. Book a consultation — start with a free video consultation if that is easier — and ask directly whether a right anterior thoracotomy valve approach is the lowest-risk option for your situation. The right answer is the one that is explained to you, not chosen for you.

For patients considering less invasive valve replacement in Mexico, practical questions about cost and travel are as important as the surgical ones.
What drives the cost. The total cost of a mini-thoracotomy aortic valve replacement depends on the hospital, the type of prosthesis (tissue or mechanical), the length of stay, and whether any additional procedures are needed. Because the incision is smaller, hospital stays are often shorter than after a sternotomy, which can reduce the overall cost — but the valve itself is the largest single variable, so ask for a full itemized estimate.
Insurance and pre-authorization. If you are traveling from abroad, ask the clinic to provide a complete medical summary and cost breakdown in advance so your insurer can review it.
Planning the trip. For international patients, we plan the timeline around a short preoperative visit, the surgery itself, and a recovery period before the flight home. In our practice, the first contact is a free video consultation where we identify exactly which studies are still needed, so no unnecessary tests are ordered before you travel.

One final thought on the anatomy of the decision: the aortic valve is fed by the heart's own circulation, and the left anterior descending artery — the vessel that runs down the front of the heart — is right next to the surgical field. This is why the choice of approach must be made by a team that understands the whole heart, not just the valve. If you also have coronary disease or a Mitral Valve Prolapse, the plan changes, and the team should tell you so before you commit to anything.
Mini-Thoracotomy Valve Surgery in Mexico: Costs, Travel and Insurance
For patients considering less invasive valve replacement in Mexico, practical questions about cost and travel are as important as the surgical ones.
What drives the cost. The total cost of a mini-thoracotomy aortic valve replacement depends on the hospital, the type of prosthesis (tissue or mechanical), the length of stay, and whether any additional procedures are needed. Because the incision is smaller, hospital stays are often shorter than after a sternotomy, which can reduce the overall cost — but the valve itself is the largest single variable, so ask for a full itemized estimate.
Insurance and pre-authorization. Most private insurers and international policies will cover valve surgery, but they may require prior authorization and specific documentation. If you are traveling from abroad, ask the clinic to provide a complete medical summary and cost breakdown in advance so your insurer can review it.
Planning the trip. For international patients, we plan the timeline around a short preoperative visit, the surgery itself, and a recovery period before the flight home. In our practice, the first contact is a free video consultation where we identify exactly which studies are still needed, so no unnecessary tests are ordered before you travel.
One final thought on the anatomy of the decision: the aortic valve is fed by the heart's own circulation, and the left anterior descending artery — the vessel that runs down the front of the heart — is right next to the surgical field. This is why the choice of approach must be made by a team that understands the whole heart, not just the valve. If you also have coronary disease or a Mitral Valve Prolapse, the plan changes, and the team should tell you so before you commit to anything.






