

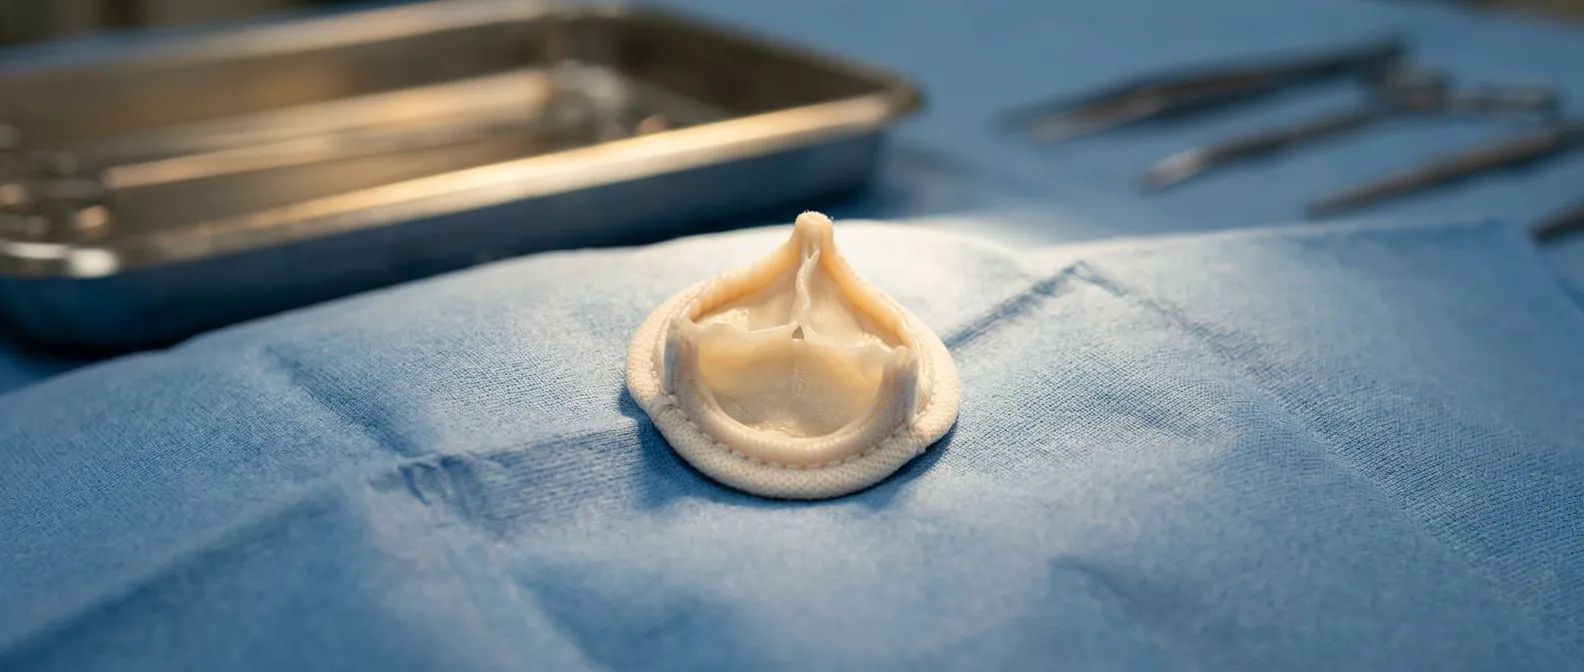
ACC/AHA Guidelines on Valve Disease for Patients
ACC/AHA guidelines valve disease explained in plain language for patients.
If you or a family member has been told you have a leaky or narrowed heart valve, you have probably searched for answers and found pages written for cardiologists, not patients. The ACC/AHA guidelines on valve disease are the most widely used rulebook in the United States for deciding when a valve needs watching, when it needs medicine, and when it needs surgery or a catheter-based fix. This guide translates that rulebook into plain language, so you can follow your own care with confidence and ask sharper questions at your next appointment.
What Are the ACC/AHA Guidelines on Valve Disease?
The ACC/AHA guidelines on valve disease are consensus documents written by the American College of Cardiology and the American Heart Association. Panels of cardiologists, surgeons, imaging specialists and patient representatives review every major study on valve disease and distill it into graded recommendations. Each recommendation carries a class — from Class I, meaning strong benefit, down to Class III, meaning the option should not be used — and a level of evidence, from multiple randomised trials down to expert opinion.
Why patients should care: these documents shape what nearly every heart centre in North America, and many beyond, actually do. When your cardiologist says your valve has "crossed the threshold" for intervention, that threshold usually comes from the guidelines. Understanding them means you can check whether your treatment plan follows the mainstream of evidence or takes a deliberate alternative route.
The most recent full revision, the 2020 ACC/AHA guideline for the management of patients with valvular heart disease, updated earlier versions from 2014 and 2017. It reflects the arrival of transcatheter valves, better imaging, and long-term data on older surgical techniques. Evidence reviews published in cardiology journals, including work summarised in JAMA, feed directly into these panels.
How Do the Guidelines Stage Valve Disease?
One of the most useful ideas in valve disease staging is the four-phase system, called stages A through D. It replaced the older habit of calling a valve simply "mild," "moderate" or "severe." The staging looks at two things at once: how abnormal the valve is, and how your heart is responding to it.
Stage A (at risk): you have risk factors — for example a bicuspid aortic valve, an abnormal murmur, or a family history — but the valve itself still works normally. No treatment is needed, only awareness and sometimes periodic imaging.
Stage B (progressive): the valve is genuinely diseased but the leak or narrowing is mild to moderate, and the heart muscle has not changed yet. Stage C (severe, asymptomatic) means the valve is severe but you feel well, with the heart still pumping normally or, at stage C2, beginning to enlarge and weaken. Stage D (symptomatic severe) means the diseased valve is now causing breathlessness, chest discomfort, dizziness or fainting.
Why staging changes decisions: the timing of intervention differs by stage. Some severe valves need fixing even when you feel fine; others can be safely watched. Your stage, not just your symptoms, drives the recommendation.
- Stage A: at risk — healthy valve, watchful monitoring.
- Stage B: progressive valve disease — no symptoms, heart not yet affected.
- Stage C: severe disease without symptoms (C) or with early heart changes (C2).
- Stage D: severe disease with symptoms — intervention is usually indicated.
What Do the ACC/AHA Guidelines Say About Aortic Stenosis?
Aortic stenosis means the valve between the left pumping chamber and the main artery to the body has narrowed, forcing the heart to push blood through a smaller opening. The ACC/AHA guidelines on aortic stenosis are unusually clear: severe, symptomatic aortic stenosis (stage D) is a mechanical problem, and no medication can fix the narrowed valve. Intervention is a Class I recommendation.
Asymptomatic severe aortic stenosis: the guidelines also recommend intervention for asymptomatic severe aortic stenosis when measurements show the valve is truly critical, or when the heart's pumping function has begun to fall, or when exercise testing brings on symptoms. Many patients unknowingly cut back their activities as the valve narrows, so the guidelines encourage doctors to ask carefully about daily function, not just about dramatic symptoms.
What to expect on the journey: the diagnosis usually starts with an echocardiogram, an ultrasound of the heart that measures valve opening and blood flow. Once severe stenosis is confirmed, your team maps the valve, the artery it sits on, and your overall fitness to choose between catheter-based replacement and surgery. In our practice, every case like this is reviewed by the multidisciplinary team against international practice guidelines before any recommendation is made, and the patient receives a clear proposal with the alternatives.
ACC/AHA Guidelines on Mitral Valve Regurgitation: Repair or Replace?
Mitral valve regurgitation means the valve between the left atrium and left ventricle leaks blood backwards with every heartbeat. The ACC/AHA guidelines on mitral valve regurgitation draw a crucial line between two kinds of leakage. Primary regurgitation is a problem with the valve leaflets themselves — a stretched leaflet, a torn cord, Mitral Valve Prolapse gone severe. Secondary regurgitation is a problem with the heart muscle, which has stretched so much that the valve can no longer close properly.
Chronic severe MR and the repair-first principle: for primary, chronic severe MR, the guidelines recommend surgery even without symptoms when the evidence shows the heart is starting to strain, and strongly favour repair over replacement when a durable repair is likely. Repair keeps your own valve tissue, avoids lifelong blood thinners, and shows better long-term outcomes. The guidelines specify experienced valve centres for this reason — durability depends heavily on the surgeon's experience.
Secondary regurgitation is different: when the leak comes from a dilated heart, repairing the valve alone does not fix the underlying muscle disease. Here the guidelines recommend careful evaluation of the heart's function and, increasingly, transcatheter options for patients who are not good surgical candidates. In our consultations we take the time to explain which kind of regurgitation a patient actually has, in plain words, because the treatment pathway is completely different for the two.
When Do the Guidelines Recommend TAVR?
TAVR — transcatheter aortic valve replacement — is a way of inserting a new aortic valve through a thin tube, usually from an artery in the groin, without opening the chest. The ACC/AHA guidelines on the TAVR procedure changed dramatically over the past decade as trial after trial showed strong results. Today the guidelines support TAVR across a broad range of ages and surgical risks, with the choice between TAVR and surgery based on age, anatomy and life expectancy rather than on "inoperable or not."
How the choice is framed: in general terms, the guidelines favour TAVR at older ages or when open surgery carries higher risk, and favour surgical aortic valve replacement at younger ages where long-term surgical durability is best documented. Structural heart programmes also weigh factors like valve anatomy, calcium distribution, and whether other procedures are needed at the same time. Transcatheter valve intervention is no longer a last resort; it is a first-line option for many patients.
What the procedure is like: most TAVR patients walk the day after the procedure and go home within a few days. In our team's practice, we perform conventional, minimally invasive, robotic and transcatheter procedures, and we recommend the less invasive route only where the evidence supports it for that specific patient — never as a default.
What Do the Guidelines Advise About Surgical Aortic Valve Replacement?
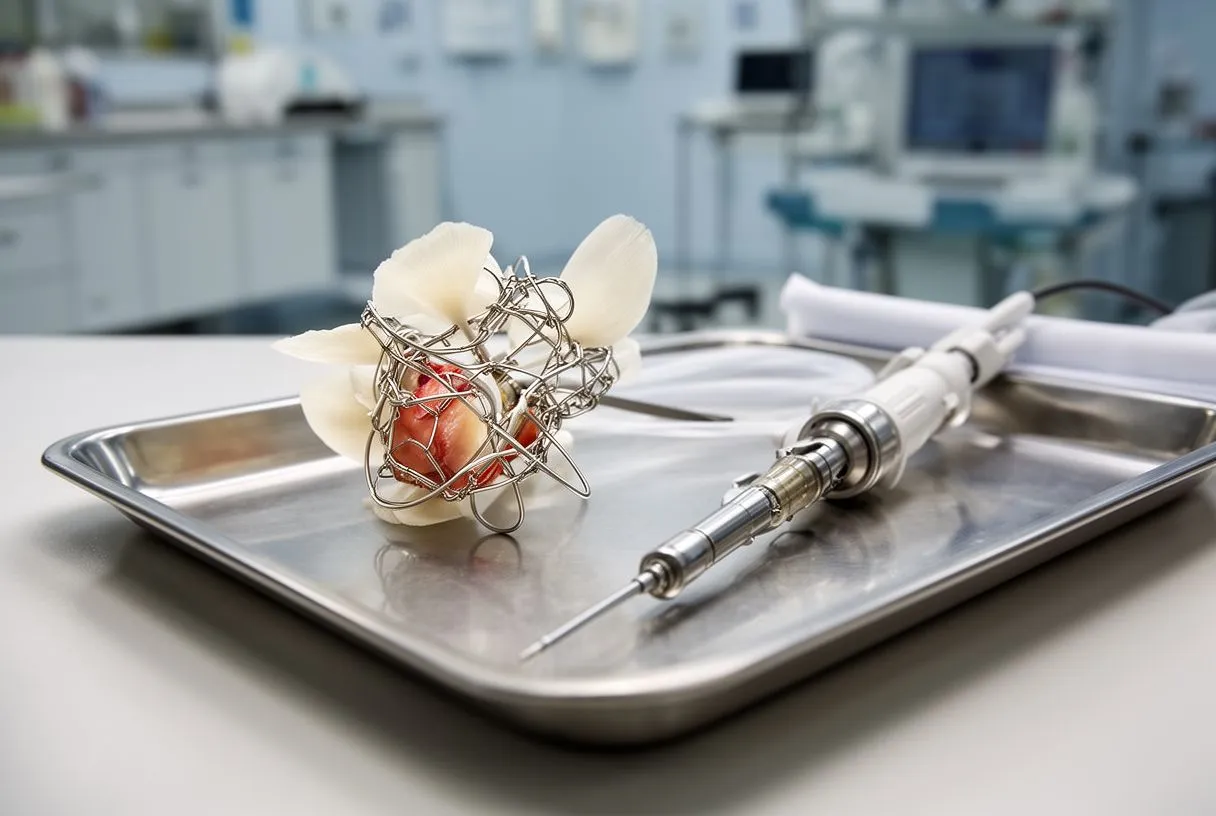
Surgical aortic valve replacement remains the benchmark against which every other option is measured. The ACC/AHA guidelines on valve replacement give surgery a Class I recommendation for symptomatic severe aortic stenosis and for asymptomatic patients whose heart function has declined. Surgery is also preferred when the valve anatomy is not friendly to a catheter approach, or when the patient needs bypass grafting or another procedure at the same time.
What surgery involves: the surgeon removes the diseased valve and sews in a replacement — either a tissue valve (from animal or human tissue) or a mechanical valve (metal, which lasts decades but requires lifelong anticoagulation medication). The guidelines describe this choice carefully, because it depends on your age, your willingness to take blood thinners, and your goals for quality of life.
Recovery reality: conventional surgery involves opening the chest through the breastbone, with a hospital stay of roughly five to seven days and several weeks of healing. Minimally invasive and robotic approaches use smaller incisions and can shorten some parts of recovery, though the valve operation itself is the same. Our team reviews every surgical candidate against international guidelines, and we are explicit with patients about which approach we propose and why — the final decision is always theirs.
How Does the Heart Team Approach Work Under the Guidelines?
The ACC/AHA guidelines on valve disease risk stratification and the heart team approach require that decisions about severe valve disease be made not by one doctor but by a multidisciplinary team: a cardiologist, a cardiac surgeon, an imaging specialist, and often an anaesthetist or intensivist. This is not a formality. Studies and guideline panels concluded that team-based decisions produce better-matched treatments than any single-speciality judgment.
What happens in a heart team meeting: your scans are projected, your valve is measured, your other conditions are listed, and the team discusses whether surgery, TAVR, medicine, or continued observation gives you the lowest risk for your situation. A clear proposal with the alternatives should come out of that discussion — and you should be able to understand it.
Your role in the decision: the guidelines emphasise shared decision-making, meaning you receive the reasoning in plain language and the choice is yours. We encourage second opinions and treat seeking one as a normal part of deciding about heart surgery. In our case reviews, the patient receives a written proposal with the alternatives and the reasoning behind each, so the decision rests in their hands with the facts laid out.
What Do the Guidelines Say About Prosthetic Valves and Follow-Up?
Once a valve is replaced or repaired, the guidelines shift from deciding to monitoring. The ACC/AHA guidance on prosthetic valve follow-up sets out how often you should have an echocardiogram, what symptoms should trigger urgent checks, and what blood-thinning medication each valve type requires. Mechanical valves require lifelong warfarin; most tissue valves require a shorter course of anticoagulation, if any, after the procedure.
Watching for valve degeneration: tissue valves gradually wear out over years, a process the guidelines call structural valve degeneration. Your echocardiogram schedule is designed to catch this early, while it is still easy to treat — often with a valve-in-valve procedure, where a new transcatheter valve is placed inside the old one. This is why keeping your follow-up appointments matters as much as the operation itself.
Practical follow-up advice: report new breathlessness, palpitations, swelling, or fainting promptly rather than waiting for your next scheduled scan. Dental hygiene matters too — the guidelines connect gum infections to valve infections. Ask for a written follow-up calendar and clear instructions on which symptoms warrant an immediate call, so you are not left guessing what "something feels different" means.
Do the Guidelines Cover Antibiotics Before Dental Work?
Yes — the ACC/AHA guidelines on infective endocarditis prophylaxis are among the most consulted pages in the entire document. Infective endocarditis is an infection of the valve surface, usually introduced by bacteria from the mouth entering the bloodstream during dental procedures. The guidelines define exactly which patients should receive preventive antibiotics and which should not.
Who needs antibiotics: the list includes patients with prosthetic valves, patients with certain congenital heart defects, patients who have had endocarditis before, and some transplant recipients. Most other repaired valves, and healed prolapse without leakage, no longer require routine antibiotic cover — a deliberate change made decades ago based on evidence that routine antibiotics caused more harm than benefit in low-risk patients.
What this means day to day: tell your dentist about your valve condition, keep your teeth and gums healthy, and ask your cardiologist which group you fall into rather than assuming. A one-page rulebook beats guesswork, and the guidance is short enough to read in five minutes. In our consultations, we review each patient's endocarditis risk category with them explicitly, so they can pass the right information to their dentist.
How Do ESC and EACTS Guidelines Compare, and What Should You Ask Your Team?
Patients in Europe, Latin America and elsewhere often encounter the ESC Guidelines (European Society of Cardiology) and the EACTS Guidelines (European Association for Cardio-Thoracic Surgery), which are periodically published jointly. The European and American documents agree on the vast majority of points — severe symptomatic valves need treatment, repair beats replacement where repair is durable, and heart team evaluation matters. Where they differ, the differences tend to be about thresholds and timing rather than direction.
What a good specialist consultation should include: whether your team follows ACC/AHA or ESC/EACTS guidance, you should expect the same essentials — your valve stage explained in plain words, the treatment options with their trade-offs, the imaging or studies still needed, and a clear proposal you can take home. If any of those pieces is missing, ask for them. A second opinion is never an insult to your doctor; it is a normal part of a decision this significant.
Getting started in Mexico: many international patients wonder how to access this standard of care locally. In our team, the first contact is a free video consultation: we get to know the patient, talk through the condition, and say which studies are still needed so no unnecessary ones are ordered; a face-to-face visit at our consulting rooms in Guadalajara, Querétaro or Hermosillo follows when the patient decides to go ahead. Dr Molina trained in cardiothoracic surgery at the Universidad de Guadalajara, and in cardiac, minimally invasive, robotic and structural surgery at the University of Montreal, with further training in structural cardiology and TAVR at CHU Bordeaux — so patients receive care built on both international guidelines and hands-on experience with every modern technique.
The ACC/AHA guidelines on valve disease, taken together, deliver one central message: valve disease follows a predictable course, modern imaging catches it early, and there is now a well-matched treatment option for nearly every stage and every body. The worst thing you can do is ignore a known valve problem; the second worst is rushing into the first treatment offered without understanding the alternatives. Bring the questions in this guide to your own cardiac team, and if you would like that team to review your case, book a consultation rather than trying to self-diagnose — a proper assessment with your own scans is the only way to know which stage you are in and what your valve needs next.







