

EACTS Guidelines on Heart Surgery for Patients
EACTS guidelines heart surgery explained for patients in Guadalajara.
If you or a family member has been told you need heart surgery, you have probably come across the phrase "EACTS guidelines" while researching online. These are the recommendations written by the European Association for Cardio-Thoracic Surgery, the body that sets the EACTS guidelines on heart surgery used by surgical teams across Europe and increasingly around the world. Understanding what these guidelines say — and how they shape real decisions about your operation — can take a great deal of fear out of the process. This article explains them in plain language, from valve replacement to bypass surgery to recovery.
What Are the EACTS Guidelines?
The definition in plain words. EACTS stands for the European Association for Cardio-Thoracic Surgery. It is a scientific body representing cardiac surgeons across Europe and beyond. Periodically, it joins forces with other societies to publish clinical practice guidelines: carefully reviewed documents that tell surgical teams which treatments are proven, which are experimental, and which should be avoided.
How the guidelines are written. Each guideline is produced by a panel of experts who read the published evidence, grade the strength of every study, and issue recommendations with an explicit level of certainty. This is why a recommendation may read "we recommend" in one place and "we suggest" in another — the wording reflects how solid the underlying evidence actually is. Nothing in the guidelines is an opinion from a single surgeon.
Why patients should care. When your cardiac team reviews your case, these documents are the reference point behind their advice. At our practice, every case is reviewed by the multidisciplinary team against international practice guidelines before a recommendation is given — the patient receives a clear proposal with the alternatives, and the final decision is always theirs. That means the advice you receive should trace back to evidence, not habit.
Why European Heart Surgery Standards Matter for Patients
Consistency across borders. The EACTS guidelines exist to make sure a patient in one country receives the same standard of reasoning as a patient in another. For anyone considering treatment abroad — including the many international patients who travel to Mexico for cardiac care — this matters enormously. Knowing that a team applies international heart surgery standards gives you a common yardstick to compare proposals.
Guidelines protect you from unnecessary procedures. A major theme throughout the guidelines is proportionality: surgery only when the expected benefit outweighs the risk for your specific anatomy and health. This is one reason we encourage second opinions and treat seeking one as a normal part of deciding about heart surgery. A proposal that follows the guidelines will always name the less invasive alternative, if one exists.
How training connects to standards. Guidelines only help if the team knows how to apply them, and the less invasive route is chosen only where the evidence supports it for that patient. Dr Molina trained in cardiothoracic surgery at the Universidad de Guadalajara, in cardiac, minimally invasive, robotic and structural surgery at the University of Montreal, and in structural cardiology and TAVR at CHU Bordeaux — training that shaped how the team weighs European and North American evidence side by side.
What Are the Current Guidelines for Aortic Valve Replacement?
The valve that most often needs help. The aortic valve sits between the heart's main pumping chamber and the aorta, the large artery that carries blood to the body. When it becomes narrowed (aortic stenosis) or leaks (regurgitation), the heart strains to push blood through. The joint ESC/EACTS guidelines on valvular heart disease set out when valve replacement is advised — for example, in severe narrowing with symptoms, or in severe leaking where the heart's pumping function has begun to decline. 2017 ESC/EACTS Guidelines for the management of valvular heart disease marked a turning point by formally recognising transcatheter replacement as an option alongside open surgery.
How the decision between surgery and TAVR is made. The guidelines weigh age, valve anatomy, other health conditions, and the condition of the blood vessels in the chest. In broad terms: younger, lower-risk patients with straightforward anatomy tend to be offered surgical replacement with a durable valve, while older or higher-risk patients are steered toward TAVR (transcatheter aortic valve replacement), where a new valve is delivered through a catheter, usually from the groin, without opening the chest. In our consultations we take the time to explain what the studies actually show, in plain words, and to answer every question before any decision.
Why the choice is personal, not automatic. No single rule fits everyone. Two patients with the same diagnosis may be given different recommendations because of artery calcification, frailty, or previous chest surgery. The updated joint guideline documents refined these choices further, reflecting years of new trial evidence. 2021 ESC/EACTS Guidelines for the management of valvular heart disease strengthened the role of heart teams — cardiologists and surgeons deciding together — in every valve case.

What Are the Latest Guidelines for TAVR?
TAVR in one sentence. TAVR — transcatheter aortic valve replacement — is a way to implant a new aortic valve through a thin tube inserted in an artery, most often in the groin, without opening the chest or stopping the heart. It was first developed for patients too fragile for open surgery, and the guidelines have progressively widened the group of people for whom it is reasonable.
What the guidelines currently recommend. In the joint European guidelines, TAVR is the preferred option for older patients with severe aortic stenosis, and is an accepted alternative to surgery for many others after the heart team reviews anatomy and risk. The key word is "reviewed": the guidelines require the decision to go through a multidisciplinary team, because TAVR has its own trade-offs, such as the need for a pacemaker in some patients or limits on how long certain valve types last.
What we see in practice. In our team, which performs conventional, minimally invasive, robotic and transcatheter procedures, a TAVR proposal is never made on the echo report alone — we check the arteries, the valve's shape on CT scanning, and the patient's overall condition before recommending it. If the anatomy is unfavourable, we will say so and explain why open surgery may be the lower-risk route for that person, even though TAVR sounds less intimidating.
How Do the EACTS Guidelines Approach Coronary Bypass Surgery?
When bypass surgery is advised. Coronary artery bypass grafting (CABG) creates new routes for blood around blocked arteries in the heart. The guidelines on myocardial revascularisation, written jointly with cardiology societies, specify which patients benefit from surgery rather than stents: typically those with disease in several arteries, blockage of the left main artery, or weakened heart muscle, and those with diabetes where surgery offers more durable results.
Arterial grafts are the guideline standard. A central recommendation is the use of the left internal thoracic artery — an artery from the chest wall — as the graft to the most important coronary artery, because it lasts far longer than veins taken from the leg. Using two arterial grafts where possible is increasingly favoured. In our operating rooms, graft strategy is planned individually for each patient before the first incision is made.
How the decision between stents and surgery is made. The guidelines require calculating a validated risk score, such as EuroSCORE II, which estimates surgical risk from factors like age, kidney function and prior operations. The heart team then compares that risk against the expected durability of stents. In our practice, every case is reviewed by the multidisciplinary team against international practice guidelines, and the patient receives the full comparison — including the option of doing nothing yet, when that is genuinely reasonable.
What Do the Guidelines Say About Minimally Invasive Heart Surgery?
What "minimally invasive" actually means. Instead of opening the chest through the breastbone (a sternotomy), minimally invasive valve surgery uses small incisions, often between the ribs, sometimes assisted by a robot. The operation on the heart is the same; the approach is different. Recovery is typically easier on the body, but the technique demands specific training.
The guideline principle: proven benefit, chosen case by case. The guidelines do not say smaller is always better. They support minimally invasive approaches when the team has the expertise and the patient's anatomy allows it with equivalent safety. This matches our own policy exactly: we perform conventional, minimally invasive, robotic and transcatheter procedures, and we recommend the less invasive route only where the evidence supports it for that patient — never as a marketing point.
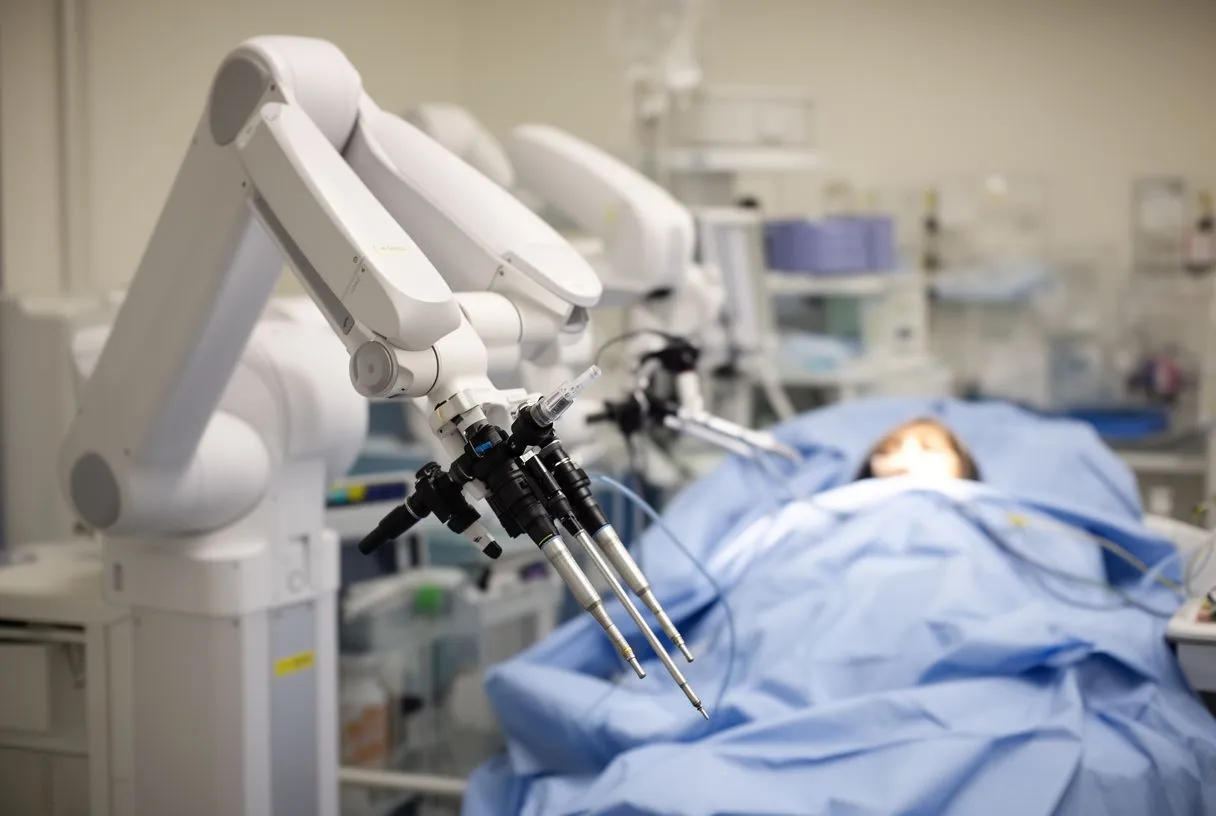
Robotics in the guidelines' context. Robotic surgery is the most technically demanding form of minimally invasive cardiac surgery, and the guidelines emphasise institutional experience and case volume. Dr Molina performed the first robotic mitral valve repair in the Ángeles Health System and the first robotic heart surgery in Guadalajara. If you are offered robotic surgery, asking how many such cases a team performs each year is a fair and important question.
What Is the ERAS Cardiac Surgery Protocol?
The idea behind ERAS. ERAS stands for Enhanced Recovery After Surgery. It is a structured protocol — now endorsed in joint EACTS guideline documents — that covers the whole journey around a cardiac operation: better pre-operative nutrition and conditioning, avoidance of unnecessary fasting and drains, early mobilisation the day after surgery, and prompt removal of tubes and lines. The goal is a smoother, faster recovery with fewer complications.
Why it became a guideline priority. Studies collected over many years showed that some of the discomfort patients used to accept as normal — prolonged bed rest, long fasting, extended ventilator time — actually slowed healing. The ERAS cardiac surgery protocol turned those findings into a checklist that surgical teams follow for every patient, and the guidelines now treat these measures as part of good care rather than optional extras.
What it means for you as a patient. If your surgical team follows ERAS principles, you should expect a pre-operative plan (including stopping smoking and optimising blood counts), a clear daily recovery path, and honest expectations about when you will walk, eat and go home. Ask your team directly whether they follow an enhanced recovery protocol — it is a reasonable question and a good sign if the answer is specific.
EACTS Guidelines vs American Guidelines: What's the Difference?
Two bodies, same evidence. The European guidelines come from EACTS together with the European Society of Cardiology (ESC). Their American counterparts are the ACC/AHA Guidelines, issued by the American College of Cardiology and the American Heart Association. Both groups read the same worldwide evidence, so their core recommendations usually align closely — for example, both support TAVR for appropriate older patients and surgery for durable valve repair in younger ones.
Where they differ in style. Differences tend to be in emphasis and timing rather than direction. One document may adopt a new technique slightly earlier, or phrase a recommendation more cautiously, depending on how its panel weighs new trials. Neither is "more advanced" — they are parallel readings of the same science.
The practical takeaway for patients. When comparing a proposal in Europe, North America or Mexico, what matters is not the flag on the guideline but whether your team follows one of them and can explain why. At our consulting rooms in Guadalajara, Querétaro and Hermosillo, we review every case against international practice guidelines and tell patients plainly which guideline informed each part of the plan — and we encourage a second opinion whenever the decision feels weighty.
- Same evidence base: ESC/EACTS and ACC/AHA guidelines both rest on global clinical trials, so core advice on valves and bypass surgery converges.
- What to ask any team: "Which guideline does your recommendation follow, and what alternative did you consider?" — a guideline-based team can answer without hesitation.
Why Patient Blood Management Is a Guideline Priority
The 2024 joint guidelines. A recent joint guideline from EACTS with the European association for cardio-thoracic anaesthesia focused on patient blood management in adult cardiac surgery: raising blood counts before the operation, minimising blood loss during it, and using transfusions strictly by threshold rather than habit. The reason is simple — avoiding unnecessary transfusion reduces complications and speeds recovery.
What happens before surgery. Part of the protocol involves checking for anaemia weeks in advance and treating it, so you arrive at the operating room in the strongest possible condition. Liver function tests and full blood counts are standard here. In our first contact — a free video consultation — we get to know the patient, talk through the condition, and say which studies are still needed so no unnecessary ones are ordered; a face-to-face visit at the consulting rooms follows when the patient decides to go ahead.
What happens during and after. Surgeons following these guidelines use techniques that reduce bleeding, recover the patient's own blood where possible, and transfuse only when a defined threshold is crossed. For you, this translates into fewer tubes, fewer transfusions, and a faster return to normal life — outcomes that matter as much as the operation itself.
What the EACTS Guidelines on Heart Surgery Mean for Your Decision
Bringing it together. The EACTS guidelines on heart surgery are not rules imposed on you — they are the distilled experience of thousands of surgeons and trials, used to make sure your recommendation is proportionate, evidence-based and transparent. Whether your situation involves an aortic valve, blocked coronary arteries, or a question about TAVR versus open surgery, a guideline-based team should be able to show you the reasoning behind every option on the table.
Your role in the process. The guidelines themselves insist that decisions are shared: the team explains, you choose. Come to any consultation with your questions written down, ask which guideline applies to your case, and never feel that a second opinion is a betrayal — we consider it a normal, healthy part of deciding about heart surgery, and our team welcomes it.
Next step. If you have been diagnosed with a heart condition or told you may need surgery, the most useful thing you can do is talk it through with a qualified cardiac team rather than decide alone. Our multidisciplinary team, led by Dr Alejandro Molina, offers a free first video consultation where we explain what your studies show in plain words and outline the options — including, where the evidence supports it, the least invasive one. Reach out when you are ready; understanding your choices is the first part of the treatment.







