

Intercostal Nerve Pain After Heart Surgery
Intercostal nerve pain after surgery is common after heart procedures.
Recovery from heart surgery is a journey with many milestones, and one of the most confusing can be a sharp, burning or tingling pain along the ribs that appears days or even weeks after the operation. This is often intercostal nerve pain after surgery — irritation or injury of the small nerves that run between each rib and give sensation to the chest wall. It is common, usually temporary, and very different from the deep pressure of the original heart problem. This guide explains where these nerves sit, why cardiac surgery can disturb them, what the pain typically feels like, how long it usually lasts, and which treatments genuinely help, so you know what to expect and when to raise it with your team.
What Are the Intercostal Nerves?
The basic wiring of your chest wall. The intercostal nerves are twelve pairs of nerves that branch off the spinal cord in the upper and middle back. Each one travels forward in the space between two ribs — the intercostal space — supplying feeling to the skin, muscles and lining of the chest along its path. They are the reason you can feel a light touch, a tap or a burn anywhere on the rib cage. The first eleven are called intercostal nerves; the twelfth, which runs below the last rib, is the subcostal nerve, and it also sends branches to the skin of the abdominal wall.
Which nerves innervate intercostal muscles? The muscles between the ribs — the internal and external intercostal muscles that help the chest expand with each breath — are supplied by these same intercostal nerves. So one nerve carries two jobs: it lets you feel the chest wall and it drives the small muscle contractions that assist breathing. That dual role matters after surgery, because an irritated nerve can produce both odd sensations and a feeling of tightness when you take a deep breath.
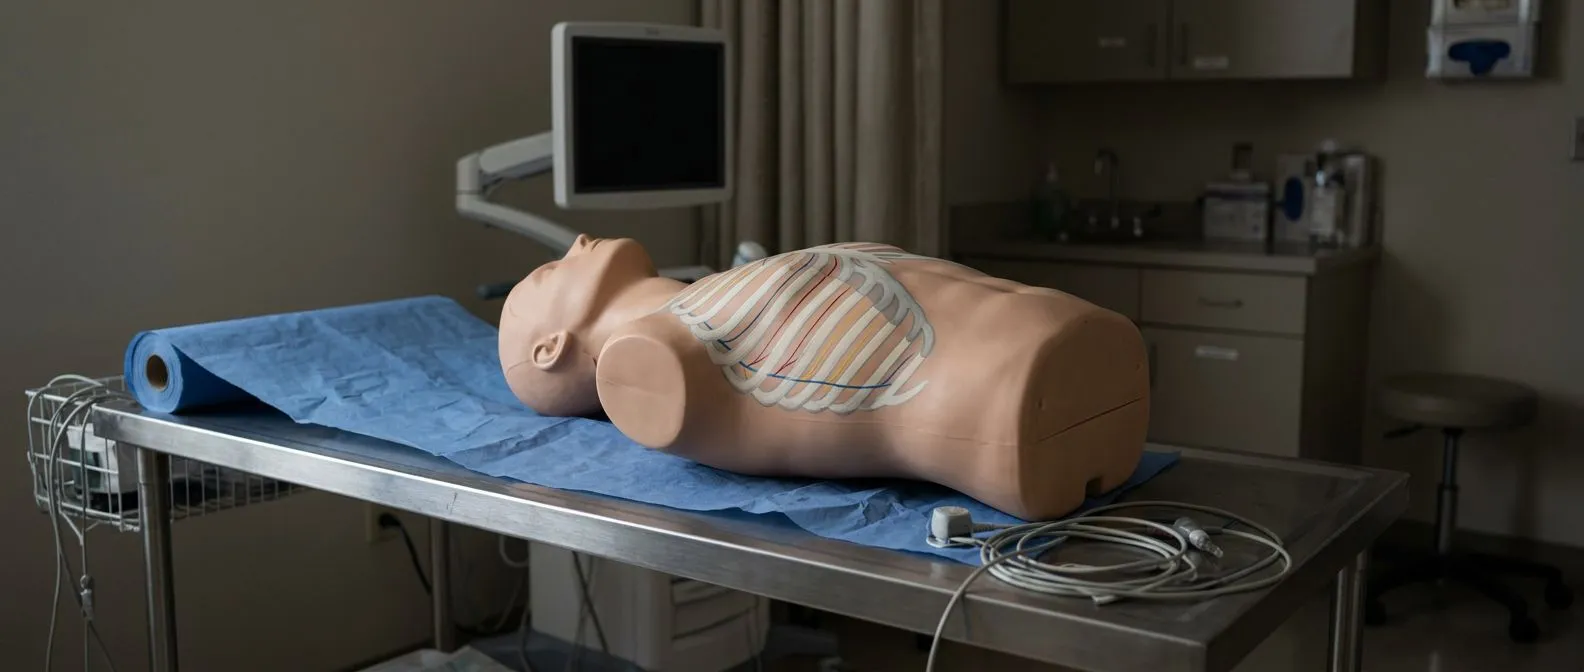
Why they matter in cardiac surgery. To reach the heart, a surgeon must pass through or around the chest wall, and the intercostal nerves sit directly in that path. Understanding their anatomy — a thoracic nerve running in a groove on the underside of each rib — explains most of the chest wall sensations patients describe during recovery. The Springer reference literature on thoracic nerves describes this course in detail, and it is the anatomical reason the topics in this article are so closely linked.
Why Does My Chest Hurt After Heart Surgery?
Two kinds of pain, one incision. After a heart operation there are really two pain systems at work. The first is somatic pain — the ordinary ache of healing bone, muscle and skin where the sternum (breastbone) was divided or the ribs were spread. The second is neuropathic pain, the electrical, burning or shock-like pain that appears when a nerve itself has been stretched, compressed or cut. Both can coexist, and telling them apart is the first step in managing nerve pain after cardiac surgery.
Chest wall pain after bypass surgery. In coronary bypass surgery and valve operations done through a sternotomy (the standard vertical incision down the breastbone), the chest is held open for several hours. Retractors press against the ribs, and the nerves that run in the grooves beneath them can be bruised. Patients who have surgery through a smaller side incision, called a thoracotomy, are especially prone to what is known as post thoracotomy nerve pain, because the nerves between the spread ribs take more direct pressure.
Why some patients feel it and others do not. Nerve injury is partly a matter of anatomy — nerve position varies slightly from person to person — and partly of the surgical approach. Minimally invasive and robotic approaches, which avoid spreading the ribs widely, tend to disturb less tissue along the way. In our practice, every case is reviewed by the multidisciplinary team against international practice guidelines before a recommendation is given, and the least invasive route is recommended only where the evidence supports it for that patient. The final decision is always the patient's.
What Does Intercostal Nerve Pain After Heart Surgery Feel Like?
The signature sensations. Intercostal nerve pain after heart surgery has a recognisable character. Patients describe it as burning, electric, stabbing or like a band tightening around the chest. It often follows the line of a rib, may wrap from the front toward the side or back, and can flare with a deep breath, a cough, a twist of the trunk or even the pressure of clothing. Some people feel patches of numbness or hypersensitivity where light touch — a shirt, a bedsheet — feels uncomfortable.
Radiating pain and why it can travel. Because each intercostal nerve runs a long, ribbon-like course around the body, irritation at one point can produce radiating pain felt along the whole strip it serves. You might feel it mainly near the scar, yet also notice rib pain after cardiac surgery toward the side or back on the same level. This is expected nerve behaviour, not a sign that something new has gone wrong — although it should still be mentioned at your follow-up.
Distinguishing it from cardiac pain. True cardiac pain is typically a pressure, heaviness or tightness deep in the centre of the chest, sometimes spreading to the arm, jaw or back. Patients sometimes report jaw pain or arm pain from the heart itself, which is why those patterns must never be dismissed after surgery. Chest wall nerve pain, by contrast, is usually sharper, tied to movement or touch, and reproducible when you press on a specific spot. In our consultations we take the time to explain what the studies and examinations actually show, in plain words, so patients can tell these two kinds of pain apart with confidence.
How Long Does Intercostal Nerve Pain Last?
The typical timeline. For most patients, how long intercostal nerve pain lasts follows a predictable curve. The first two to six weeks carry the strongest pain, driven largely by the healing sternum and inflamed tissues. Nerve-type sensations — burning, zaps, hypersensitivity — often peak in the first weeks and then steadily fade over two to three months. Many patients notice good days and bad days rather than a straight line, which is normal and not a sign of setback.
When pain persists. Chronic pain after heart surgery is usually defined as pain that is still present three months or more after the operation, and it affects a minority of patients. Persistent intercostal neuralgia after open heart surgery — the medical name for ongoing nerve pain along the ribs — is real and treatable, but it deserves a proper assessment rather than waiting it out indefinitely. Nerves recover slowly, so even persistent symptoms often continue to improve with time and the right treatment.
Factors that shape recovery time. Nerve pain recovery time varies with the surgical approach, the amount of retraction needed, whether the chest was opened centrally or through the side, diabetes and other conditions that affect nerve health, and how early the patient returns to gentle movement. In our team's experience, patients who walk early, breathe deeply and follow the sternal precautions they were given tend to describe a smoother, shorter course of chest wall discomfort. None of these factors guarantees an outcome — they simply shape the odds.
What Is the Anatomy of the Intercostal Space?
A layered structure. What is the anatomy of the intercostal space? Picture the gap between two ribs as a layered sandwich. From outside in: the external intercostal muscles, the internal intercostal muscles, and the innermost intercostal layer. Running in the plane between the internal and innermost layers, tucked into a groove on the underside of the upper rib, are three structures together called the neurovascular bundle — the intercostal vein, artery and nerve, in that order from top to bottom.
Why the position matters clinically. Because the nerve sits low in the space, procedures that pass needles or tubes through the chest wall are aimed just above the lower rib of a space, to avoid the bundle. The subcostal nerve, meanwhile, runs below the twelfth rib and continues forward toward the abdomen, which is why injury patterns after upper abdominal or lower chest procedures can mimic rib pain after cardiac surgery even though the source is different.
Where the nerve ends up. Near the front of the chest, each intercostal nerve turns forward and its anterior branch supplies the skin of the chest. Later branches wrap around toward the back. This map is exactly why nerve pain so often follows a curved line — a strip of skin served by one nerve is called a dermatome, and the strip between any two ribs corresponds to one segment. Knowing your pain follows a dermatome is a strong clue it is nerve-related rather than coming from the heart or the sternum itself.
Is It Nerve Pain or a Surgical Complication?
Reassuring signs. Certain features point toward ordinary nerve and wound healing: pain that changes with position or movement, tenderness when you press along the scar or a rib, electric or burning qualities, and gradual improvement week by week. Clicking or movement at the sternum with discomfort is common while the bone knits. These patterns, while unpleasant, fit the expected picture of a healing chest.
Warning signs that need prompt attention. Some symptoms must never be attributed to nerve healing without a check. Seek urgent care if any of the following appear:
- Pressure or heaviness in the centre of the chest — crushing chest pain, especially with sweating, nausea or breathlessness, must be treated as a cardiac symptom until proven otherwise.
- Fever, redness or discharge from the incision — these suggest wound infection or deep sternal problems that need immediate assessment.
- New or worsening breathlessness — fluid around the lung or heart can develop after surgery and does not behave like nerve pain.
- Sudden tearing chest pain between the shoulder blades or in the back — this pattern requires emergency evaluation.
What a proper assessment involves. Distinguishing nerve pain from complications usually takes a focused history, an examination of the scar and chest wall, and sometimes an ECG, chest X-ray or echocardiogram. In our team, patients can raise exactly these questions in the free first video consultation: we get to know the patient, talk through the symptoms, and say which studies are genuinely needed so no unnecessary ones are ordered. When the answer is unclear, we would rather check than reassure without evidence.
Intercostal Nerve Block After Surgery: How Does It Help?
What a block actually is. An intercostal nerve block is an injection of local anaesthetic — sometimes with a mild anti-inflammatory drug — placed beside the nerve in one or more intercostal spaces. The anaesthetic temporarily switches off the pain signals travelling from that strip of chest wall to the brain. Blocks can be placed during the operation itself, in the recovery unit, or later as a treatment for established pain.
What the evidence and practice show. Used around the time of chest surgery, blocks can reduce opioid requirements and make deep breathing and coughing more comfortable, which matters for lung recovery. Research on regional anaesthesia and renal and autonomic effects, such as the review published by Karger, shows how closely pain control, the nervous system and organ function interact — one reason pain management after cardiac surgery is planned rather than improvised. Blocks are also used diagnostically: if an injection relieves the pain, that confirms the nerve as the source.
What is the most common complication of intercostal nerve block? The most common complication is a pneumothorax — air leaking into the space between the lung and chest wall if the needle passes too deeply — along with more ordinary effects like transient numbness or, rarely, slight bleeding at the site. This is why blocks are performed by clinicians who do them regularly, with ultrasound or anatomical landmarks guiding the needle. The risk is low, but it is not zero, and it belongs in any honest conversation about the technique.
Intercostal Pain Relief Options: What Actually Works?
A layered approach. No single treatment removes intercostal nerve pain after surgery on its own; effective relief usually stacks several modest measures. The aim of pain control is not just comfort — it is enabling the deep breathing, walking and sleep that drive recovery. Most patients move through the options below in some combination, guided by their surgical team:
- Simple analgesics and anti-inflammatories — paracetamol and, where suitable for the patient, anti-inflammatory medicines form the base layer for chest wall pain.
- Neuropathic medicines — drugs originally developed for epilepsy or depression, such as gabapentin or duloxetine, are specifically effective for nerve-type pain and are prescribed at low doses, titrated up.
- Targeted injections — intercostal blocks or, for stubborn cases, longer-acting regional techniques can break a pain cycle that oral medicine alone cannot.
- Movement and positioning — graded walking, breathing exercises, sleeping propped up and avoiding twisting loads on the sternum all reduce flare-ups.
Why opioids are not the long answer. Strong opioid painkillers have a place in the first days after surgery, but they do not treat neuropathic pain well, they dull breathing, and dependence becomes a risk with prolonged use. If you find yourself needing them weeks after the operation, that is a signal to revisit the diagnosis rather than increase the dose.
Matching treatment to the pain type. Neuropathic chest pain after surgery responds to a different toolkit than muscular or bone pain, which is why describing your symptoms precisely — burning versus aching, skin sensitivity, movement triggers — genuinely changes the treatment you are offered. In our consultations, we encourage patients to keep a simple note of when the pain spikes and what they were doing; that pattern is often more informative than the pain score alone.

Managing Nerve Pain After Cardiac Surgery at Home
Pacing, not pushing. The chest wall forgives overdoing it slowly and punishes it quickly. In the first weeks, respect sternal precautions — no pushing, pulling or lifting with the arms, no driving until your team clears you — and build walking gradually. A sternal support pillow for coughing or sneezing protects the healing bone and, indirectly, the irritated nerves around it.
Dress and sleep with the nerves in mind. Loose, soft clothing over the scar, a pillow wedged under the painful side when sleeping on it is intolerable, and propping the upper body for the first weeks all reduce mechanical provocation of the healing nerves. Heat — a warm shower or a covered heat pad, never directly on a fresh incision — relaxes the intercostal muscles and often eases the tight, band-like quality of the pain.
The mind–nerve connection. Persistent pain is amplified by poor sleep and anxiety, and the months after heart surgery are rarely restful. Gentle relaxation breathing, short daylight walks and keeping a regular sleep window measurably lower pain intensity for many patients. Autonomic research in cardiology, including work on heart rate variability reviewed in the Russian Journal of Cardiology, underlines how tightly the nervous system's state and cardiac symptoms are linked — calming one often helps the other. If low mood or poor sleep is fuelling the pain, say so at your follow-up; it is a medical issue, not a character flaw.
When Should You Tell Your Surgical Team?
Any new pain deserves a mention. Patients sometimes minimise symptoms, not wanting to bother the team. Do not. Mention pain that is worsening rather than easing, pain that changes character, pain accompanied by numbness that spreads, or pain that stops you sleeping or doing your breathing exercises. Early adjustment of a pain plan is far easier than rescuing a patient from a well-established chronic pain cycle.
Specific triggers for a call. Contact your team promptly for pain with fever, pain with new breathlessness, increasing redness or swelling at the incision, a sternum that feels unstable or clicks painfully, or any of the cardiac warning signs listed earlier. For everything else — the burning rib line, the tender spot beside the scar, the zaps when you twist — the routine follow-up is the right place, and a short symptom diary makes that conversation far more productive.
Second opinions are normal. If your pain is persistent and you are unsure whether the plan you have is the right one, seeking another view is a reasonable and respected step, not a betrayal of your surgeon. We encourage second opinions and treat seeking one as a normal part of deciding about heart surgery and its recovery. Dr Molina trained in cardiothoracic surgery at the Universidad de Guadalajara, in cardiac, minimally invasive, robotic and structural surgery at the University of Montreal, and in structural cardiology and TAVR at CHU Bordeaux, and the team also trained at Jena, Bad Berka and Buffalo — but we still regard an informed, questioning patient as the best kind.

Rib Pain After Cardiac Surgery Versus Sternotomy Pain
Two patterns, two causes. Nerve pain after sternotomy is usually felt along the vertical breastbone incision and the strips of chest just beside it, worse with arm movement, coughing or rolling in bed, because those actions load the healing bone and stretch the nearby nerves. Rib pain felt more toward the side or back — especially after surgery through a side incision — fits the pattern of direct nerve irritation from retraction. Locating your pain precisely, front versus side, helps your team identify which structure is complaining.
Lingering rib pain after surgery. A tender spot over one rib that persists for months, worsened by pressure or deep breaths, can reflect a small intercostal muscle strain, an inflamed rib junction, or a genuinely injured nerve. Examination usually separates these: muscle and joint pain is tender and mechanical, while nerve pain adds burning, electric or skin-sensitivity qualities in a strip pattern. Both improve with time; the treatments that help differ, which is again why precision matters.
Intercostal nerve damage symptoms worth knowing. Classic intercostal nerve damage symptoms are numbness in a band of chest skin, a burnt or raw feeling without an obvious cause, skin that flinches at light touch, and occasional sudden electric jabs. Weakness of the chest wall muscles is rare and usually subtle. If your symptoms fit this picture, tell your team in exactly those words — "it burns along the rib, and the skin is sensitive" describes a nerve; "it aches when I press" describes something else, and both are useful.
Recovering Well From Intercostal Nerve Pain After Surgery
The realistic picture. Most patients find that intercostal nerve pain after surgery follows the same arc: intense in the first weeks, patchy by the second month, and a faint memory or an occasional twinge by the third to sixth month. A minority experience longer-lasting neuropathic pain, and that minority deserves active treatment, not endurance. Recovery is rarely a straight line, and a bad week after three good ones does not erase progress.
Your part in it. Walk daily, breathe deeply on schedule, protect the sternum, take prescribed neuropathic medicines as directed rather than sporadically, and report changes honestly. Keep follow-up appointments even when things are going well — they are where small problems are caught while still small. Bring your questions written down; a prepared patient gets a more complete answer in the same ten minutes.
Getting the right team behind you. Chest pain after heart surgery has many possible sources, and the safest path runs through a team that examines, investigates and explains rather than guesses. Every case in our practice is reviewed by the multidisciplinary team of cardiac surgeons led by Dr Alejandro Molina, with consulting rooms in Guadalajara, Querétaro and Hermosillo, and patients receive a clear proposal with the alternatives before any decision is made. If you are unsure whether your chest wall pain is normal healing or something that needs attention, discuss your situation with a qualified cardiac team — you can book a consultation rather than self-diagnose, and you may be surprised how much relief comes simply from understanding what the pain is.






