

Smaller Incisions in Heart Surgery: What Changes for You
Smaller incisions heart surgery means faster recovery and less pain.
If you or someone you love has been told that heart surgery is needed, one of the first questions is usually about the cut. For decades, heart operations meant a long incision down the middle of the chest and a saw through the breastbone. Today, many valve and other cardiac procedures can be done through smaller incisions heart surgery teams use with long instruments and video cameras — sometimes less than five centimetres long. This guide walks through what that actually means for you: how these operations are done, what the benefits and risks really are, how recovery differs, and how to decide whether a smaller incision is the right choice for your specific heart problem.
What Are Smaller Incisions Heart Surgery Actually Involves
Traditional open heart surgery uses a full sternotomy: an incision of 20 to 25 centimetres down the centre of the chest, with the breastbone (sternum) divided so the surgeon can reach the heart directly. It is a proven, safe approach used every day around the world.
Minimally invasive cardiac surgery replaces that large opening with one or more small cuts, usually between the ribs on the right or left side of the chest, or a short partial breastbone incision. The surgeon works through these openings using long, thin instruments and a high-definition camera that shows the heart on a monitor. The heart is still stopped and protected during the operation, and a heart-lung machine is still often used — what changes is the doorway, not the operation itself.
Our team performs conventional, minimally invasive, robotic and transcatheter procedures, and in every case we review the option carefully before recommending the less invasive route, because it is not automatically better for every patient.
What Is a Small Incision Called?
Patients often hear several names used for the same idea, and it helps to know the vocabulary before your consultation.
- Keyhole heart surgery: a common everyday term for any operation done through small cuts between the ribs, with instruments and a camera replacing direct vision.
- Endoscopic heart surgery: surgery performed entirely with a camera and long instruments, without the surgeon's eyes looking directly at the heart.
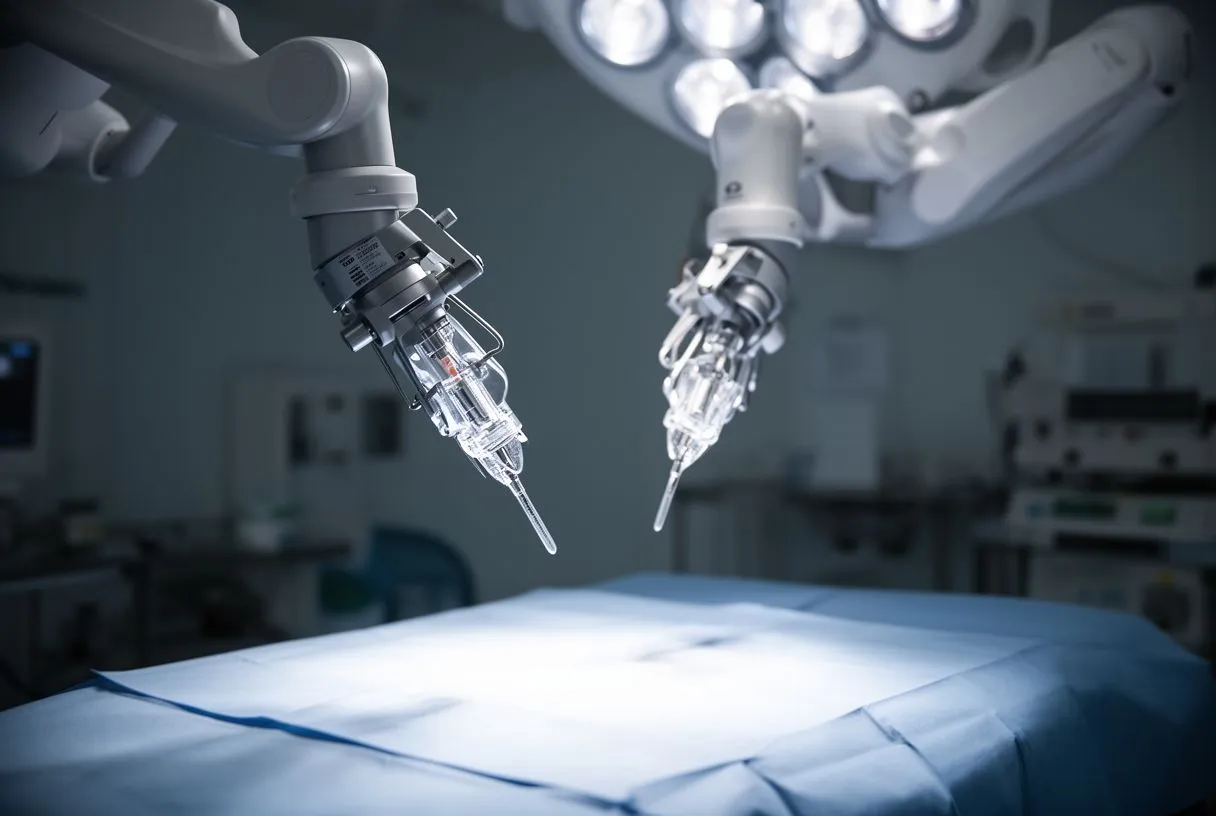
- Robotic heart surgery small incisions: the surgeon controls a robotic platform from a console; the robot's arms hold instruments that enter through tiny cuts, allowing very precise movements.
- Transcatheter procedures: no surgical incision at all — a new valve is delivered through a thin tube, usually from an artery in the groin. TAVR (transcatheter aortic valve replacement) is the best-known example.
There are also partial sternotomy incisions with names you may hear: a J-incision, which opens only the lower or upper part of the breastbone, and an Inverted T-incision, which divides the breastbone in a T-shaped pattern. These sit between a full sternotomy and a true keyhole approach and are chosen when the surgeon needs slightly more room without the full opening.
How Smaller Incisions Heart Surgery Works Step by Step
Understanding what happens on the day helps take away some of the fear of the unknown.
Before the operation. You will have imaging studies — an echocardiogram (an ultrasound of the heart), a CT scan and sometimes a catheter study — that let the surgical team map your anatomy and plan the exact incision site. In our practice, the first contact is a free video consultation: we get to know you, talk through your condition, and tell you which studies are still needed so that no unnecessary ones are ordered.
During the operation. You are under general anaesthesia as in any heart operation. The surgeon makes the planned small incision, separates a rib space carefully or makes a short breastbone cut, and inserts the camera and instruments. The heart may be stopped with the help of a heart-lung machine connected through smaller vessels, or in some cases the operation is done on the beating heart. The valve or vessel is then repaired or replaced through that working window, and everything is closed with the incision itself — usually 4 to 8 centimetres.
Right after surgery. You go to an intensive care unit for close monitoring, typically for a shorter time than after a full sternotomy, because there is no divided breastbone to worry about.
Types of Less Invasive Heart Surgery Available Today
Not every heart problem has a less invasive answer, but the list has grown considerably.
Minimally invasive valve surgery is the most established. Mitral valve repair (fixing the valve between the upper and lower left chambers) through a right-chest incision or robotically is performed routinely in experienced centres. Aortic valve replacement through a small right-chest cut or a partial breastbone incision is also well developed.
Small incision bypass surgery is possible in selected patients — one or two blocked coronary arteries can be bypassed through a left-chest incision. Multi-vessel bypass in a patient with several blockages is usually still done through a full sternotomy, because direct access and safety come first.
TAVR replaces the aortic valve through an artery, with no chest incision at all. It is generally reserved for patients whose age, anatomy or overall health makes open surgery higher risk, and the decision between TAVR and surgical replacement depends on careful review of your specific anatomy and risk profile.
Dr Molina performed the first robotic mitral valve repair in the Ángeles Health System and the first robotic heart surgery in Guadalajara, so our team has direct experience with the full range of these approaches.
Minimally Invasive Valve Surgery Benefits That Matter to Patients
The appeal of a smaller cut is not only cosmetic — several benefits are supported by clinical experience and published evidence.
Less pain and less blood loss. With no divided breastbone, there is less tissue trauma. Patients generally need less pain medication in the first days, and smaller incisions tend to bleed less.
Lower risk of wound complications. The breastbone takes weeks to knit back together, and in patients with diabetes or lung disease, sternal wound infections are a recognized risk of full sternotomy. Avoiding the bone division removes that specific risk category.
Faster return to normal life. Because there is no sternum to heal, driving, working and gentle exercise generally resume sooner than after a full sternotomy, where surgeons often advise limiting lifting and pushing for six to eight weeks to protect the healing bone.
Smaller, less visible scars. A small scar tucked under the right breast or on the side of the chest is far less noticeable than a central chest scar. For many patients — especially younger ones — this matters more than they expect to admit out loud.
The European Society of Cardiology guidelines on valve disease recognize that both minimally invasive surgical replacement and TAVR are established options for aortic valve disease, with the choice driven by patient age, anatomy and surgical risk rather than by preference alone (European Society of Cardiology).
Smaller Incision vs Open Heart Surgery: Which Is Right for You?
This is the decision that matters most, and it deserves an honest comparison.
What favours the smaller incision. Younger, otherwise healthy patients with an isolated valve problem — a mitral valve that can be repaired, or an aortic valve needing replacement — are often the best candidates. Good lung function matters, because working between the ribs requires one lung to be temporarily deflated during the operation.
What favours the traditional approach. Multiple bypass grafts, emergency operations, heavily calcified vessels, poor lung function, previous chest surgery with scarring, or certain anatomical problems can all make a full sternotomy the safer choice. A larger incision is not "worse" surgery — it is simply the right doorway for certain operations.
How the decision should be made. The trade-offs are real on both sides: a smaller incision can mean a longer operation time and requires a surgeon and team with specific experience in these techniques. Every case in our practice is reviewed by the multidisciplinary team against international practice guidelines before a recommendation is given, and you receive a clear proposal with the alternatives — the final decision is always yours.
Are Small Incision Heart Surgeries Safe?
Safety is the right question to ask, and the honest answer has two parts.
In experienced hands, yes. Major clinical trials and large registries of minimally invasive valve surgery have shown outcomes comparable to traditional sternotomy for the right patients, with the added benefits described above. The key phrase is "in experienced hands" — technique and team experience are the strongest predictors of a good result.
The risks to know about. Any heart operation carries risks of bleeding, stroke, infection and arrhythmia (irregular heartbeat). Minimally invasive surgery adds the risk of converting to a full sternotomy if the surgeon cannot complete the operation safely through the small opening — something a good team plans for from the start, not improvises. Research on structured, technology-supported care after surgery shows that careful follow-up and monitoring meaningfully improve outcomes for patients after cardiac procedures (The effectiveness of mobile-health technology-based health behaviour change or disease management interventions for health care consumers: a systematic review).
What we watch for. In our consultations we take the time to explain what the studies actually show, in plain words, and we are explicit about the situations where we would convert to a larger incision — because you deserve to know that before, not after.
How Long Do Small Incisions Take to Heal?
Recovery is where smaller incisions change your life most visibly.
The incision itself. A small chest incision typically closes within two weeks, and the deeper tissue layers continue healing over the following weeks. Compare this with a sternotomy, where the breastbone itself needs roughly eight to twelve weeks to become solidly healed and movement restrictions apply throughout that period.
Returning to activities. Many patients who have had minimally invasive valve surgery are walking comfortably within days, driving within two to three weeks, and back to office work within three to four weeks. Heavy lifting takes longer, and your surgical team will give you specific milestones rather than a single date. Recent research tracking heart function during and after treatment shows that careful monitoring of the heart's recovery gives a clearer picture of long-term outcomes (Simultaneous Left Ventricular Volume and Strain Changes During Chemotherapy Associate With 2‐Year Postchemotherapy Measures of Left Ventricular Ejection Fraction).
The first weeks at home. Expect tiredness — heart surgery is major surgery regardless of incision size. Sleep, gentle walking, and a structured cardiac rehabilitation program matter more than the incision for how quickly you feel like yourself again.
Minimally Invasive Heart Surgery: Cost and Travel Considerations
For patients who travel from other parts of Mexico or from abroad, practical questions are as important as clinical ones.
What affects the cost. The type of procedure, whether robotic technology is used, the length of hospital stay, and whether the operation is on the heart's valves, coronary arteries or aorta all shape the final figure. A shorter hospital stay after minimally invasive surgery can offset part of the higher technology cost, but you should always ask for a complete, written estimate before deciding anything.
Planning for travel. If you are coming from outside the region, plan to arrive with time for a face-to-face evaluation before surgery and to stay nearby during the early recovery period. Flying is generally not advisable in the first days after heart surgery, and your team will advise on timing based on your recovery.
Insurance and documentation. Ask whether your insurance covers the specific procedure and the hospital, and request your complete medical records and operative report to take home. Our consulting rooms are in Guadalajara, Querétaro and Hermosillo; if you are travelling from farther away, ask how follow-up can be planned so the trip is as short as safely possible.
Choosing a Heart Surgeon for Smaller Incisions
When you are comparing options, the surgeon's experience with the specific technique matters more than almost anything else on the list.
Questions worth asking directly. How many of these specific operations does the surgeon perform each year? What is the conversion rate to full sternotomy? What is the team's protocol if something changes mid-operation? A confident, experienced surgeon will answer these without hesitation.
Training and breadth matter. A surgeon trained in multiple approaches — conventional, minimally invasive, robotic and transcatheter — is more likely to recommend the right approach for you rather than the one they happen to perform. Dr Molina trained in cardiothoracic surgery at the Universidad de Guadalajara, in cardiac, minimally invasive, robotic and structural surgery at the University of Montreal, and in structural cardiology and TAVR at CHU Bordeaux, and the team has trained further at Jena, Bad Berka and Buffalo.
Second opinions are normal. We encourage second opinions and treat seeking one as a normal, healthy part of deciding about heart surgery — no reputable team should make you feel otherwise. If a second opinion confirms the plan, you proceed with confidence; if it raises questions, those questions deserve answers before you commit.

Smaller incisions heart surgery has genuinely changed what recovery looks like for many patients — less pain, no divided breastbone, and a faster return to ordinary life. But the incision is the last thing to decide and the first thing to stop worrying about: what determines your outcome is matching the right operation to your specific heart, your anatomy and your overall health, in the hands of an experienced team. If you have been told you need valve surgery or another cardiac procedure, bring your questions to a qualified cardiac team and ask openly about every option — including TAVR, robotic surgery and the traditional approach — before deciding. The right first step is a consultation, not a self-diagnosis, and asking is never a bad beginning.






