

The Atrium Explained: How Your Upper Heart Chambers Work
Learn how heart atrium function powers your circulatory system.
Your heart has four chambers, and the two at the top — the atria — are easy to overlook. Yet without healthy heart atrium function, the entire circulatory system loses its rhythm and efficiency. Whether you are preparing for a cardiac consultation, supporting a family member through a diagnosis, or simply trying to understand a report that mentions your "left atrium," this guide walks you through what these upper chambers do, how they can falter, and what treatments look like in real life. We will keep the language plain and define every medical term as it appears, so nothing here requires a cardiology degree to follow.
What Is Heart Atrium Function?
The word atrium comes from Latin and means "entry hall" — a fitting name, because each atrium is the entry hall where blood arrives before being pushed into the heart's main pumping chambers. Your right atrium collects oxygen-poor blood returning from your body; your left atrium collects freshly oxygenated blood returning from your lungs. In each case, the atrium acts as both a receiving reservoir and a booster pump.
Why does a "booster pump" matter? Because blood is lazy. It arrives in the atria at low pressure, having travelled through veins or lung vessels, and it needs a final nudge to fill the ventricles — the powerful lower chambers that drive circulation to the lungs and the rest of the body. The atria provide that nudge with a gentle contraction sometimes called the "atrial kick," which tops up ventricular filling right before each heartbeat. Losing that kick, as happens in certain rhythm disorders, can noticeably reduce how well the heart performs, especially in older adults or people with stiff ventricles.
Understanding heart chamber anatomy in this way reframes the atria: they are not passive waiting rooms but active, precisely timed components of the cardiac cycle — the sequence of filling and emptying that repeats with every beat, roughly 60 to 100 times a minute at rest. The National Institutes of Health describes the atria's role in coordinating filling as fundamental to normal cardiac output, and research into the worldwide burden of cardiovascular disease — including a Global Burden of Cardiovascular Diseases and Risk Factors, 1990-2019: Update From the GBD 2019 Study — shows why protecting these chambers matters at a population scale: conditions that disturb atrial structure and rhythm are among the most common heart problems worldwide.
Heart Chamber Anatomy: The Four Rooms of Your Heart
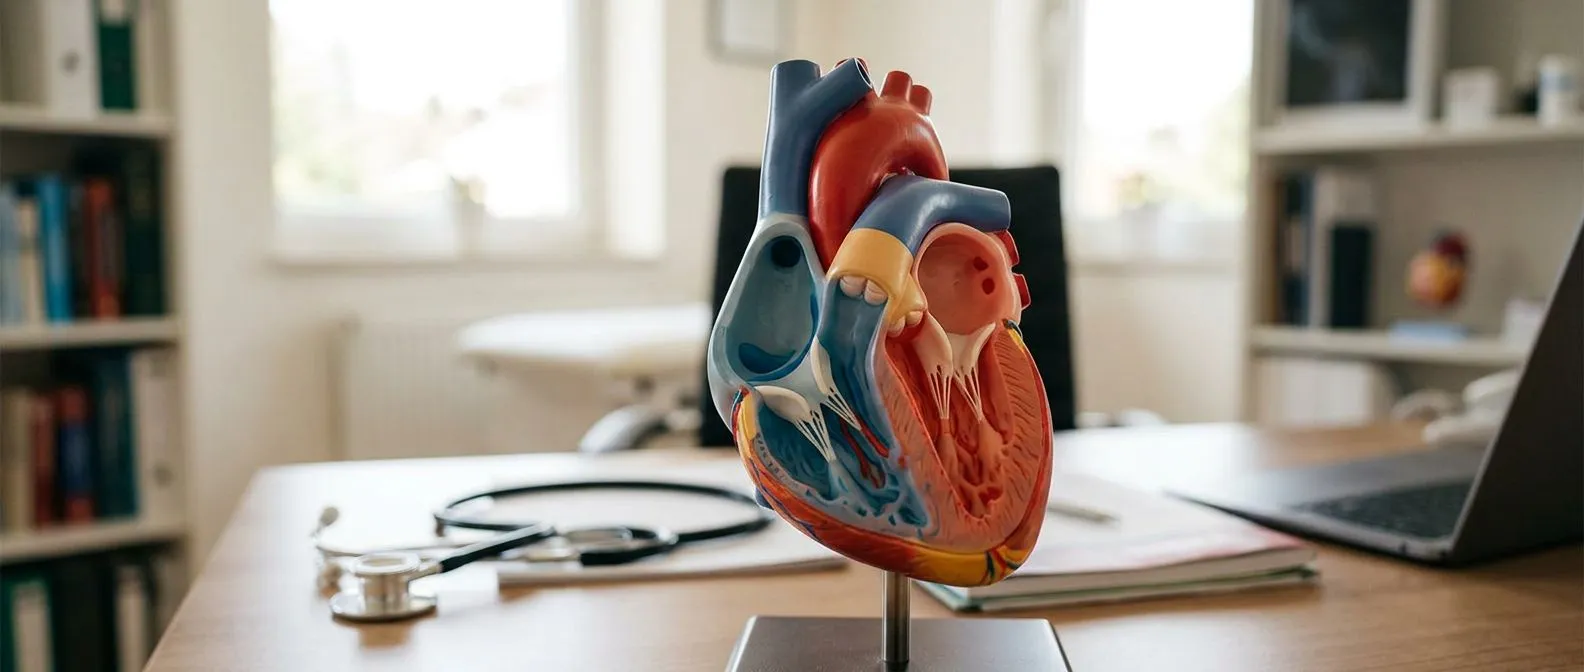
Two atria, two ventricles, four valves. The heart's chambers are arranged in a matched pair. The right atrium and right ventricle handle blood heading to the lungs; the left atrium and left ventricle handle blood heading to the body. Between each atrium and its ventricle sits a one-way valve — the tricuspid on the right, the mitral on the left — that opens to let blood flow downward and slams shut to stop it from flowing backward. These heart valve–atrium connections are central to how the chambers stay organised and efficient.
The walls between chambers. A muscular wall called the interatrial septum separates the two atria, and a thicker wall separates the two ventricles. Before birth, a small opening in the septum (the foramen ovale) allows blood to bypass the lungs; it normally seals shut shortly after birth. When it does not, or when a hole develops for other reasons, blood can shunt between the atria — a topic we return to in the section on atrial septal defects.
For anyone who wants to visualise this, think of the heart as a two-storey house with a right side and a left side. Blood always moves upstairs-to-downstairs (atrium to ventricle) and right-side-to-lungs-to-left-side, never backward and never across the dividing walls in a healthy heart. Advanced imaging such as Cardiac CT or Cardiac Magnetic Resonance can map these chambers in extraordinary detail, and the interpretation of such scans is standardised worldwide — the Society for Cardiovascular Magnetic Resonance publishes task-force guidelines so that measurements of chamber size and function mean the same thing in Guadalajara as they do in Boston.
Right Atrium Blood Flow: From Body to Lungs
Where the blood comes from. Right atrium blood flow begins with two large veins. The superior vena cava delivers blood from your head, arms and upper body into the top of the right atrium, while the inferior vena cava delivers blood from the legs and abdominal organs into its lower portion. A smaller but important contributor is the coronary sinus, which returns blood that has already supplied the heart muscle itself. All of this oxygen-poor, bluish blood pools briefly in the right atrium.
Where the blood goes. When the right atrium contracts, blood crosses the tricuspid valve into the right ventricle, which then pumps it into the pulmonary artery and out to the lungs to pick up oxygen and release carbon dioxide. The right atrium also does something subtle but vital: it acts as a pressure sensor. Stretch receptors in its walls tell the body how full the circulatory system is, influencing hormone release and fluid balance — one reason physicians pay close attention to atrial pressure monitoring during Cardiac catheterisation: advantages and disadvantages are always weighed carefully before such invasive testing is recommended.
Certain structural problems can disrupt this tidy circuit. Narrowing of the tricuspid or pulmonary valve, elevated lung-vessel pressures, or conditions like Carcinoid Heart Disease — in which tumour-produced hormones scar the right-sided valves — can all raise pressure inside the right atrium and cause it to enlarge over time. In emergencies such as massive pulmonary embolism, surgeons sometimes perform a Balloon Aortic Valvuloplasty-style catheter intervention on other valves or use an intra-aortic Balloon pump as a Bridge to Recovery; the principle is always the same — relieve the strain so the chambers, including the atria, can rest and recover.
Left Atrium Oxygenated Blood and the Pulmonary Veins
The left atrium is the heart's "fresh air" chamber. Four pulmonary veins — two from the left lung, two from the right — deliver bright red, oxygen-rich blood directly into it. This is the only place in the body where veins carry oxygenated blood in an adult, which is why the pulmonary veins left atrium connection is anatomically special. From there, blood passes through the mitral valve into the thick-walled left ventricle, the pump that supplies the entire body.
Why the left atrium is clinically important. Because it sits at the crossroads of lung circulation and systemic circulation, the left atrium is sensitive to pressure changes on both sides. A stiff, failing left ventricle pushes pressure backward into the left atrium; lung disease does something similar from the other direction. Over months and years, that pressure stretches the atrial wall, and a stretched atrium is prone to rhythm disturbances — particularly atrial fibrillation, which we will examine shortly. An enlarged left atrium is therefore not a diagnosis by itself but a signal that something upstream or downstream deserves attention.
Surgeons know the left atrium intimately. Procedures ranging from mitral valve repair to the Cabrol Technique — a surgical method used in complex aortic root surgery — require precise handling of this chamber and its delicate relationship with the oesophagus, the aorta, and the pulmonary veins. For patients with Bicuspid aortic valves (valves formed with two leaflets instead of three) undergoing aortic work, the left atrium often lies directly in the operative field, and careful planning with imaging keeps the operation safe.
Atrium vs Ventricle Function: What's the Difference?
Pressure and power. The clearest way to understand atrium vs ventricle function is to think of a hand pump feeding a fire hose. The atria are the hand pumps: low-pressure, thin-walled, and responsible for topping off the ventricles. The ventricles are the fire hoses: thick-walled, high-pressure, and responsible for actually moving blood to the lungs and the body. The right ventricle works at relatively low pressure against the lungs; the left ventricle works at much higher pressure against the whole arterial system.
Contribution to filling. In a healthy heart at rest, the ventricles fill substantially even before the atria contract — the atrial kick adds roughly the final quarter of ventricular filling. That contribution becomes disproportionately important when the heart is stiff (as with age or hypertrophy) or when a person exercises and the heart rate rises. This is why patients who lose atrial contraction may feel fine at rest but become unusually short of breath climbing stairs.
Why the distinction matters for treatment. Knowing which chamber is the problem changes everything. A weak ventricle may need medications, a stented artery treated with a Bare-metal Stent or newer drug-eluting device, or in advanced cases a ventricular assist device used as a Bridge to Transplant. A diseased atrium, by contrast, most often presents as a rhythm problem or a source of clots, and treatment focuses on restoring rhythm, preventing stroke, or correcting structural defects. The diagnostic journey usually starts non-invasively — echocardiogram, ECG, Cardiac CT or magnetic resonance — and a Cardiac Imaging Specialist interprets these studies to pinpoint the culprit chamber.
Normal Heart Rhythm Atrium and the Electrical Conduction System
Every heartbeat begins with electricity, and the heart's natural pacemaker — the sinoatrial (SA) node — lives in the right atrium, near the entrance of the superior vena cava. A cluster of specialised cells, it fires an impulse roughly 60 to 100 times a minute at rest, and this impulse spreads across both atria in a wave, causing them to contract together. A normal heart rhythm atrium is one in which this wave travels smoothly and uniformly.
The relay to the ventricles. After sweeping the atria, the impulse reaches the atrioventricular (AV) node, a brief electrical "delay station" between the atria and ventricles. That delay is deliberate: it buys the ventricles time to fill completely before they contract. The impulse then races down specialised fibres into the ventricles, triggering the powerful squeeze that sends blood on its way. The entire sequence — atrial contraction, microsecond delay, ventricular contraction — defines the cardiac cycle atrium role and produces the familiar "lub-dub" heard through a stethoscope.
When this conduction system heart circuitry falters, the results range from harmless to serious. Extra beats arising in the atria (premature atrial contractions) are extremely common and usually benign. Slowing of the SA node can cause fatigue and dizziness and may eventually require a pacemaker. And when the organised wave degenerates into electrical chaos, the result is atrial fibrillation — the most common sustained rhythm disorder in adults and the subject of the next section.
Atrial Fibrillation Symptoms: When the Atria Misfire
What it feels like. Atrial fibrillation symptoms vary enormously. Some people feel a racing, fluttering, or "flopping fish" sensation in the chest; others notice only unexplained fatigue, breathlessness on exertion, or lightheadedness. A troubling minority feel nothing at all and discover the condition incidentally on an ECG. During atrial fibrillation, the atria stop contracting and instead quiver — several hundred disorganised impulses per minute — while the ventricles receive an irregular, often rapid series of signals.
Why it matters beyond symptoms. Because the fibrillating atria do not squeeze, blood can pool and stagnate, most dangerously in a small pouch of the left atrium called the left atrial appendage. Stagnant blood tends to clot, and a clot that escapes can travel to the brain and cause a stroke. This is the single most important reason atrial fibrillation is taken seriously even when it causes no symptoms, and why blood-thinning medication is a cornerstone of management for many patients.
How it is treated. Management is layered and highly individual:
- Rate and rhythm control: medications to keep the ventricles from beating too fast, and sometimes procedures such as electrical cardioversion or catheter ablation to restore a normal rhythm.
- Stroke prevention: anticoagulants (blood thinners) or, in selected patients, a small implantable device that occludes the left atrial appendage.
- Addressing underlying causes: treating sleep apnoea, thyroid disease, hypertension, and valve problems reduces episodes, because an irritated atrium is more likely to fibrillate.
Diagnostic confirmation may involve Blood Cultures if infection is suspected as a trigger, a prolonged rhythm monitor, or an echocardiogram to assess atrial size and ventricular function. The good news is that atrial fibrillation today is a manageable condition — outcomes improve markedly when it is detected early and treated consistently.

Enlarged Atrium Causes and Atrial Enlargement on Echocardiogram
The usual suspects. Enlarged atrium causes fall into a handful of categories: long-standing high blood pressure, leaky or narrowed valves (especially the mitral valve, which sits directly between the left atrium and ventricle), lung diseases that raise pulmonary pressures, congenital defects, and — crucially — atrial fibrillation itself, which begets enlargement just as enlargement begets fibrillation. Obesity and chronic kidney disease also contribute. In other words, the atrium usually enlarges because it is being asked to work against resistance, hold too much volume, or beat chaotically.
How enlargement is found. Atrial enlargement on echocardiogram is one of the most common incidental findings in cardiac imaging. The sonographer measures the atrium's diameter and volume, and modern guidelines define normal ranges by body size and sex. A mildly enlarged atrium might warrant only follow-up; a significantly enlarged one triggers a search for the cause. Because measurements matter, high-quality imaging matters — which is why established practices invest in standardised protocols and experienced readers.
What enlargement means for you. An enlarged atrium is best understood as a barometer, not a verdict. It tells your cardiologist that pressure or volume has been elevated for some time, and it refines decisions about treatment — for example, the likelihood that a rhythm-control strategy will succeed, or the urgency of fixing a leaky valve. It also informs surgical planning: in minimally invasive atrial surgery, chamber size and geometry help determine whether a less invasive approach is feasible. The honest answer to "is this dangerous?" is always: it depends on the cause, and that cause is what your cardiac team will investigate.
Atrial Septal Defect Repair and Interatrial Septum Function
The interatrial septum function is elegantly simple: keep the two atrial bloodstreams separate. Oxygen-poor blood belongs on the right, oxygen-rich blood on the left, and the thin muscular wall between them enforces that division. But in roughly a quarter of the population, a small flap-like opening (patent foramen ovale) persists from fetal life without causing problems; in a smaller number, a true hole — an atrial septal defect — allows blood to cross continuously.
Why a hole matters. When the hole is significant, blood flows from the higher-pressure left atrium into the right, adding volume to the right-sided chambers and the lungs. Over years this can enlarge the right atrium and right ventricle, raise lung pressures, and occasionally cause reversal of the shunt. Some people reach adulthood without symptoms; others notice breathlessness, frequent respiratory infections, or unexplained fatigue that traces back to the defect.
How repair works. Atrial septal defect repair has become one of cardiac medicine's quiet success stories. Many defects — particularly the common "secundum" type — can be closed with a catheter-based device inserted through a vein in the groin, avoiding open-heart surgery entirely. Larger or unusually positioned defects may require surgical patch closure, sometimes via a minimally invasive approach with a small chest incision. Recovery from device closure is typically days to weeks; surgical recovery is measured in weeks to a few months. Repairing a significant defect early protects the right heart and lungs, which is why the finding should never simply be ignored.
Keeping Your Atria Healthy: When to Talk to a Cardiac Team
Everyday steps that genuinely help. The atria respond to the same habits that protect the rest of the cardiovascular system: controlling blood pressure, maintaining a healthy weight, treating sleep apnoea, limiting alcohol, staying physically active, and managing diabetes and cholesterol. Atrial fibrillation and other atrial problems are strongly influenced by these factors — more so than many people realise — which means lifestyle is not an afterthought but part of the treatment plan itself.
Warning signs that deserve prompt attention.
- A new sensation of racing, fluttering, or irregular heartbeat that does not settle within minutes
- Breathlessness or fatigue that is new, worsening, or limiting everyday activities
- Any sudden weakness, facial droop, speech difficulty, or vision change — call emergency services immediately, as these may signal a stroke
- Fainting, chest pain, or faintness with standing
The value of expert evaluation. Atrial conditions sit at the intersection of rhythm medicine, structural heart disease, and surgery, and the right answer for one patient can be wrong for another. At Cirugía de Corazón, Dr Alejandro Molina and his team in Guadalajara, Querétaro and Hermosillo evaluate each patient's chambers, valves, rhythm and overall health before recommending anything — from watchful waiting to catheter procedures or surgery. If a report mentions atrial enlargement, an arrhythmia, or a septal defect, the most useful next step is a focused consultation rather than Internet self-diagnosis. Book an appointment with a qualified cardiac team, bring your questions and your imaging, and let an experienced specialist explain what your atria are telling you — and what, if anything, needs to be done about it.






