CABG Versus PCI: Comparing Bypass and Stents
A cabg versus pci comparison guides your heart procedure choice.
If your cardiologist has told you that you have blocked coronary arteries, you have probably heard two very different options on the table: open heart bypass surgery, or a stent placed through a catheter. A cabg versus pci comparison is one of the most important decisions you and your cardiac team will make together, because each route carries its own benefits, risks, and recovery timeline. This guide walks through how each procedure works, which patients tend to benefit from each one, what recovery actually looks like, and how to weigh the decision with confidence.
What Is a CABG Versus PCI Comparison?
Two procedures, one goal. Both CABG and PCI exist to restore blood flow to heart muscle that is starved by narrowed or blocked coronary arteries. CABG stands for Coronary Artery Bypass Grafting, an operation in which a surgeon takes a healthy blood vessel from your leg, arm, or chest and uses it to route blood around the blockage. PCI stands for Percutaneous Coronary Intervention, better known as angioplasty with a stent, where a thin catheter is threaded from the wrist or groin into the artery and a small mesh tube opens the narrowing from the inside.
Why the comparison matters. The two approaches treat the same disease in different ways, and the right choice depends on how many arteries are blocked, where the blockages sit, how the heart is functioning, and your overall health. A heart bypass versus angioplasty decision is rarely about one option being universally better; it is about which option fits your specific anatomy and circumstances.
Angiogram versus PCI — a common confusion. Many patients ask whether the coronary angiogram (the dye test that shows blockages) is the same thing as PCI. It is not. The angiogram is the diagnostic picture-taking; PCI is the treatment that may follow in the same sitting if the anatomy is suitable and the plan is to place a stent. There are also two broad types of angioplasty: balloon angioplasty alone, and balloon angioplasty with a stent left in place. Nearly all modern PCI uses a stent.
How Do Bypass Surgery and Coronary Stents Work?
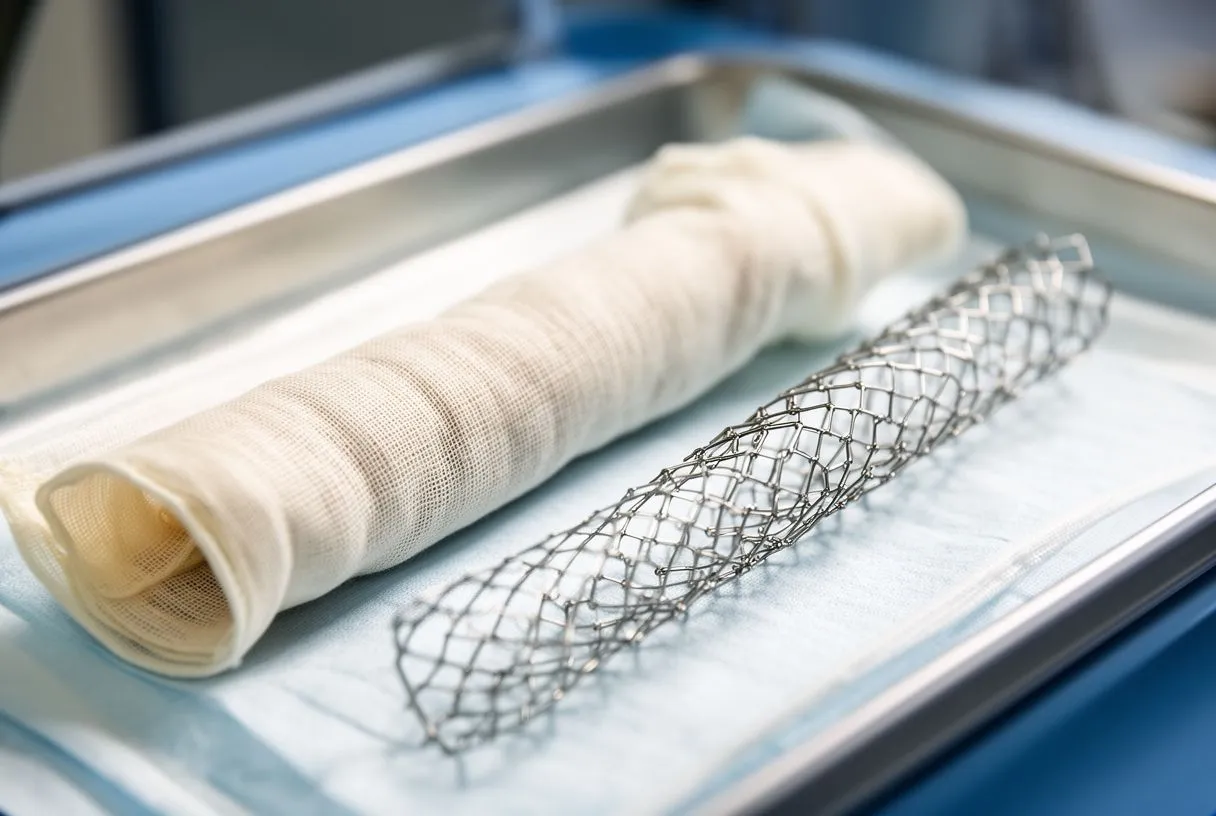
Inside the stent procedure. During PCI, the cardiologist inflates a tiny balloon at the site of the narrowing to press the plaque against the artery wall, then deploys a coronary stent to hold the vessel open. Stents come in two main types: a bare-metal stent, which is a simple mesh scaffold, and a drug-eluting stent, which releases medication over weeks to months to prevent scar tissue from re-narrowing the artery. Drug-eluting stents are now the standard in most cases because they markedly reduce the chance of repeat blockage.
Inside the bypass operation. CABG uses your own vessels — typically the internal mammary artery from the chest wall and the saphenous vein from the leg — to create new routes around blockages. During an on-pump bypass, the surgeon uses a heart-lung machine (cardiopulmonary bypass) to circulate blood while the heart is still. In an off-pump bypass, the surgeon performs the grafting on the beating heart without the machine. Both are established techniques; the choice depends on the patient and the surgeon's judgement. The cardiopulmonary bypass duration, called the bypass time, is one of the factors the team monitors closely during the operation.
Completely different philosophies. A stent treats the specific narrowing that is shown on the angiogram. Bypass surgery re-plumbs the circulation, placing grafts that can outlive the disease process and cover territory beyond just the worst-looking lesion. That structural difference is what drives many of the long-term outcomes discussed below.
What Are the Coronary Artery Disease Treatment Options?
Medication always comes first. Before any procedure, coronary artery disease is treated with medications that lower cholesterol, prevent clots, control blood pressure, and ease the heart's workload. For many patients with stable disease, good medication plus lifestyle change is enough, and studies have shown that in stable patients PCI does not reduce the risk of heart attack or death compared with medication alone. Procedures enter the picture when symptoms persist despite medication, or when the anatomy is dangerous enough that opening the artery urgently is warranted.
Guideline-driven decisions. Modern pci versus cabg guidelines from the major cardiology and cardiac surgery societies weigh anatomy, symptoms, heart function, and patient preference. The decision should be made by a multidisciplinary team — interventional cardiologists and cardiac surgeons reviewing the same images — not by whoever performed the angiogram.
When the team reviews your case. In our practice every case is reviewed by the multidisciplinary team against international practice guidelines before any recommendation is made, and the patient receives a clear proposal with the alternatives so the final decision always rests with them.
CABG or PCI for Diabetes: Which Is Better?
Why diabetes changes the equation. Diabetes makes coronary disease more diffuse — blockages spread along longer segments of the artery rather than sitting in one discrete spot. A stent opens one segment; a bypass graft jumps over the whole diseased stretch. For this reason, major trials comparing the two procedures have generally favored bypass surgery for diabetic patients with multivessel disease, particularly when an internal mammary artery graft is used.
What this means in practice. If you have diabetes and blockages in more than one artery, your team will usually lean toward CABG, provided your surgical risk is acceptable. If you have diabetes but only one or two discrete, suitable blockages, PCI with a drug-eluting stent can still be a reasonable and lower-risk choice. The answer is genuinely individual.
Questions to ask your team. Bring these to your consultation so you can participate in the decision with full information:
- How many arteries are involved? One, two, or three — and where are they located?
- Is my disease diffuse or focal? Diffuse disease favors bypass; a single discrete blockage may favor a stent.
- How is my heart pumping? A reduced ejection fraction shifts the balance toward surgery in many cases.
Left Main Coronary Artery Disease: CABG vs PCI?
Why the left main artery is special. The left main coronary artery supplies most of the blood to the left ventricle, the chamber that does the heart's heavy pumping work. A significant narrowing here is therefore treated with more caution than disease elsewhere. For decades, CABG was the default. Modern trials show that PCI with drug-eluting stents can be an acceptable alternative in carefully selected patients — typically those with simpler left main anatomy and lower complexity — while surgery remains preferred when the blockage involves complicated branches or when surgical risk is low.
What the team looks at. The location of the narrowing within the left main, the health of the other arteries, your age, your kidney function, and your heart's pumping strength all feed the recommendation. This is exactly the kind of decision that should be made by a heart team rather than a single specialist, because the two options trade off differently depending on these variables.
Balance, not dogma. There is no single right answer for every left main case. What matters is that the angiogram images are reviewed with fresh eyes by both a surgeon and an interventional cardiologist, and that the reasoning behind the recommendation is explained to you in plain language before you decide.
Multivessel Disease: CABG or Stent?
The scale tips with more arteries. When two or three coronary arteries are significantly blocked, cabg versus pci evidence increasingly favors surgery, especially in patients who are good surgical candidates. Complete revascularization — restoring flow to all important territories — is easier to achieve with multiple grafts than with multiple stents, and grafts to the left internal mammary artery have demonstrated durable, often decades-long patency.
The SYNTAX-style thinking. Contemporary cardiology scores the complexity of the anatomy: how many lesions, how calcified, how accessible, where they sit. High anatomical complexity pushes toward CABG; lower complexity with suitable lesions can support PCI. Your team should be able to explain where you sit on that spectrum.
Hybrid options exist. In selected patients, a cabg pci hybrid procedure combines a minimally invasive bypass graft to the left internal mammary artery with stents to other vessels, sharing the work between surgeon and cardiologist. It is not for everyone, but it is worth asking about when a full sternotomy seems like a heavy price for treatable disease.
Coronary Bypass vs Stent Recovery: What to Expect?
PCI recovery is fast. Most patients who receive a stent through the wrist go home the same day or the next morning. You will need to keep the wrist or groin site still for a few hours, take dual antiplatelet medication (usually aspirin plus a second clot-preventing drug) for months to a year, and avoid heavy lifting for about a week. Many people are back to desk work within days.
Bypass recovery is a bigger project. Conventional CABG involves opening the breastbone, so expect several days in hospital — including usually a night in intensive care — and roughly six to eight weeks for the breastbone to knit. Driving, lifting, and returning to work follow the sternum's healing, not the heart's. You will also be given discharge rules about diet: nothing "forbidden forever," but the post-bypass period calls for low-salt, low-saturated-fat eating, controlled portions, and often cardiac rehabilitation to rebuild strength safely.
Minimally invasive and off-pump options. Minimally invasive bypass performed through small incisions between the ribs, or an off-pump bypass without the heart-lung machine, can shorten some parts of recovery in selected patients. The right approach depends on anatomy and surgical risk, and in our practice we recommend the less invasive route only where the evidence supports it for that specific patient.
In our consultations we take the time to explain what the studies actually show about each recovery path, in plain words, and we answer every question before any decision is made.
Stent vs Bypass Life Expectancy: What Are the Long-Term Outcomes?
What the long-term data show. For patients with the most serious disease patterns — left main involvement, three-vessel disease, diabetes, reduced heart function — long-term follow-up studies have generally shown better survival and fewer repeat procedures after bypass surgery than after PCI. For simpler, one- or two-vessel disease, the survival difference between well-performed PCI and CABG is small, and the decision often comes down to anatomy, risk profile, and patient preference.
Can you live 30 years after bypass surgery? Many patients do. A well-placed internal mammary artery graft is famous for still working twenty years and beyond after surgery, and patients who stop smoking, control diabetes and blood pressure, and stay active can live for decades after CABG. Surgery fixes the plumbing; long life depends on slowing the disease process that caused the blockages in the first place.
Repeat procedures. Repeat revascularization after PCI is more common than after CABG, because stents treat only the lesions that were stented and restenosis (re-narrowing inside the stent, called in-stent restenosis) or new blockages elsewhere can occur. This is one of the most important differences to weigh when both options are on the table, and it is a central point in any stent vs bypass life expectancy discussion.
Heart Stent Problems vs Bypass: What Are the Risks?
Stent-specific risks. The two main stent complications are stent thrombosis — a clot forming inside the stent, which can cause a heart attack and is why antiplatelet medication must not be stopped without cardiology approval — and in-stent restenosis, where scar tissue re-narrows the treated segment. Drug-eluting stents lowered restenosis rates substantially compared with bare-metal stents, but neither risk is zero. A newer concern cardiologists watch is late stent failure with peri-stent contrast staining, where patterns of dye around the stent on follow-up angiography can signal different risk profiles; research published in the Journal of the American Heart Association has compared the long-term outcomes of focal versus segmental staining patterns.
Bypass-specific risks. CABG carries the general risks of major surgery — bleeding, infection of the sternal wound, stroke, and the effects of the heart-lung machine — and these risks rise with age, kidney disease, lung disease, and frailty. The trade-off is that once you are through the operation, the grafts themselves need no medication to stay open, and the surgical result is often more complete and more durable.
How we look at risk. When our team reviews a case, we weigh each patient's surgical risk factors against the expected durability of the result, and we say plainly where a stent is the lower-risk choice and where surgery protects the heart better over the years. Reliable plain-language summaries of both procedures' risks are also available from sources such as WebMD.
Who Needs Coronary Artery Bypass Surgery, and When Should You Seek a Second Opinion?
Typical candidates for surgery. Knowing who needs coronary artery bypass surgery helps you sanity-check a recommendation. Surgery is usually favored for significant left main disease, three-vessel disease, multivessel disease in diabetics, diffusely diseased arteries not suitable for stenting, and patients whose heart function is already reduced. PCI is usually favored for one- or two-vessel disease with suitable anatomy, for patients at high surgical risk, and for urgent situations where speed matters most.
Younger patients deserve the durability conversation. For a younger patient, stent or bypass is not a casual choice: a stent placed at 45 may need revision at 55, while a mammary graft placed at 45 may still be working at 70. Age is not a reason to have surgery by itself, but expected decades of life make the durability of each option more meaningful.
Second opinions are normal. Getting a cardiac surgeon second opinion in Mexico, or anywhere, is a sensible and widely recommended step before a major heart procedure. We encourage second opinions and treat seeking one as a normal part of deciding about heart surgery. If you are trying to identify the best hospital for CABG in Guadalajara or anywhere else, look less at slogans and more at whether decisions are made by a multidisciplinary heart team with transparent reasoning. Our multidisciplinary team, led by Dr Alejandro Molina, sees patients in Guadalajara, Querétaro and Hermosillo, and the first contact is a free video consultation in which we review your situation, discuss the condition, and identify exactly which studies are still needed so no unnecessary ones are ordered. When we review a case, we compare a CABG versus PCI recommendation against international practice guidelines and present you with both options and their trade-offs before you decide anything.
The bottom line. In a cabg versus pci comparison, neither option wins outright. PCI offers speed, comfort, and a quick return to normal life, with a somewhat higher chance of needing another procedure over the years. CABG offers a more complete and often more durable repair, at the cost of major surgery and a longer recovery. The right answer is written in your angiogram, your health profile, and your priorities — and it deserves a conversation with a qualified cardiac team, not a self-diagnosis. If you are facing this decision, bring your questions to a consultation and make the choice with every alternative laid out in front of you.