Diabetic Revascularisation: Bypass or Stents for Diabetics
Diabetic revascularisation bypass or stents—which option gives diabetics the better outcome?
If you have diabetes and your cardiologist has found blocked coronary arteries, you will eventually face a hard question: should the blockages be treated with a coronary artery bypass grafting operation or with stents placed through a catheter? This decision — often called diabetic revascularisation, meaning restoring blood flow to the heart muscle in a person with diabetes — matters more for you than for most patients, because the two options do not perform equally in people with high blood sugar. This guide walks you through how diabetes affects your arteries, what each procedure actually involves, where the evidence points, and how to think through the choice with your own cardiac team.
What Is Diabetic Revascularisation?
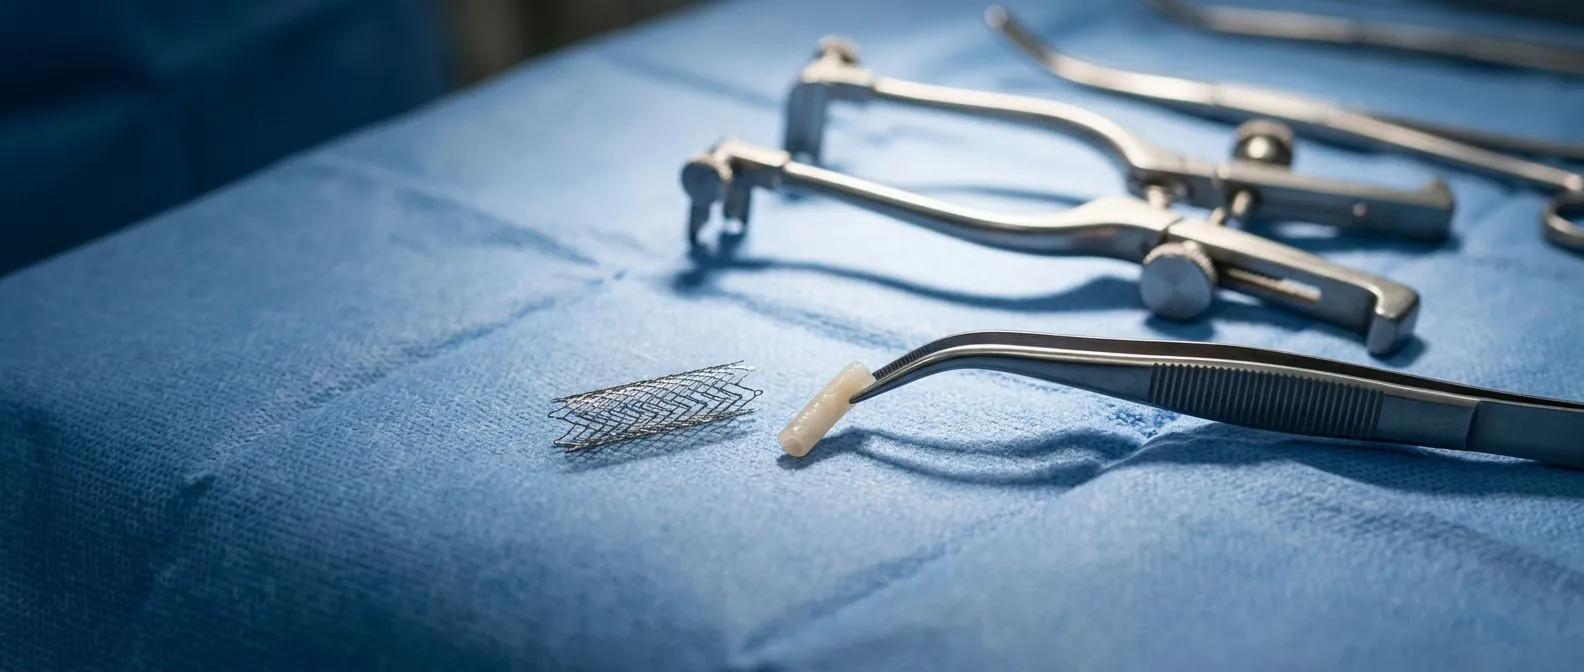
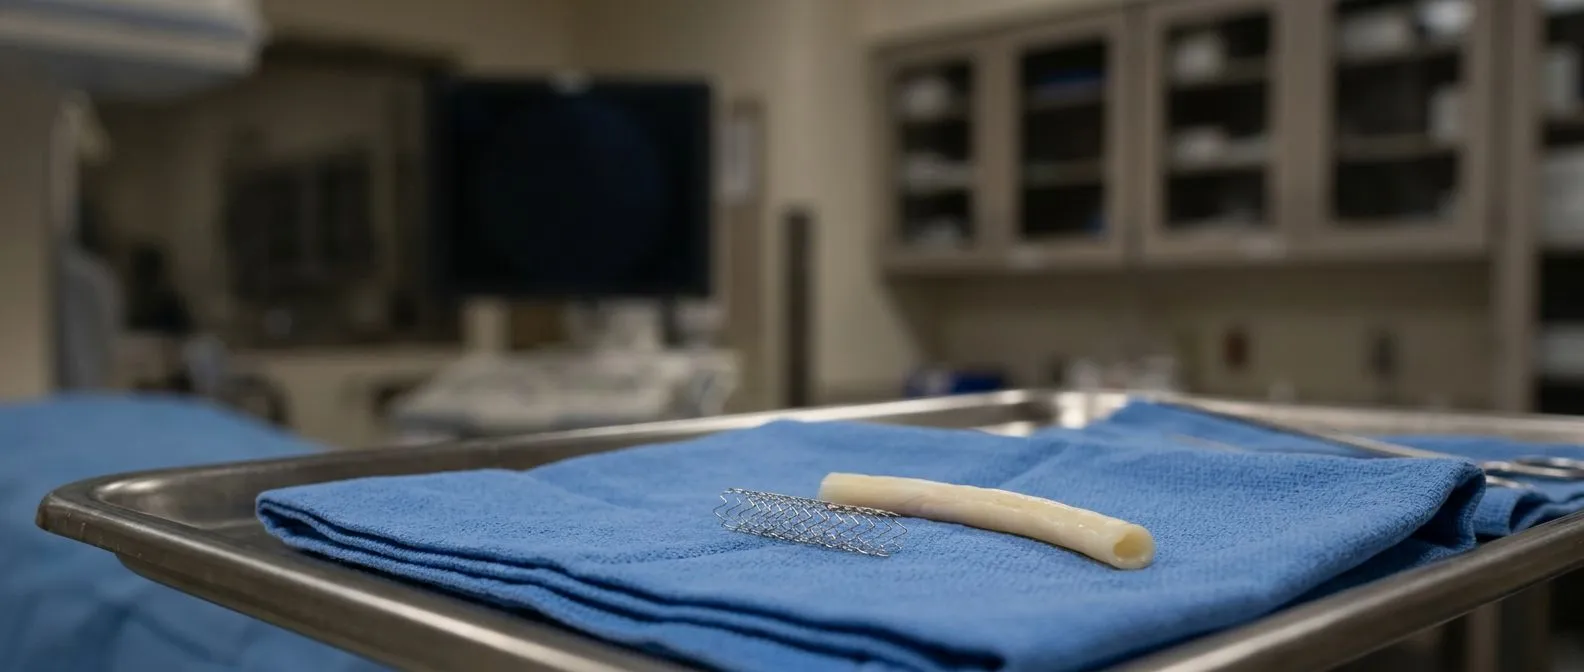
Revascularisation simply means reopening or rerouting blood supply. When a coronary artery — one of the vessels that feeds the heart muscle itself — becomes narrowed or blocked, the muscle downstream is starved of oxygen-rich blood. Revascularisation restores that flow in one of two ways: a surgeon builds a new route around the blockage using blood vessels taken from your chest, arm or leg (bypass surgery), or a cardiologist threads a thin tube into the artery, opens the blockage with a small balloon, and leaves behind a coronary stent, a tiny metal scaffold that holds the vessel open.
Diabetes changes the calculus. High blood sugar over years damages the lining of arteries throughout the body, and in the heart it tends to produce more widespread disease — several vessels affected, and blockages that are longer and harder to treat with a stent alone. It also changes how the body heals after any procedure. That is why the phrase "diabetic revascularisation bypass or stents" describes a genuine decision point rather than a routine pathway: in a patient without diabetes, the two options often perform similarly; in a diabetic patient with multivessel disease, large outcome studies have consistently favoured bypass surgery, and this is echoed in major practice guidelines for coronary revascularisation in diabetes mellitus.
Every case of coronary disease in a diabetic patient is reviewed by our multidisciplinary team against international guidelines before a recommendation is made, so that surgical and catheter-based routes are honestly weighed rather than whichever one the first doctor you saw happens to perform.
Why Does Diabetes Change the Heart Arteries?
Chronically high glucose injures the vessel wall. Over time, sugar molecules bind to proteins in the arterial lining, promoting inflammation and accelerating the buildup of plaque — a mixture of cholesterol, calcium and scar tissue inside the artery. In diabetics, this process tends to run faster and spread wider, and the plaque is often more diffuse, meaning it narrows long stretches of vessel rather than a single short, well-defined spot that a stent can neatly cover.
Silent ischaemia is common. Because diabetes can also damage the small nerves, many diabetic patients feel less chest pain than they should when the heart is starved. Breathlessness on exertion, unusual fatigue, jaw or back discomfort, or even nausea may be the only warnings. This is why a diabetic patient's first presentation is sometimes a heart attack without much warning at all — and why screening for coronary disease is taken seriously even when there is no classic pain.
Blood vessels beyond the heart are affected too. Many patients with diabetic heart disease also have peripheral artery disease — narrowing in the arteries of the legs. Patients often ask whether peripheral artery disease can be reversed: the damage to the artery wall is not truly reversible, but the symptoms can be substantially improved with medication, supervised walking exercise, and, when a specific narrowing is causing them, local revascularisation. Leg symptoms deserve attention in their own right, because severe diabetic peripheral artery disease can threaten the limb.
How Does Bypass Surgery Work for Diabetic Patients?
Coronary artery bypass grafting — usually abbreviated CABG — creates detours around the blockages. The surgeon takes healthy blood vessels from elsewhere in your body: typically the internal mammary artery, which runs inside the chest behind the breastbone and has proven remarkably durable, along with veins from the leg or the radial artery from the forearm. These are attached above and below the blocked segments, so blood flows around the obstruction, giving complete myocardial revascularisation — all parts of the heart muscle get a fresh supply.
There are two main technical approaches. In on-pump bypass, the heart is temporarily stopped and a machine called a cardiopulmonary bypass takes over circulation while the surgeon works; the bypass time on the machine is kept as short as safely possible. In off-pump bypass, the surgeon operates on the beating heart without the machine at all. In patients with diabetes, some evidence suggests that avoiding the heart-lung machine may reduce certain complications, though the choice depends on the anatomy and the whole patient, not on the technique alone. A related strategy, total arterial revascularisation — using only arterial grafts rather than leg veins — is increasingly favoured in diabetic patients because arterial grafts last longer, and long-lasting grafts matter more when the patient is expected to live many decades with progressive disease.
Recovery is real, but predictable. Most patients spend one to two days in intensive care and roughly a week in hospital, then four to six weeks rebuilding strength at home before returning to most normal activities. Diabetes does slow wound healing, so the chest and leg incisions are checked carefully during follow-up, and blood sugar is managed tightly in the hospital to protect healing. In our practice, the surgical plan for a diabetic patient is always discussed with the full team first, and the patient receives a clear proposal with the alternatives — including what stenting would and would not achieve for their specific anatomy — before anything is scheduled.

What Is Stent Placement in Diabetic Patients?
Stent placement — also called percutaneous coronary intervention or PCI — is done through a small puncture, usually in the wrist. A long thin tube is guided up to the heart, a balloon is inflated at the blockage to flatten and widen it, and a coronary stent is expanded to hold the artery open. Modern stents are almost always drug-eluting stents — metal scaffolds coated with medication that slowly releases into the vessel wall to prevent scar tissue from re-narrowing the channel. Older designs were bare-metal stents, which caused much more re-narrowing and are now used only in special situations.
Stenting works best for limited disease. A single short blockage, or one or two discrete lesions in a small area of the heart, can often be treated very well through the wrist with an overnight stay or a one-day admission. The appeal is obvious: no chest incision, no heart-lung machine, a much faster return to daily life. For a diabetic patient with one important narrowed artery and a healthy rest of the heart, a modern drug-eluting stent is a genuinely good option.
The challenge is diffuse, multivessel disease. When diabetes has narrowed several arteries, or long continuous stretches of one, a stent treats the visible narrowings but leaves the underlying vessel disease in place. The stented segment itself can also run into two well-known problems: in-stent restenosis, where scar tissue grows back inside the scaffold and re-narrows it, and stent thrombosis, where a clot forms on the stent surface and can cause a sudden heart attack. Both risks are managed with blood-thinning medication, but in diabetic patients with extensive disease the stent strategy simply has more work to do and more opportunities to fall short.
In the first consultation we take the time to show the patient their own angiogram images and explain in plain words exactly what the studies show — where the narrowings are, how many arteries are involved, and what each option would actually accomplish for that pattern of disease.
Bypass vs Stents for Diabetics: Which Is Better?
For multivessel disease in diabetes, the evidence points towards bypass. Multiple randomised trials have compared CABG versus PCI in diabetic patients and, taken together, they show that bypass surgery reduces the long-term likelihood of death, heart attack and repeat revascularisation compared with stenting — particularly when at least two major arteries are diseased. The advantage is strongest when the left internal mammary artery is used to graft the most important vessel on the front of the heart. This is why current guidelines recommend bypass as the preferred strategy for diabetic patients with significant multivessel disease.
For limited disease, the question is genuinely open. With a single blocked artery and no other vessels involved, both options give good results, and the decision comes down to anatomy, other medical conditions, surgical risk and the patient's own priorities — recovery speed versus long-term durability.
The honest picture, then, looks like this:
- Single-vessel disease: a stent or bypass can both be appropriate; the choice is individualised, weighing recovery speed against long-term durability.
- Two or more diseased arteries: bypass surgery with an arterial graft is usually favoured, because it offers a more complete and more durable solution for diabetic coronary artery disease treatment.
- Complex anatomy with high surgical risk: sometimes a hybrid or staged approach is considered, with the trade-offs explained openly rather than a single "correct" answer imposed.
What Are the Two Types of Revascularisation?
Patients often ask exactly this: what are the two types of revascularization? The answer is surgical and percutaneous. Surgical revascularisation means bypass surgery — a formal operation, general anaesthesia, a chest incision, grafts sewn in place, and a hospital stay measured in days. Percutaneous revascularisation means catheter-based treatment — stents, balloons, entry through the wrist or groin, and usually one night in hospital. Neither is universally "better"; they are different tools for different patterns of disease.
The same two categories apply to the legs. When diabetes narrows the arteries of the legs — sometimes described, somewhat loosely, as coronary artery disease in the legs, though strictly it is peripheral artery disease — treatment again splits into surgical bypass of the blocked leg arteries versus catheter-based angioplasty and stenting. People also ask how to open blocked veins in legs: when the blockage is in a vein rather than an artery, the same catheter techniques are often used, but the diagnosis must be made first, because vein blockages (for example deep vein thrombosis) are treated very differently from arterial narrowing. Elderly patients considering leg angioplasty should know the specific risks: puncture-site bleeding, damage to the artery at the entry point, kidney strain from the contrast dye, and re-narrowing of the treated segment, which happens more often in diabetic vessels than in others.
Arterial insufficiency is the umbrella term. When people ask what arterial insufficiency is, it simply means that an artery cannot deliver enough blood to the tissue it supplies — in the heart it causes chest pain and heart attacks, in the legs it causes cramping on walking, wounds that will not heal, and in advanced cases pain at rest. The treatment logic is the same in both locations: restore flow, and support the tissue with medication and risk-factor control.
What Are the Risks of Revascularisation in Diabetes?
Every procedure carries risks, and diabetes modifies them. For bypass surgery, the main risks are bleeding, infection of the chest or leg wound, irregular heart rhythm in the first days, kidney stress, and stroke. Diabetes raises the probability of wound infection and delayed healing, which is why blood sugar control around the time of surgery is treated as part of the operation itself, not an afterthought. The kidney is another diabetic vulnerability, and the contrast dye used in catheter procedures can strain it, so hydration and kidney-protection protocols are standard.
For stents, the risks run in a different direction. The immediate procedure is gentler, but the stented segment can re-narrow, and a clot can form on the stent. To prevent clotting, patients must take dual antiplatelet therapy — usually two blood thinners together — for months to a year or more. Interrupting this medication early, for dental work or surgery, is one of the most common causes of stent thrombosis, so any patient with a stent must tell every treating doctor before stopping it. There is also a longer-term consideration: a review published in a Brazilian cardiovascular journal has described a case in which a stent complication after an acute myocardial infarction progressed to severe ischemic cardiomyopathy, a sobering reminder that stent problems, though uncommon, can be serious (Revista Brasileira de Cirurgia Cardiovascular).
Diabetes and the arteries of the legs deserve a word of honesty. People also ask whether elevating your legs is bad for people with peripheral artery disease. The answer is that raised legs relieve swelling and venous discomfort, but in arterial insufficiency they can actually worsen the blood supply to the feet — gravity no longer helps fill the diseased arteries. If you have both problems, ask your doctor which position suits your specific circulation. In our practice, the risks of each proposed route are laid out explicitly, and the final decision is always the patient's — we present the options, and the patient chooses.
What Is Recovery Like After Diabetic Heart Revascularisation?
Recovery after a stent is measured in days; after bypass, in weeks. After stent placement through the wrist, most patients go home the next day and resume desk work within roughly a week, though the anti-clotting medication schedule must be followed exactly. After bypass surgery, the first week is dominated by wound care and gentle walking, sternum precautions — no lifting, pushing or driving for about six to eight weeks while the breastbone heals — and a gradually expanding programme of activity. A cardiac rehabilitation programme, with supervised exercise, makes a measurable difference in both groups.
For diabetic patients, healing and blood sugar are the main themes. Incisions need daily inspection because diabetes can mask early infection signs, and the nerves of diabetes can make wound discomfort less reliable as a warning. Tight glucose control during the first weeks does more than protect the incision — it also protects the grafts and the stented vessel, since high sugar accelerates the very disease the procedure was meant to fix. Rehabilitation also addresses the exercise question: people with peripheral artery disease are usually recommended supervised walking programmes — walking to the point of mild leg discomfort, resting, then repeating — because this trains the muscles to use the available blood supply more efficiently. For a diabetic patient after heart revascularisation, the same principle of graded, regular exercise applies to the heart.
After surgery, the incisions, the blood sugar log and the diabetes plan all need regular review with the patient's diabetes doctor, because heart surgery in a diabetic patient is never just a heart problem.
How Do You Choose the Right Procedure for You?
The anatomy decides far more than any preference. The most useful single piece of information is how many arteries are blocked, how long each blockage is, and where they sit. A single short lesion in one vessel is a stent conversation; multiple diseased arteries in a diabetic patient is a bypass conversation. A specialist in myocardial revascularisation — the formal name for restoring blood flow to the heart muscle — should be able to show you your own images and explain, in plain language, which option fits which finding.
Ask the questions that matter. A short checklist helps patients make sense of their consultation:
- How many arteries are involved, and how badly? The count and the pattern drive the recommendation more than any other factor.
- What does bypass give me that stents do not — and vice versa? Ask for both the benefit and the cost of each route in your own case.
- What is my surgical risk? Tools such as EuroSCORE II estimate operative risk from age, kidney function, lung function and other factors; the number should be discussed openly.
- What happens if I do nothing? Sometimes medication alone is appropriate for stable disease — the guidelines allow it in the right circumstances, and the option deserves to be mentioned.
Weighing glycaemic control matters too. Research on revascularisation outcomes stratified by glycemic control shows that long-term sugar control influences how well any revascularisation holds up, which is a fair reason to ask your diabetes team to optimise your treatment before a major decision. We also actively encourage second opinions and treat seeking one as a normal part of deciding about heart surgery — a confident team welcomes a second pair of eyes.
Can You Live Well After Revascularisation With Diabetes?
Revascularisation is the beginning of the long game, not the end. Whether you received grafts or a stent, the underlying disease process — diabetes-driven atherosclerosis — continues unless it is actively managed. The medication that protects grafts and stents (blood thinners, statins, blood pressure control, diabetes therapy) is not a temporary prescription; it is the maintenance plan. Smoking cessation, weight management and regular movement do more for the long-term result than any single technical choice made in the operating room.
Follow-up is where durability is won. Periodic check-ups catch re-narrowing, graft disease and new blockages while they are still manageable. Diabetic patients should expect coordinated care between the heart team and the diabetes team, because the two conditions are one disease in two territories. The key point about the stent-versus-bypass decision, drawn from the pooled trial evidence summarised in the cardiology literature (Springer), is that it should be made by a team that can genuinely deliver either option — not by whichever procedure happens to be available or preferred by a single specialist.
In our multidisciplinary team, led by Dr Alejandro Molina, with consulting rooms in Guadalajara, Querétaro and Hermosillo, we cover valve disease, coronary disease, the aorta and structural heart conditions, and we recommend the less invasive route only where the evidence supports it for that specific patient. If you are facing this decision, the next step is not self-diagnosis: it is a proper review of your images by a qualified cardiac team. Our first contact is a free video consultation — we get to know you, talk through your condition, and tell you which studies are still needed so no unnecessary ones are ordered — and a face-to-face visit follows when you decide to go ahead.