

Dialysis Patients and Heart Surgery: Special Planning
Dialysis patients heart surgery requires special coordination between kidney and cardiac teams.
When someone on dialysis needs heart surgery, the two conditions change each other's management in ways that surprise most families. This guide explains what dialysis patients heart surgery planning actually involves — how kidney care and cardiac care teams coordinate, what the operation and recovery look like, and which decisions deserve a second opinion. If you or a loved one are living with kidney failure and have just been told you need a heart procedure, here is what happens next, step by step.
What Is Dialysis and Why the Heart Needs Special Care
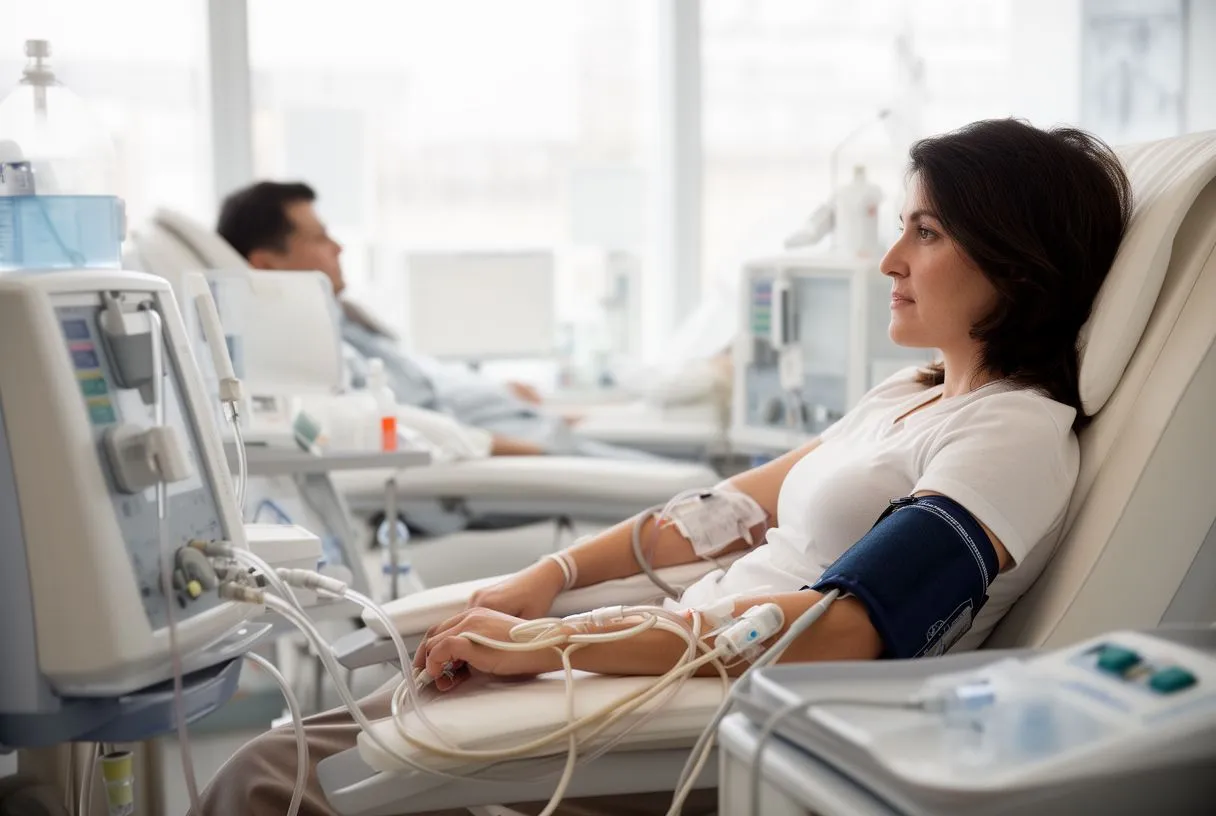
Dialysis is a treatment that takes over the kidneys' job of filtering waste and extra fluid from the blood when the kidneys can no longer do it. There are two main forms: hemodialysis, which circulates the blood through a machine usually three times a week, and peritoneal dialysis, which uses the lining of the abdomen as a natural filter. Both keep a person alive and functioning, but neither replaces the kidneys perfectly.
Why the heart and kidneys are linked: Kidney failure and heart disease travel together. Damaged kidneys raise blood pressure, cause fluid to build up in the lungs, and disturb the balance of minerals like potassium and calcium that the heart muscle depends on to beat steadily. Over time, blood vessels in the heart stiffen and narrow. This is why cardiac surgery chronic kidney disease is such a common combination — the same process that destroys the kidneys damages the heart.
The practical consequence: A person who has been on dialysis for years is more likely to develop coronary artery disease (narrowed heart arteries) or valve disease than someone with healthy kidneys. The disease also arrives earlier and can progress faster. That is not a reason for alarm; it is a reason for careful planning. The good news is that heart surgery for dialysis patients is done routinely, and outcomes have improved steadily as teams have learned to manage the two conditions together.
How Hard Is Dialysis on the Body?
People often ask how hard dialysis is on the body, and the honest answer is: it is a significant physical load, but one the body adapts to. During a hemodialysis session, several liters of blood are filtered through a machine over about four hours. The rapid shifts in fluid and blood pressure ask a lot of the circulation, especially of the heart.
The strain on the heart: Each session changes the volume of blood the heart must pump. When fluid is removed too quickly, blood pressure can drop and the heart muscle can be briefly starved of adequate blood flow. Over the years, this repeated stress can contribute to a condition called uremic cardiomyopathy — a weakening and stiffening of the heart muscle caused by the buildup of waste products that dialysis removes only partially. The American Heart Association publishes research on this heart-kidney relationship, and cardiologists now treat it as a two-way street: a failing heart damages the kidneys, and failing kidneys damage the heart.
What patients actually feel: Many people tolerate dialysis well and live full lives on it. Others feel drained after sessions, especially in the first months. Fatigue after dialysis is one of the most common complaints patients report, and it matters here because it shapes what recovery from heart surgery will feel like. A person who is already tired from three sessions a week will experience surgical fatigue differently, and the care plan has to account for that rather than treating it as an afterthought.
Why Do Dialysis Patients Heart Surgery Plans Differ?
The central reason dialysis patients heart surgery planning is special is fluid. During standard open heart surgery, the heart-lung machine circulates the patient's blood, and the body retains a large amount of fluid used to prime that machine. A person with healthy kidneys simply urinates the extra fluid out over the following days. A person on dialysis cannot — so the team must plan for dialysis to remove it, on a schedule and in amounts that protect the healing heart.
Three systems that need coordinating: First, the fluid balance: too much fluid strains the heart and lungs, too little damages the kidneys that remain (in partial kidney failure) and drops blood pressure. Second, the medications: blood thinners, antibiotics, and anesthesia drugs must be dosed for reduced kidney clearance, which is what heart surgery dialysis clearance reviews are about. Third, the access: a dialysis fistula in the arm is a lifeline, and it must be protected during positioning, lines, and blood pressure cuffs.
Timing is the fourth variable: Dialysis before heart surgery is often scheduled within 24 hours of the operation to start the procedure in the best possible fluid and chemical balance. Potassium, in particular, must be in a safe range before anesthesia — a level that is too high can trigger dangerous heart rhythms. This is why the kidney team and the surgical team talk to each other before the date is set, not after.

A word about the multidisciplinary approach: This is why the team reviews every case against international guidelines before a recommendation is made. In our consultations with patients on dialysis, we find that the fluid management plan is the part families most want explained, and rightly so: it is the single biggest difference between cardiac surgery in a dialysis patient and the same surgery in someone with healthy kidneys.
Types of Heart Surgery for Dialysis Patients
Not every heart problem in a dialysis patient requires open heart surgery. The goal is always to treat the heart condition with the least invasive approach that is safe and effective for that specific patient. These are the main options:
- Coronary artery bypass (CABG): Coronary artery bypass dialysis patients undergo is performed to route blood around blocked arteries. It is the traditional approach for multiple blocked vessels and is done through the chest, with the heart-lung machine.
- Valve surgery and repair: Heart valve surgery dialysis patients need most often involves the aortic or mitral valve. It can be done conventionally, minimally invasively through smaller incisions, or robotically.
- Transcatheter procedures (TAVR): Transcatheter aortic valve replacement, or TAVR, delivers a new aortic valve through a catheter in the groin, without opening the chest. It is often considered for patients at higher surgical risk — a category where many dialysis patients fall.
- Angioplasty and stents: For one or two narrowed arteries, a catheter-based procedure with a stent may treat the problem without any surgical incision at all.
How the choice is made: The decision depends on the anatomy of the disease, the urgency, the patient's overall strength, and the surgical risk score. Kidney dialysis patients cardiac surgery risk is usually higher, which pushes the balance toward less invasive options like TAVR — but not always. A patient with several blocked arteries may do better with bypass surgery than with multiple stents, even at higher risk. We recommend the less invasive route only where the evidence supports it for that patient; in our practice the choice is never made by the technology available, but by what the studies and the patient's own anatomy show.
Dialysis Before Heart Surgery: What to Expect
Knowing what to expect during dialysis — and around surgery — removes much of the fear. In the weeks before a scheduled operation, the kidney team tightens control of fluid, potassium, and phosphorus. The surgeon orders heart imaging: an echocardiogram (an ultrasound of the heart), a catheterization to map the coronary arteries, and sometimes a CT scan. Each test answers a specific question, and the preoperative dialysis heart patients protocol exists so that no unnecessary ones are ordered.
The final 48 hours: Dialysis is usually performed the day before surgery. The nephrologist aims for a "dry weight" — the weight at which the body holds neither excess fluid nor is depleted. Blood tests confirm potassium, hemoglobin, and clotting factors are in the surgical range. Patients are often asked to hold certain medications, and the anesthesia team reviews everything.
Day of surgery: The patient arrives early, meets the anesthesiologist, and is taken to the operating room. Whether the procedure is bypass, valve replacement, or TAVR, the dialysis catheter or fistula is handled with deliberate care — it is as important to the patient's survival as the heart itself. In our own operating planning, we protect the dialysis access as a first-order priority, because losing it means a difficult search for new access during recovery.
What Causes Muscle Cramps and Fatigue During Dialysis?
Two of the most searched questions about dialysis are what causes muscle cramps during dialysis and whether dialysis makes you tired and weak. Both deserve clear answers, because they also affect surgical recovery.
Cramps: Muscle cramps during dialysis usually happen when fluid is removed faster than the body can adjust. As blood volume drops, muscles — often in the legs — respond by cramping. Low sodium in the dialysis fluid and removing too much fluid in one session both contribute. The fix is usually adjusting the dialysis prescription: slower fluid removal, longer sessions, or sodium adjustments. Cramps are uncomfortable, but they are a signal the treatment plan can be tuned, not a sign something is failing.
Fatigue: Tiredness after dialysis comes from several sources: the drop in blood pressure during treatment, the loss of small amounts of blood each session, anemia (low red blood cell count, common in kidney disease), and the underlying illness itself. Before surgery, the team treats anemia aggressively because it directly affects how well the body heals. After surgery, expect the fatigue to be layered — surgical tiredness on top of dialysis tiredness — and to improve gradually over weeks, not days. Patients often tell us they do feel better after dialysis once their prescription is balanced; the difference between a well-tuned and poorly tuned dialysis plan is real, and it matters enormously during a surgical recovery.
Are Dialysis Patients Open Heart Surgery Risks Higher?
The question families ask most directly: are dialysis patients open heart surgery risks higher than for other patients? Yes, they are — and pretending otherwise would be a disservice. Dialysis patients open heart surgery carries higher rates of wound infection, bleeding, irregular heart rhythms, and longer hospital stays compared with patients who have normal kidney function. The statistical tools surgeons use, such as the EuroSCORE II, deliberately account for kidney failure when calculating an individual's risk.
What the higher risk actually means: Higher risk does not mean unacceptable risk. It means the decision must be made deliberately, with the alternative options — medication alone, stents, TAVR — weighed honestly. For some dialysis patients, the risk of surgery is justified because the heart condition would otherwise shorten life or destroy its quality. For others, careful medication management is genuinely the safer path. There is no universal answer; there is only the answer for one patient, one anatomy, one set of goals.
Wound healing deserves its own mention: Kidney failure slows skin and tissue healing, so chest wounds in dialysis patients need extra attention. Meticulous wound care and early follow-up help catch problems before they become serious — the incision is checked at postoperative visits, and families should learn exactly what to watch for at home.
How Doctors Plan Heart Surgery for Kidney Dialysis Patients
Good planning is where the outcomes are won. Modern teams increasingly use 3D-printed models of the patient's own heart to rehearse complex procedures before the operating room; a cross-specialty review published in the International Journal of Environmental Research and Public Health documents how these models improve planning and surgical training for complex cases. For a dialysis patient whose anatomy may be altered by years of vascular disease, seeing the actual problem in three dimensions can change the surgical plan.
The typical planning sequence: The cardiac surgeon and nephrologist agree on the dialysis schedule around the operation, the anesthesia team sets the medication plan, and the intensive care team prepares the postoperative dialysis strategy. Everything is written down before the first incision. Nothing about a dialysis patient's heart operation should be improvised.
Questions to bring to your consultation: A good cardiac team welcomes hard questions, and seeking a second opinion is a normal, respected part of deciding about heart surgery — we actively encourage our patients to get one. Useful questions include:
- Which procedure, and why not the alternatives? Ask the surgeon to explain the reasoning in plain words, including what would happen with treatment alone.
- How will my dialysis schedule be handled? Before surgery, in the hospital, and in the first weeks home.
- Who manages my kidney care during the hospital stay? A named nephrologist should be part of the inpatient plan.
In our first meeting with a patient — which is a free video consultation — we get to know the person, talk through the condition in plain language, and identify which studies are genuinely still needed. A face-to-face visit follows only when the patient decides to go ahead. Dr Molina trained in cardiac, minimally invasive, robotic and structural surgery at the University of Montreal, and in structural cardiology and TAVR at CHU Bordeaux, and the team also trained at Jena, Bad Berka and Buffalo — a background that matters here, because TAVR experience is directly relevant to many dialysis patients.
Heart Surgery and Dialysis Recovery: What Really Happens
The honest picture of heart surgery and dialysis recovery is a gradual one, measured in weeks and months. The hospital stay is typically longer than for patients without kidney failure — often a week or more — because fluid, potassium, and blood pressure need close daily management.
Weeks one to four: Dialysis resumes almost immediately after surgery, often the next day, with sessions adjusted to protect the healing chest and the new or repaired heart structures. Wound care happens at every dialysis visit, which is an unexpected advantage: the dialysis nurse sees the incision three times a week. Walking begins within days. The sternum (breastbone) needs six to eight weeks to knit, so lifting restrictions apply throughout.
Months one to three: Energy returns slowly. Cardiac rehabilitation — supervised, structured exercise — is strongly recommended and works well for dialysis patients when the kidney team is involved in setting the pace. Some patients report that after the immediate surgical fatigue lifts, they feel better than before surgery: less breathless, able to walk farther, sleeping better. That improvement is real and it is why the surgery was worth doing.
How long does a person stay on dialysis? This question — how long does a person be on dialysis — deserves a direct answer here. For most people who start dialysis, it is a long-term or lifelong treatment unless a kidney transplant becomes possible. Heart surgery does not change that trajectory; what it changes is the quality and sometimes the length of life lived on dialysis. If a transplant is being considered, the heart operation may actually be a prerequisite step — many transplant programs require significant heart disease to be treated first.
How to Help Someone with Kidney Failure Facing Heart Surgery
Family members often ask how to help someone with kidney failure who now also needs heart surgery. The support that matters most is practical and specific rather than general encouragement.
Practical support that makes a difference: Help track the dialysis schedule and the medication list — two sets of instructions from two teams can create confusion that one written list resolves. Attend the pre-surgical consultations and take notes; the patient is absorbing difficult information and a second set of ears genuinely helps. Learn the warning signs to watch at home: fever, increasing redness or drainage from the incision, sudden weight gain, shortness of breath, or leg swelling — any of these warrants a call to the team, not a wait-and-see.
Emotional support without pressure: Recovery is slower for dialysis patients, and expectations must match that reality. The most valuable thing a family can do is celebrate small milestones — the first walk to the mailbox, the first dialysis session completed without a blood pressure dip — rather than measuring against a healthy person's recovery timeline.
Signs of advanced kidney disease that deserve attention: Families of people in stage 4 kidney disease (severe kidney function loss, before dialysis) should know the common symptoms: worsening fatigue, poor appetite, nausea, itching, swelling in the legs, and changes in urination. If these appear in someone with known heart disease, both the cardiologist and the nephrologist should be told — the two conditions are managed best in concert, never in isolation.
Finally, if you are reading this because you or someone you love is a dialysis patient facing a heart problem, do not try to make this decision alone or by searching. Talk to a qualified cardiac team that works with kidney patients regularly, ask every question, get a second opinion if you want one, and book a consultation so the plan is built around your specific heart and your specific kidneys. That conversation is the single most valuable step in the entire process.






