

Edge-to-Edge Repair for a Leaking Mitral Valve
Edge-to-edge repair mitral valve is a catheter-based alternative to open heart surgery.
When your doctor tells you that your mitral valve is leaking, the first question is usually whether open heart surgery is the only answer. For many patients, it is not. Edge-to-edge repair mitral valve is a catheter-based technique that clips the leaking valve leaflets together, restoring the valve's ability to close without opening the chest. In this guide we explain what the procedure involves, who it suits, how recovery works, and how it compares with conventional Mitral Valve Repair and Mitral Valve Replacement, so you can approach the decision with clear facts.
What Is Edge-to-Edge Repair Mitral Valve?
Edge-to-edge repair mitral valve refers to a technique that joins the two edges of the mitral valve leaflets, the thin flaps of tissue that open and close with every heartbeat. The idea is simple: if the leaflets leak because they do not meet properly, bringing a central portion of them together reduces the leak and creates a double-orifice valve, much like the double-stitch technique surgeons have used for decades. When done through a catheter, it uses an edge-to-edge clip, and the general term is Transcatheter Edge-to-edge Repair, or TEER.
The technique was first adapted from surgical experience. Surgeons in Italy developed the idea in the early 1990s, and the percutaneous version was built on that experience, as described in Percutaneous Mitral Valve Edge-to-Edge Repair. Today it is one of the most studied procedures in structural heart medicine, and a recent Meta-analysis of two devices for transcatheter mitral edge-to-edge repair confirms that results are consistent across patient groups.
Understanding your own valve matters here. If you want the anatomy in plain language, our article on Knowing your heart: the mitral valve explains how the valve sits between the left atrium and left ventricle, why it has two leaflets, and what happens when they fail to close. The edge-to-edge approach is one of several options, and the best one depends on the exact reason your valve leaks.
How Does a Leaking Mitral Valve Affect Your Heart?
What regurgitation does to the heart. When the mitral valve leaks, blood flows backward into the left atrium with every heartbeat. Doctors call this mitral regurgitation. The heart has to pump more blood than the body actually needs, and over months or years this extra workload stretches and weakens the left ventricle. Symptoms often start quietly: shortness of breath on stairs, fatigue, waking at night feeling breathless, or swelling in the ankles.
Why symptoms can appear late. Many people tolerate a leaking valve for years because the heart compensates. That is also why some patients only learn about the problem during a routine echocardiogram, an ultrasound of the heart. But waiting too long can cost you options. Once the heart muscle is stretched or the lung pressure rises, some treatments become less effective or higher risk. This is one reason we review every case in our team against international practice guidelines before recommending anything, and we tell patients plainly when the findings suggest it is time to act.
What the grades mean. Regurgitation is graded from mild to severe. Mild leaks are usually monitored. Severe regurgitation, especially when it causes symptoms or evidence of heart strain, needs treatment. Your echocardiogram report will mention terms like "flail leaflet" or "prolapse", which describe specific ways the valve fails. Mitral Valve Prolapse, for example, means one leaflet bows backward into the left atrium during the heartbeat, and that is one of the classic situations where the valve leaks.
What Is Edge-to-Edge Repair (TEER)?
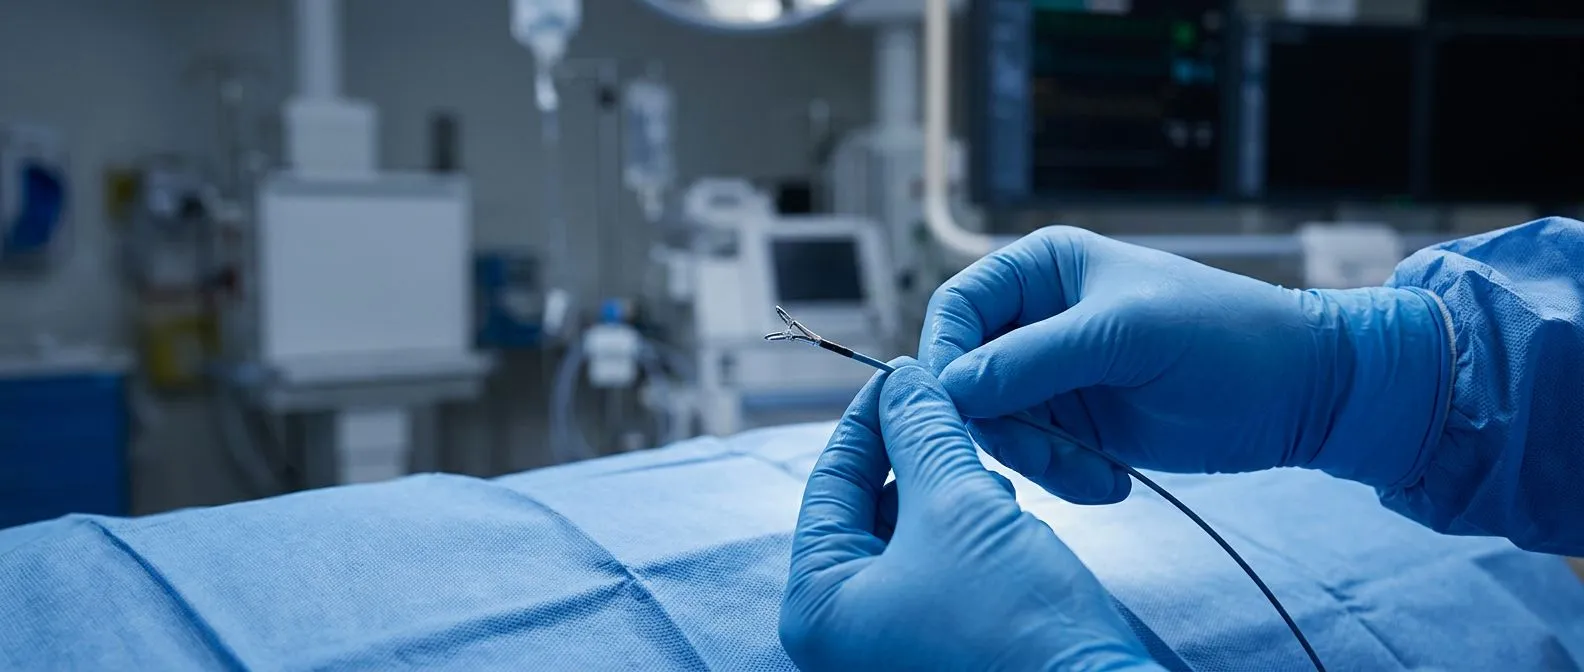
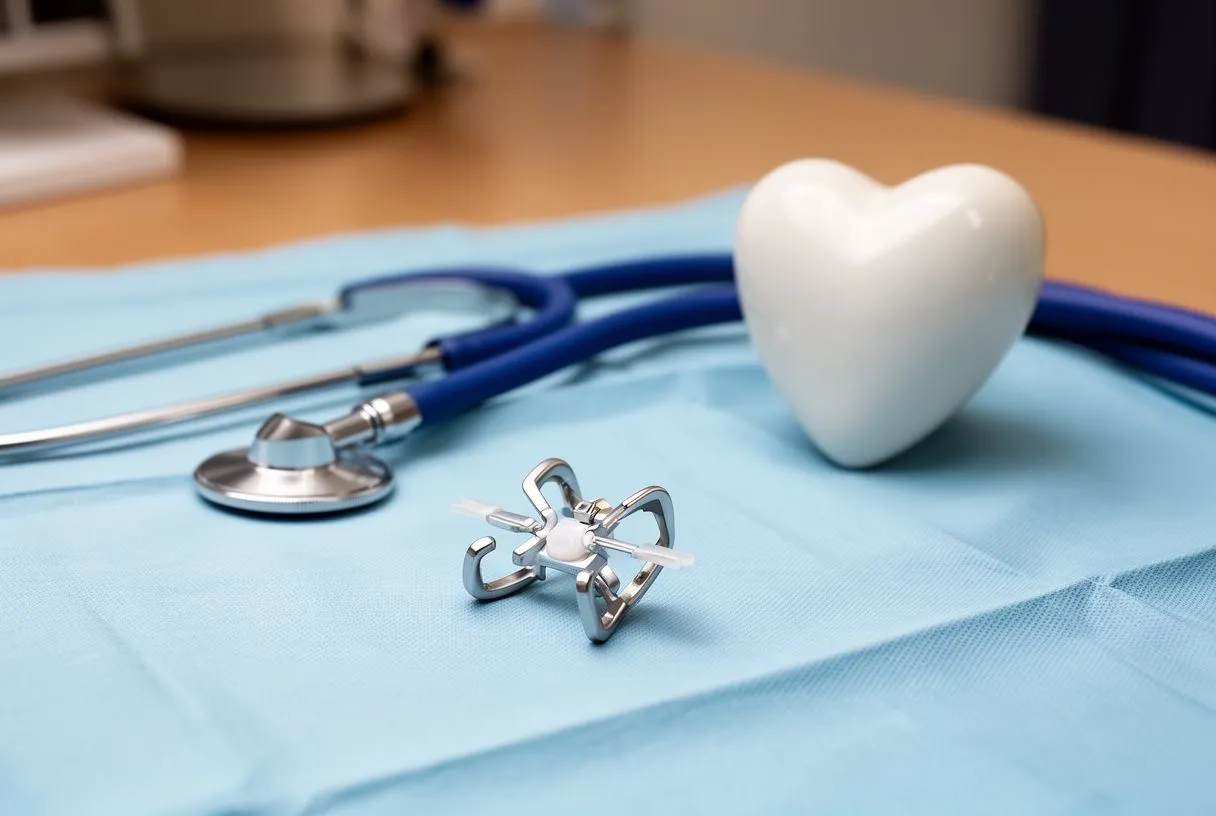
The device in plain words. Edge-to-edge repair (TEER) is a well-established catheter treatment for mitral regurgitation. It is a small polyester-covered clip, roughly the size of a grain of rice, delivered on a thin catheter. The catheter enters through a vein in the groin, travels up to the heart, and passes through the wall between the two upper chambers to reach the left side. The clip is then positioned in the center of the valve and closed, pinning the two leaflets together where they leak.
How one clip changes the leak. By joining the leaflets in the center, the clip creates two smaller openings instead of one large one. Each opening closes better than the original single one, and the backward leak is reduced. Some patients need one clip, some need two. The goal is not a perfect valve in every case; it is a meaningful reduction in the leak that lets the heart rest and symptoms improve.
What it does not do. Edge-to-edge repair does not address every cause of leakage. If the valve leaflets are calcified, if the ring that supports the valve is badly diseased, or if the leak is in the corner rather than the center, a clip may not hold. A careful echocardiogram, sometimes with a transesophageal study, tells the team whether the anatomy suits the clip. Our team reviews each case in person before offering the procedure, precisely because the anatomy decides the answer.
Who Is a Candidate for Transcatheter Edge-to-Edge Mitral Repair?
Patients at high surgical risk. The clearest indication for TEER is a patient with severe degenerative mitral regurgitation who is too high risk for conventional surgery. International guidelines also cover patients with secondary regurgitation, where the leak is caused by the heart muscle failing rather than by the valve itself. The reported success rates in these groups are high, and the meta-analysis we cited earlier shows consistent improvement in symptoms and heart function.
Patients with secondary regurgitation. When the heart muscle is weak, the valve leaflets get pulled apart rather than ballooning backward. The leak is real, but the valve itself is normal. Edge-to-edge repair works in these patients because the clip pulls the leaflets back together, reducing the leak and the heart's workload. These patients usually also need medical therapy for heart failure, and the clip is part of a broader plan rather than the whole answer.
Who is not a candidate. Some patients do better with conventional surgery. If the valve is repairable through surgery and the patient is at low risk, conventional or minimally invasive repair is usually preferred because it treats the whole valve and can last decades. Patients who cannot tolerate even a catheter-based procedure, or whose anatomy is too difficult for the clip, may need other options. We discuss these trade-offs openly, and we recommend the less invasive route only where the evidence supports it for that patient.

Edge-to-Edge Repair vs Mitral Replacement
Repair keeps your own valve. Whenever possible, valve repair is preferred over replacement. The valve leaflets are your own tissue, and they last longer than any artificial valve. Repair also avoids the lifelong need for blood thinners that comes with most mechanical valves and the typical wear that comes with biological valves. Mitral Valve Repair is the standard treatment for severe regurgitation when the valve anatomy is suitable, and modern surgical repair success rates are excellent.
When replacement is needed. Sometimes the valve is too damaged to repair. Severe calcification, rheumatic disease, or a prior failed repair may leave replacement as the only option. Mitral Valve Replacement is a major surgery, but it is a well-established and safe option. There are also newer approaches such as Transcatheter Mitral Valve Replacement, which is done through a catheter and does not require opening the chest, and valve-in-valve procedures, where a new valve is placed inside an old one that has worn out.
Trade-offs in a table.
- Edge-to-edge repair: catheter-based, no chest incision, usually shorter hospital stay, best for patients at high surgical risk or with specific anatomy.
- Conventional surgical repair: treats the whole valve, longest durability, requires open chest or minimally invasive surgery, best for patients at low surgical risk.
- Replacement: needed when repair is not possible, may require lifelong blood thinners with a mechanical valve or eventual replacement of a biological valve.
What our team recommends. We review every case in a multidisciplinary meeting before making a recommendation. The decision is not about the newest technique but about the right one for your anatomy, your surgical risk, and your goals. When a patient is a candidate for both, we explain the trade-offs in plain words and let them decide.
What Happens During the Edge-to-Edge Mitral Valve Procedure?
Before the procedure. You will need a detailed echocardiogram, sometimes a transesophageal echocardiogram, which is done with a probe swallowed like a camera tube to see the valve from inside the esophagus. Blood tests, an electrocardiogram, and a CT scan of the heart are also common. In our first contact, which is a free video consultation, we get to know the patient and explain which of these studies are actually needed, so that nobody orders unnecessary tests.
During the procedure. The procedure is done in a catheterization laboratory, under general anesthesia. A thin catheter enters through a vein in the groin and is guided to the heart. The team uses live ultrasound imaging, not X-rays, to steer the clip and confirm it grips the leaflets correctly. The clip is then closed, and the team checks the leak has reduced. If needed, a second clip is placed. The whole procedure usually takes two to three hours.
After the procedure. Most patients stay one to two nights in hospital. A follow-up echocardiogram is done before discharge to confirm the leak is reduced. Some patients notice symptom improvement within days; for others it takes weeks. You will need regular follow-up echocardiograms over the following years to make sure the repair is holding.
Edge-to-Edge Repair Recovery Time
Back to daily life quickly. One of the main advantages of TEER over open surgery is recovery time. Because there is no chest incision, most patients are walking within a day and back to normal activities within a week or two. Compare that with open surgery, where full recovery typically takes six to twelve weeks. Recovery is gentler, and there is no need to avoid driving for weeks or do weeks of chest precautions.
What to expect in the first days. The groin puncture site is usually the sorest part. Some patients have bruising there. Mild fatigue is common for a week or two. Many patients are surprised how quickly they feel better, especially if symptoms of breathlessness had been limiting them.
Follow-up care. You will need to see your cardiologist within a few weeks, and then at regular intervals. Echocardiograms at three, six, and twelve months, and annually after that, are standard. If you are on heart failure medications, your team will adjust them after the procedure as the heart improves. We encourage second opinions and treat seeking one as a normal part of deciding about heart surgery, so if you want another view before committing, that is welcome.
Are There Risks to Catheter-Based Mitral Valve Repair?
Known risks and how often they happen. Every procedure has risks. For TEER, the main ones are bleeding at the access site, stroke, arrhythmia, and the clip detaching or not holding. Rare but serious risks include tearing of the leaflets or needing urgent surgery. The published rates are low, and the meta-analysis we cited above reports that the safety profile is consistent across large patient groups. No procedure is risk-free, and the honest answer is that the risk of any one complication depends on the patient.
Risks compared with surgery. For patients at high surgical risk, TEER is usually the lower-risk option because it avoids the chest incision and the heart-lung machine. For patients at low surgical risk, surgery is usually the better option because it is more durable and treats the whole valve. The risk comparison is therefore not about the procedure but about who is having it.
What our team checks. In every case we review the risk factors individually, and we explain the risks in plain language so that nothing is assumed. Tell your doctors about any symptoms you notice after the procedure, and ask exactly which signs to watch for. If a complication develops, most are caught early and managed, which is why follow-up is not optional.
Mitral Regurgitation Treatment Without Open Heart Surgery
The full landscape of options. Edge-to-edge repair is one of several options for treating a leaking valve without opening the chest. Others include Tricuspid Valve Repair for patients with a leak in the right-sided valve, Transcatheter Mitral Valve Replacement for patients whose valve cannot be repaired, and Valve-in-valve procedures for patients whose previous bioprosthetic valve has worn out. The choice depends on the valve, the patient, and the timing.
When to treat and when to watch. Not every leaking valve needs an intervention. Mild leaks with no symptoms are monitored. Severe leaks with symptoms or evidence of heart strain need treatment. The guidelines that drive these decisions are international, and our team reviews every case against them before a recommendation is given. We do not push procedures; we explain what the evidence says and what the alternatives are.
What the alternatives are. If the anatomy is not suitable for a clip, the options are not limited to surgery. Some patients are candidates for a newer edge-to-edge device. Others are better served by a Transcatheter Mitral Valve Replacement, where a new valve is placed inside the old one via a catheter. A few need a surgical approach. Our team covers all of these and is trained in each, so we can explain the trade-offs of each route honestly.
How to Choose a Mitral Valve Repair Surgeon?
Volume and experience matter. For any heart valve procedure, the experience of the team matters. Ask how many procedures of the kind being recommended the team performs each year, what the outcomes are, and how the multidisciplinary review is structured. A team that reviews every case in a group meeting before recommending a procedure is a team that takes the decision seriously. Dr Molina trained in cardiothoracic surgery at the Universidad de Guadalajara, in cardiac, minimally invasive, robotic and structural surgery at the University of Montreal, and in structural cardiology and TAVR at CHU Bordeaux, and the team also trained at Jena, Bad Berka and Buffalo. He performed the first robotic mitral valve repair in the Ángeles Health System and the first robotic heart surgery in Guadalajara.
What to ask in the consultation. A good consultation gives you time to ask questions. We take the time to explain what the studies actually show, in plain words, and to answer every question before any decision. Ask about the procedure, the alternatives, the risks, the recovery, and the cost. Ask what happens if the procedure does not work as planned. Ask about follow-up and how long you will need to be seen.
Where we are. Our consulting rooms are in Guadalajara, Querétaro and Hermosillo, and we are a multidisciplinary team of cardiac surgeons led by Dr Alejandro Molina. The first contact is a free video consultation, and a face-to-face visit at the consulting rooms follows when the patient decides to go ahead.
Cost and insurance. The cost of edge-to-edge mitral repair in Mexico depends on the hospital, the device, and the patient's situation, and we discuss it openly during the consultation rather than quoting a number that may not apply. This is a conversation worth having before you commit to anything.
A leaking mitral valve is a serious diagnosis, but it is also a treatable one, and the range of options today is wider than ever. Edge-to-edge repair has earned its place for patients at high surgical risk, and surgical repair remains the gold standard for those who can tolerate it. The right answer depends on your valve, your heart, and your goals. If you have been told you need treatment for a leaking valve, or you are unsure whether edge-to-edge repair mitral valve is right for you, the next step is to talk with a qualified cardiac team. Bring your questions, bring your studies, and bring your doubts. We are here to explain them, and to help you decide with clear facts. Book a consultation with us and we will review your case together.






