

Graft Occlusion After Bypass: Signs and Treatment
Graft occlusion after bypass warning signs, causes and treatments you should know.
If you or someone you love has had coronary artery bypass grafting — the operation that creates new routes for blood around blocked heart arteries — you know how much the surgery itself takes out of a person. What many families are not told clearly is what happens to those new routes in the months and years afterwards. Graft occlusion after bypass, meaning the narrowing or blockage of one of the connected vessels, is one of the most common reasons a patient who felt well after surgery returns with chest pain or shortness of breath. It is not a sign that your surgeon did something wrong, and it is not automatically a catastrophe. But it does deserve attention, and understanding the basics will help you ask the right questions at the right time.
What Is Graft Occlusion After Bypass?
During bypass surgery, a surgeon takes a healthy blood vessel from another part of your body — usually an artery from inside the chest wall or a vein from the leg — and connects it above and below the blocked coronary artery. Blood then flows through this new channel, called a graft, and reaches the heart muscle that was being starved. Graft occlusion simply means that this channel becomes narrowed or blocked again, by clot, by thickening of the vessel wall, or by new disease at the connection points.
Why it happens is not random. The graft is living tissue responding to its new job. Vein grafts in particular were never designed to carry blood under arterial pressure, so their walls thicken over time — a process called intimal hyperplasia. Arterial grafts tolerate the job better, but they too can develop blockages at the stitching points or further along their length.
Occlusion is a spectrum, not a switch. A graft can be mildly narrowed with no symptoms at all, severely narrowed with chest pain on exertion, or completely closed. Some closures are discovered by accident on a routine scan years later, in a patient who feels fine. The clinical significance depends on which artery the graft supplies and how much heart muscle depends on it.
Types of Bypass Grafts and Why They Differ
Not all grafts are the same, and knowing which ones you received helps you understand your own risk profile. Surgeons choose grafts based on the artery being bypassed, the patient's anatomy, and what is available in the chest and legs.
- Arterial graft: the left internal mammary artery, taken from inside the chest wall, is the gold standard for the most important coronary artery (the LAD). Arterial grafts resist thickening far better than veins and often remain open for decades.
- Saphenous vein graft: harvested from the leg, this is still the most widely used conduit for the other coronary arteries. It works well immediately but is more vulnerable to early clotting and to late-wall thickening.
- Other arterial grafts: the radial artery from the forearm and the right internal mammary artery are increasingly used, with patency results generally better than vein in selected positions.
When you review your operative report — and we encourage every patient to keep a copy — look for the terms used to describe your conduits. Ask your surgeon or cardiologist which grafts went to which arteries. This single piece of information shapes every future conversation about monitoring, symptoms and risk.
How Often Do Bypass Grafts Fail?
Families often ask, with real worry in their voices, whether the operation "wears out." The honest answer is that graft failure is common enough to monitor for, and rare enough that most patients never need another operation. The pattern follows a timeline.
The first year carries the highest risk. Early failure is usually clot forming inside a newly connected vein graft, often within days to weeks of surgery, and it is the reason patients are started on antiplatelet medication — usually aspirin, sometimes with a second drug — immediately after the operation. Research has long confirmed that aspirin reduces early vein graft occlusion, which is why it is a standing part of post-operative care.
Years three to ten are the slow-failure window. Vein grafts progressively develop wall thickening and new blockages. Large long-term follow-up studies published in The Lancet have documented that a significant proportion of saphenous vein grafts are occluded or severely diseased a decade after surgery, while arterial grafts fare considerably better. This is one reason surgeons now use arterial grafts more aggressively wherever the anatomy allows.
What this means practically: your risk is not uniform across time. The first months, the first year, and the years after the fifth all carry different patterns of failure, and your follow-up plan should reflect that. Ask for a written monitoring schedule matched to your graft types, because "come back if it hurts" is not a plan.
What Causes Early Graft Occlusion After CABG?
Early occlusion — generally meaning within the first days to months — has its own set of causes, distinct from the slow wear seen later. Understanding them helps explain why your care team does what it does in the hospital and the weeks that follow.
Technical and anatomical factors come first. The size of the target artery matters: grafting a very small coronary artery, or one with heavy disease beyond the connection point, gives blood nowhere good to go, and flow slows. Slow flow invites clot. This is assessed before and during surgery, and it is why some planned grafts are abandoned on the table — a decision that can feel alarming but is actually protective.
Blood biology matters too. Patients who stop antiplatelet drugs early, who have inflammatory states, or who have diabetes with small-vessel disease face higher early risk. Research on myocardial protection, including studies of omega-3 fatty acid pretreatment before elective coronary bypass, reflects the wider effort to reduce the inflammatory injury that grafts and heart muscle endure around surgery.
In-hospital surveillance exists for a reason. Units watch for tell-tale electrocardiogram changes, rising heart-damage markers on blood tests, and new wall-motion abnormalities on echocardiogram in the days after surgery, precisely because a quietly occluding graft is best caught early, when it can often be reopened before heart muscle is lost.

What Are Late Graft Occlusion Symptoms?
Here is the paradox that catches many patients off guard: late occlusion of a vein graft often produces few or no symptoms. Why? Because in many cases the original coronary artery below the graft has developed its own new channels over the years, or the graft was supplying an area that has adapted. A completely closed graft discovered on a scan ten years after surgery is not unusual in a patient with no chest pain.
When symptoms do appear, they usually resemble the symptoms that led to the original operation. That familiarity can be dangerous, because patients sometimes dismiss them: "I already had the surgery, this can't be the same thing." It can be.
- Chest pressure or tightness with exertion — climbing stairs, walking uphill, carrying shopping — that eases with rest.
- Shortness of breath out of proportion to the activity, or a new inability to lie flat at night.
- Palpitations or irregular heartbeat, which deserve evaluation because atrial fibrillation is common after bypass surgery and can itself signal a changing heart.
- Unexplained fatigue — the heart compensating quietly for reduced blood supply.
Any of these after a bypass operation warrants a call to your cardiac team, not a wait-and-see approach at home. New or worsening symptoms in a post-bypass patient are treated with more urgency than the same symptoms in someone who has never had heart surgery.
What Are the Warning Signs of Bypass Graft Failure?
Distinguishing between ordinary post-surgical aches and true warning signs is one of the hardest things for recovering patients. In our consulting rooms in Guadalajara, Querétaro and Hermosillo, the questions we hear most often are exactly these — "is this my incision healing, or is this my heart?" — and taking the time to answer them in plain words is, in our view, part of the treatment.
Signs that need same-day attention: chest pain at rest or pain that does not ease with your usual measures, pain spreading to the jaw, arm or back with sweating or nausea, fainting, or sudden severe breathlessness. These may indicate an acutely occluding graft or a new coronary event, and they belong in an emergency department, not a scheduled clinic.
Signs that need prompt-but-not-emergency review: exertional chest discomfort that is new or has clearly worsened, declining exercise tolerance over weeks, new palpitations, or ankle swelling with breathlessness. These suggest a narrowing that is progressing and should be assessed within days.
Signs that are usually benign but worth mentioning: incisional discomfort, occasional brief stabbing chest twinges with movement or breathing, and fatigue in the early recovery months. Healing sternum and chest-wall nerves produce sensations that mimic cardiac pain remarkably well — but if there is any doubt, let a professional make that call, not an internet checklist.
How Is Graft Occlusion Diagnosed?
Diagnosis follows a logical sequence, and knowing it helps you understand why your doctor orders one test and not another.
Non-invasive tests come first. An electrocardiogram and blood tests for cardiac enzymes are done when symptoms are active. An echocardiogram — an ultrasound of the heart — shows how well the pumping chambers move; a new area of sluggish movement points toward a failing graft supplying that region. Stress testing, whether on a treadmill or with imaging, looks for the regions of heart muscle that run short of blood under exertion.
CT angiography has changed the game. A coronary CT scan can now image the grafts themselves directly, showing narrowing, clot or closure without entering the body. For a patient with suspected graft problems but no active emergency, this is often the next step, and it is far less invasive than the alternative.
Coronary angiography remains the definitive test. A thin catheter is threaded from the wrist or groin into the heart arteries, contrast is injected, and the grafts and native arteries are visualized in real time. It is the test that answers the question with certainty — and it can be converted into treatment in the same sitting if a fixable narrowing is found. When we review a patient's angiogram as a team, we look at every graft and every connection point, not just the artery with the worst picture, because the fix for one failing graft may depend on the state of the others.
What Treatment Options Exist for Graft Occlusion After Bypass?
Treatment depends on three things: how occluded the graft is, which artery it feeds, and how much viable heart muscle depends on it. There is no single answer, and the right choice is genuinely individual.
Medication is always part of the answer. Antiplatelet therapy — aspirin, often with a second agent such as clopidogrel — plus statins to stabilize plaque and slow graft disease, and drugs to control blood pressure and heart rate, form the backbone of management for most graft problems. Even patients who go on to have a procedure continue these medications for life.
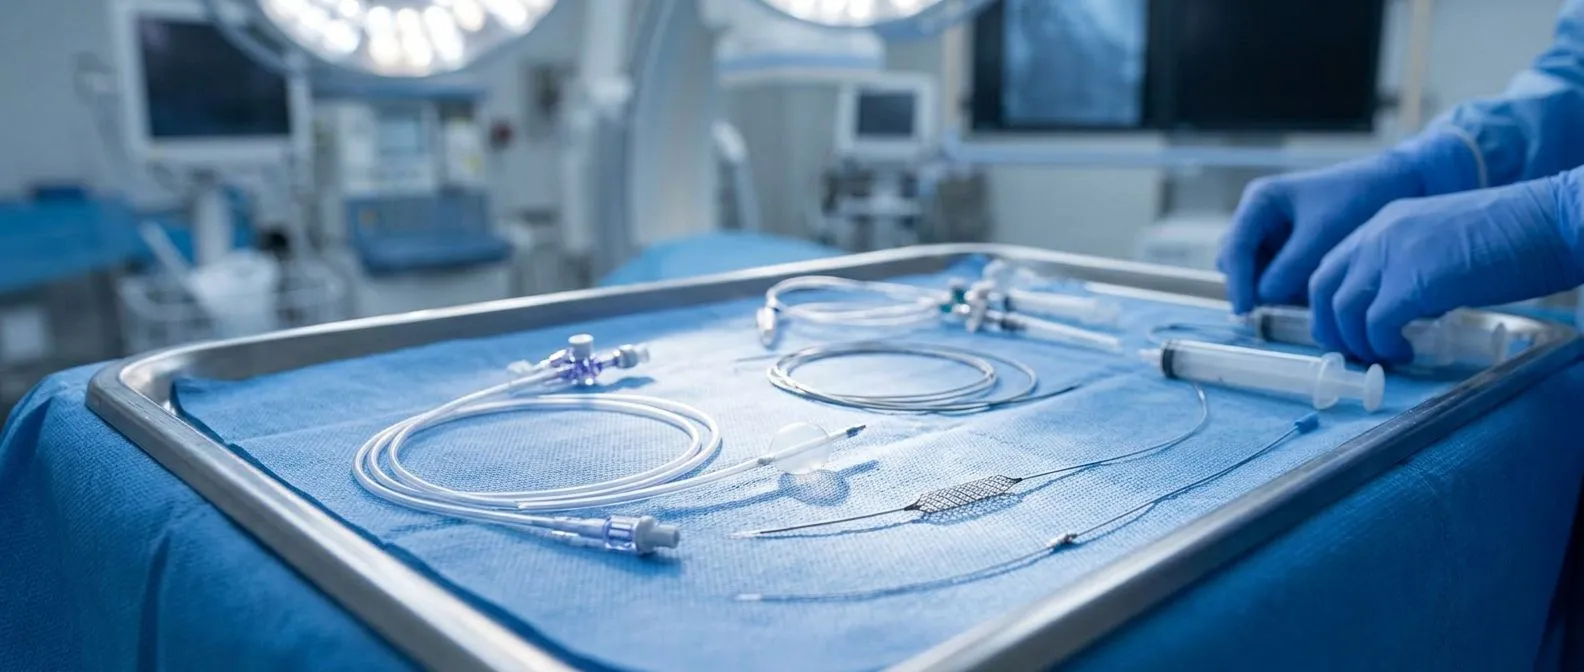
Catheter-based treatment is often possible. Many graft narrowings can be opened with angioplasty and stenting through the wrist or groin — no open surgery. Vein grafts can be stented, and native coronary arteries below a blocked graft can sometimes be opened instead, restoring flow through the original pathway. The choice between stenting the graft versus reopening the native artery is a genuine clinical decision point, and a good team will discuss both.
Redo bypass surgery is reserved for specific situations. When multiple grafts have failed, when the anatomy is not suitable for stenting, or when there is a large territory of threatened heart muscle, a second operation may be the best option. Redo surgery is more complex than the first — scarring makes dissection harder and risk is higher — so it is undertaken only when the benefit clearly outweighs it. Our multidisciplinary team reviews every such case against international practice guidelines before recommending anything, and the patient receives a clear proposal with the alternatives — including doing nothing beyond medication — because the final decision must always be theirs.
How Can You Prevent Graft Occlusion After Bypass?
Prevention after bypass surgery looks a lot like prevention of the original disease, with a few graft-specific additions. None of it is glamorous, and all of it matters.
- Take antiplatelet medication as prescribed. Stopping aspirin early after surgery is one of the most consistent predictors of early vein graft closure. If another doctor suggests stopping it, make sure they know you have grafts.
- Never smoke again. Smoking accelerates graft disease and native artery progression more than almost any other factor. Quitting is the single most powerful thing a bypass patient can do.
- Stay on a statin. These drugs slow the wall thickening that closes vein grafts, and guideline targets for cholesterol after bypass are stricter than for the general population.
- Control blood pressure and diabetes. Both silently damage grafts and remaining arteries. Home monitoring is worth the small effort.
- Attend cardiac rehabilitation and keep moving. Supervised exercise after surgery improves outcomes and, just as importantly, teaches you what your body's normal feels like — so that abnormal stands out.
One more form of prevention deserves mention: follow-up imaging in the years after surgery, even without symptoms, is increasingly used to catch quiet graft disease early. Whether and when to do this depends on your risk profile, and it is a reasonable question to raise with your cardiologist.
What Does Life Look Like After Coronary Bypass Surgery?
Patients often ask about the long view: how long do people live after this operation, and what is the quality of that life? The honest framing is that a successful bypass, cared for properly, very often relieves angina, improves exercise capacity, and allows people to return to work, travel and family life. Survival after bypass is influenced most by the same factors that influenced the disease in the first place — heart function before surgery, kidney health, diabetes, smoking — and by how well the grafts and remaining arteries are protected in the years that follow.
The recovery itself follows a predictable arc. Most patients are up walking within days, home within about a week, and driving again within roughly six to eight weeks once the sternum has healed. Full recovery of energy takes three to six months. Cardiac rehabilitation during this window is not optional polish; it measurably improves outcomes and confidence.
Monitoring is the quiet half of success. A bypass operation is a moment in time; graft health is a lifelong project. Periodic review, honest reporting of new symptoms, and consistency with medication are what convert a good surgical result into a good long-term outcome. Weaning from bypass in the operating theatre, the bypass time on the machine, the patency checks at the end of the operation — all of these matter enormously — but what happens in the ten years after discharge matters just as much.
Some patients are facing their first bypass decision; others are years out from surgery with new questions. Our first contact is a free video consultation, where we get to know you, talk through your condition and your studies, and tell you plainly which additional tests are actually needed so that no unnecessary ones are ordered. Dr Molina trained in cardiothoracic surgery at the Universidad de Guadalajara and in cardiac, minimally invasive, robotic and structural surgery at the University of Montreal, with further training in structural cardiology and TAVR at CHU Bordeaux, and the team also trained at Jena, Bad Berka and Buffalo. If you have had bypass surgery and something has changed — or if you are weighing the decision now — reach out for a consultation rather than trying to answer these questions alone. Your situation deserves a considered answer from a team that has the time to give you one.







