


Heart Auscultation: What Doctors Listen For
Heart auscultation reveals murmurs, valve problems, and rhythm issues in seconds.
What Is Heart Auscultation and Why Does It Matter
Heart auscultation is the clinical practice of listening to the sounds your heart produces as blood flows through its chambers and valves. For patients and families facing a potential cardiac diagnosis, understanding what the doctor is doing with that stethoscope can transform a mysterious ritual into a meaningful medical conversation. Auscultation has been a cornerstone of cardiac evaluation for over two centuries, and despite advances in imaging technology, it remains one of the fastest, safest, and most informative first-line assessments available.
When a cardiologist places a stethoscope on your chest, they are not simply checking whether your heart is beating. They are listening for specific acoustic signatures that reveal how well the valves open and close, whether blood flows smoothly or turbulently, and whether the electrical and mechanical coordination of your heart muscle is functioning properly. Each sound carries diagnostic weight, and patterns of sounds can point toward conditions ranging from innocent physiological murmurs to serious structural valve disease that may require surgical intervention.
The value of heart auscultation lies in its accessibility and immediacy. An experienced examiner can detect a significant murmur, an irregular rhythm such as atrial flutter, or signs of fluid around the heart in a matter of seconds, long before any echocardiogram or blood test is ordered. For patients in Guadalajara, Querétaro, and Hermosillo who may be anxious about cardiac symptoms, knowing that a skilled clinician can gather so much information from listening alone is both reassuring and an important reminder that this step should never be skipped or rushed.
How Heart Auscultation Works: The Stethoscope Examination
The stethoscope is not just a hearing aid; it is a precision instrument designed to transmit specific frequency ranges from the body to the examiner's ears. The bell side picks up low-frequency sounds such as certain murmurs and the rumbling diastolic murmurs of mitral stenosis, while the diaphragm side is tuned for higher-frequency sounds like the sharp closure of normal valves and the clicks produced by mechanical or balloon-expandable valve prostheses. The examiner switches between these surfaces deliberately, depending on what they are trying to detect.
How sound travels from heart to ear: When heart valves snap shut or blood swirls through a narrowed opening, vibrations travel through the chest wall as mechanical waves. The stethoscope captures these vibrations and channels them through tubing to the listener's ears. The thickness of the chest wall, the presence of lung tissue between the heart and the stethoscope, and the patient's body habitus all influence how clearly these sounds are transmitted. A thin athlete may produce crystal-clear acoustics, while a patient with significant adipose tissue or emphysema may muffle the sounds considerably.
Skilled examiners also use positional maneuvers during heart auscultation to bring certain sounds closer to the chest wall. Asking a patient to lean forward while exhaling brings the aortic valve nearer to the stethoscope, making aortic regurgitation murmurs more audible. Turning the patient onto the left side brings the mitral valve into closer apposition with the chest wall, enhancing detection of mitral stenosis. These techniques are not arbitrary; they reflect a deep understanding of cardiac anatomy and acoustic physics working together at the bedside.
Heart Auscultation Points: Where Doctors Listen
Doctors do not listen at just one spot on the chest. Heart auscultation follows a systematic map of four primary listening areas, each corresponding to a specific heart valve, though the sounds do not originate exactly beneath the stethoscope. The aortic area is found at the second intercostal space on the right side of the sternum, the pulmonic area at the second intercostal space on the left, the tricuspid area at the lower left sternal border, and the mitral area at the cardiac apex in the fifth intercostal space at the midclavicular line.
Sound radiates across the chest depending on which valve is involved and what type of abnormality is present. An aortic stenosis murmur, for instance, may be loudest at the aortic area but radiates upward toward the right clavicle and sometimes into the neck. A mitral regurgitation murmur often radiates from the apex toward the left axilla. Understanding this radiation pattern helps the examiner distinguish which valve is producing the abnormal sound, even when the murmur is audible at multiple listening points.
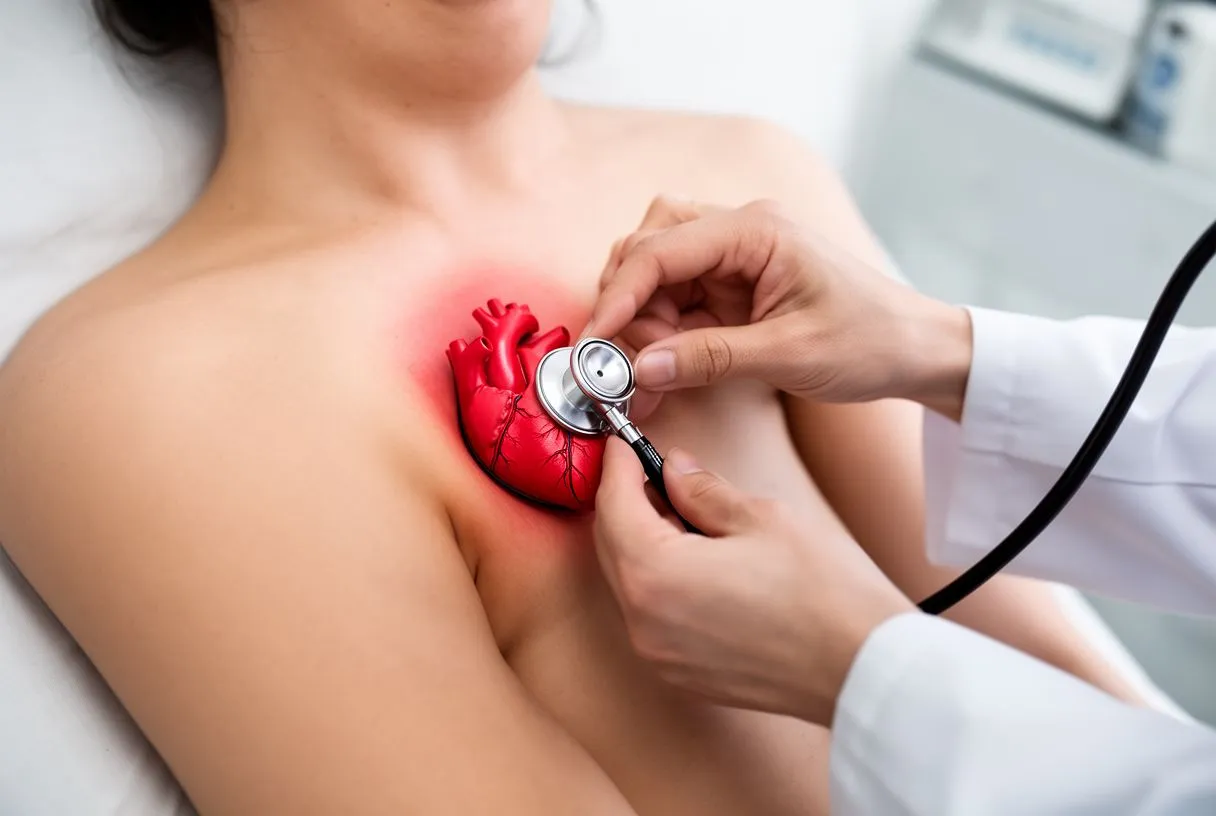
Examiners also listen in less conventional positions when clinical suspicion warrants it. The left sternal border in the third and fourth intercostal spaces is critical for detecting an aortic regurgitation murmur when the patient leans forward and holds their breath in expiration. The back may be auscultated to detect signs of coarctation of the aorta or pericardial friction rubs that radiate posteriorly. A thorough clinician never limits the examination to just four points if the clinical picture suggests a problem elsewhere.
Normal Heart Sounds: S1 and S2 Explained
The two primary heart sounds, often described as "lub-dub," are the acoustic fingerprint of a normally functioning heart. The first heart sound, S1, is produced by the closure of the mitral and tricuspid valves at the beginning of ventricular systole, when the ventricles contract to push blood out to the body and lungs. The second heart sound, S2, results from closure of the aortic and pulmonic valves at the end of systole, when the ventricles relax and begin to fill again. These sounds mark the mechanical rhythm of the cardiac cycle.
Why S1 and S2 split into two components: The two valves on each side of the heart do not close at exactly the same instant. Under normal conditions, the aortic valve closes slightly before the pulmonic valve during expiration, and the separation widens during inspiration due to increased venous return to the right heart. This physiologic splitting of S2 is a normal finding and actually indicates healthy heart function. When splitting becomes fixed or paradoxically reversed, it can signal an atrial septal defect or other structural problems requiring further investigation.
Listening to S1 and S2 also tells the examiner about the integrity of the heart's electrical conduction system. If the PR interval on an electrocardiogram is prolonged, S1 may become softer because the mitral and tricuspid valves have drifted toward a partially closed position before ventricular contraction begins. Variations in the intensity of S1 can also indicate conditions such as atrial flutter, where the atrium contracts irregularly and valve closure timing shifts from beat to beat. These subtle acoustic clues are precisely why heart auscultation remains irreplaceable as a bedside diagnostic tool.
Heart Murmur Sounds: What Extra Noises Mean
A heart murmur is any sound that occurs between or overlapping the normal S1 and S2 sounds, and it is one of the most common findings that brings patients to a cardiologist. Murmurs are generated by turbulent blood flow, which can result from a valve that does not open fully (stenosis), a valve that leaks backward (regurgitation), an abnormal connection between heart chambers, or simply increased blood flow through a normal valve during exercise, fever, or pregnancy. Not all murmurs indicate disease, and distinguishing innocent from pathological murmurs is a core skill in cardiac auscultation.
How murmurs are graded by intensity: Clinicians use a six-point grading scale for systolic murmurs, where grade 1 is barely audible and grade 6 is audible even without the stethoscope touching the chest. The grade does not directly correlate with severity of disease, however. A soft murmur can indicate significant valve narrowing, while a loud murmur may be entirely benign. The character, timing, location, radiation, and response to maneuvers matter more than volume alone. According to research published by JAMA Network, clinician accuracy in auscultation correlates strongly with experience and structured training, underscoring the importance of having a skilled examiner perform the assessment.
The timing of a murmur relative to S1 and S2 is critical for diagnosis. Systolic murmurs occur between S1 and S2 and may be innocent or indicate aortic stenosis, mitral regurgitation, or ventricular septal defect. Diastolic murmurs occur after S2 and before the next S1, and they are virtually always pathological, suggesting conditions such as mitral stenosis or aortic regurgitation. Continuous murmurs that span both systole and diastole may indicate a patent ductus arteriosus or arteriovenous shunt. This timing framework gives the examiner an immediate triage system for deciding which patients need urgent echocardiography and which can be reassured at the bedside.
Abnormal Heart Sounds: Clicks, Rubs, and Gallops
Beyond murmurs, heart auscultation can detect a range of additional sounds that carry specific diagnostic meaning. An ejection click is a sharp, high-pitched sound occurring early in systole, often associated with a bicuspid aortic valve or a stenotic pulmonary valve. A mid-systolic click followed by a late systolic murmur is the classic auscultatory signature of mitral valve prolapse, where one of the mitral leaflets bulges backward into the atrium during contraction. These clicks are subtle but, once recognized, immediately direct the clinician toward targeted imaging.
What a pericardial friction rub sounds like: A pericardial friction rub produces a grating, leather-like sound that can be heard in both systole and diastole, caused by the inflamed pericardial and pleural surfaces rubbing against each other. It is often loudest when the patient leans forward and exhales completely. Detecting this sound is clinically important because it may indicate pericarditis, which can occur after a heart attack, a viral infection, or an autoimmune condition. In some patients, a pericardial effusion large enough to cause tamponade may muffle heart sounds altogether, a dangerous sign requiring immediate intervention.
A third heart sound, S3, occurs just after S2 and produces a gallop rhythm. In adults over forty, an S3 often indicates ventricular dysfunction or heart failure, reflecting a stiff or dilated ventricle struggling to accommodate filling blood. A fourth heart sound, S4, occurs just before S1 and is associated with reduced ventricular compliance, as seen in hypertension or hypertrophic cardiomyopathy. When both S3 and S4 are present, the resulting rhythm is called a quadruple gallop, a serious acoustic warning sign. In rare cases, simultaneous repair of chest wall deformities and cardiac conditions has been documented, as in a case of simultaneous pectus excavatum repair using sternal plate in a patient undergoing the Bentall procedure, which demonstrates how structural abnormalities of the thorax can coexist with complex cardiac surgical needs.
Heart Valve Auscultation: Detecting Valve Problems
Each of the four heart valves produces a characteristic sound when diseased, and heart valve auscultation is the first step in identifying which valve may be failing. Aortic stenosis creates a harsh, crescendo-decrescendo systolic murmur loudest at the aortic area and radiating to the neck. Aortic regurgitation produces a soft, decrescendo diastolic murmur best heard at the left sternal border with the patient leaning forward. Mitral stenosis generates a low-pitched diastolic rumble heard best at the apex with the bell of the stethoscope, while mitral regurgitation causes a holosystolic murmur radiating to the axilla. Tricuspid valve disease is less common but produces similar patterns heard best at the lower left sternal border.
When auscultation findings prompt surgical referral: Auscultation alone cannot determine the severity of valve disease, but it identifies which patients need echocardiographic confirmation. If a murmur suggests significant aortic stenosis, further imaging can measure the valve area and gradient to determine whether the ascending aorta or the valve itself requires replacement. Decisions about surgical timing often depend on whether the aortic diameter exceeds guideline thresholds such as 5.5 cm or whether symptoms such as exertional chest pain or syncope have appeared. In these situations, auscultation serves as the gateway that triggers the entire diagnostic cascade.
For patients who have already undergone valve replacement, auscultation remains a valuable surveillance tool. A mechanical valve produces a distinct metallic click, and changes in the character of that click or the appearance of a new regurgitant murmur can indicate valve dysfunction, thrombosis, or paravalvular leak. Patients who have received a balloon aortic valvuloplasty or who carry a balloon-expandable valve from a transcatheter aortic valve replacement procedure also require periodic auscultation to confirm ongoing valve competence. A new murmur in any of these patients warrants urgent echocardiographic evaluation, and clinicians trained in structured auscultation protocols are demonstrably more accurate at detecting these changes, as confirmed by training studies referenced in magnetic resonance imaging in the evaluation of pectus excavatum and related diagnostic literature.
Pediatric Heart Auscultation: Listening to Children's Hearts
In children, heart auscultation takes on a different character because the pediatric cardiovascular system is still developing, and many normal findings in infants would be pathological in adults. A resting heart rate of 140 beats per minute is normal in a newborn but would be alarming in an adult. Physiologic splitting of S2 may be more pronounced in children due to the thinner chest wall and the higher resting cardiac output relative to body size. Still's murmur, a vibratory systolic murmur common in children aged three to seven, is entirely benign and is one of the most frequently encountered innocent murmurs in pediatric cardiology.
Distinguishing innocent from congenital murmurs: Innocent murmurs in children share certain features: they are systolic, short, soft (grade 1 or 2), vary with position, and have no associated clicks or diastolic components. Pathological murmurs tend to be louder (grade 3 or above), holosystolic or diastolic, associated with thrills, and accompanied by symptoms such as poor feeding, failure to thrive, or cyanosis. Congenital lesions such as ventricular septal defects, coarctation of the aorta, and tetralogy of Fallot each produce distinctive auscultatory findings that an experienced pediatric cardiologist can identify with remarkable accuracy.
For families, the pediatric cardiac examination can be an anxious moment, particularly when a doctor mentions a murmur. It is important to understand that the majority of childhood murmurs are innocent and resolve as the child grows. However, any new murmur in an infant, especially one accompanied by breathing difficulty, sweating during feeds, or poor weight gain, should be evaluated promptly. Pediatric heart auscultation is most reliable when performed by a clinician with specific training in congenital heart disease, which is why referral to a pediatric cardiologist is appropriate whenever uncertainty exists after the initial examination.
Heart Auscultation Technique: What a Proper Exam Includes
A technically complete heart auscultation examination involves more than placing the stethoscope on the chest. The examiner should begin by inspecting the patient for visible signs of cardiac disease, including jugular venous distension, chest wall deformities, and surgical scars from prior procedures such as coronary artery bypass or valve surgery. Palpation follows, checking for thrills (palpable vibrations associated with loud murmurs) and the point of maximal impulse, which may be displaced laterally in patients with an enlarged left ventricle. Only after this groundwork does the listening phase begin.
Key elements of a thorough auscultation exam:
- Systematic coverage: All four primary listening areas plus the axilla, neck, and back, performed with both the bell and diaphragm of the stethoscope.
- Timing and rhythm: Assessment of rate, regularity, and any extrasystoles or pauses, noting whether the rhythm matches what is felt at the wrist.
- Dynamic maneuvers: Valsalva maneuver, squatting-to-standing, hand-grip, and positional changes to provoke or suppress specific murmurs and clarify their origin.
The patient's cooperation matters enormously. Shallow, rapid breathing can obscure low-frequency sounds, while breath-holding at end-expiration reduces lung noise interference. The room must be quiet, the stethoscope tubing intact, and the earpieces properly fitted. These seemingly mundane details are precisely what separates a perfunctory listen from a diagnostic-quality examination, and they explain why the same patient can receive markedly different auscultation findings from different examiners on the same day.
Heart Sound Interpretation: From Stethoscope to Diagnosis
Heart sound interpretation is the cognitive process of translating acoustic patterns into clinical decisions. The examiner integrates what they hear with the patient's history, physical findings, and risk factors to form a differential diagnosis. A new systolic murmur in a patient who has recently had an atypical infarction raises concern for papillary muscle rupture or ventricular septal defect, both of which are surgical emergencies. A diastolic murmur in a patient with long-standing hypertension and atherosclerosis, possibly with elevated Apolipoprotein B levels, suggests aortic regurgitation that may progress and require serial monitoring. Each auscultatory finding is never interpreted in isolation; it is one piece of a larger clinical puzzle.
How auscultation guides the next diagnostic step: When auscultation identifies a significant finding, the next step is typically transthoracic echocardiography to visualize the valves, measure chamber sizes, and quantify any regurgitant or stenotic flow. In patients with complex findings, transesophageal echocardiography or cardiac MRI may be needed for a definitive anatomic assessment. For patients who may require surgery, the cardiac team will also consider factors such as the patient's EuroSCORE II risk stratification, whether they are on medications such as aspirin that may affect perioperative management, and whether conditions like an awake ECMO candidacy might influence the surgical plan. Auscultation findings thus serve as the trigger that sets the entire diagnostic and therapeutic pathway in motion.

For patients and families reading this, the key takeaway is that heart auscultation is far more than a formality. It is a sophisticated diagnostic skill that, when performed by an experienced clinician, can detect valve disease, rhythm disturbances, heart failure, and congenital anomalies at the bedside without any radiation, needles, or cost. If you have been told you have a murmur, or if you experience symptoms such as chest discomfort, exertional shortness of breath, unexplained arm pain, or palpitations, we encourage you to schedule a formal cardiac evaluation. Rather than self-diagnosing based on what you have read, let a qualified cardiac team listen to your heart and guide you toward the right next step for your individual situation.






