


Sinotubular Junction Dilation and Aortic Valve Leaks
Sinotubular junction dilation can cause aortic valve leaks and heart damage.
When a cardiologist mentions that the upper portion of your aorta — the large artery carrying blood out of the heart — has widened, the news can feel alarming, especially when that widening sits dangerously close to the aortic valve. Sinotubular junction dilation is one such finding that often emerges on a routine echocardiogram and leaves patients searching for clear, honest answers about what it means and what comes next.
What is sinotubular junction dilation?
Understanding the anatomy behind the diagnosis: The sinotubular junction is a specific ridge where the aortic root — the segment of the aorta nearest the heart — transitions into the ascending aorta. It sits directly above the three sinuses of Valsalva, the small pouches that house the coronary artery openings and the aortic valve leaflets. When this ridge dilates, the normally precise circumference stretches outward, altering the geometry that keeps the valve leaflets aligned and able to seal shut.
Dilation at this location is not the same as a diffuse aneurysm elsewhere in the aorta. It is a focal enlargement of a structurally critical zone. The aortic valve depends on the sinotubular junction acting as a stable anchor point; the leaflets attach partly to the aortic wall at this level, so any widening pulls their edges apart. Over time, even a modest increase in diameter can prevent the valve from closing completely, allowing blood to leak backward into the left ventricle with each heartbeat.
It is important to distinguish dilation from a true aneurysm, though the terms are sometimes used interchangeably in early reports. Dilation describes measurable enlargement that has not yet reached surgical thresholds; an aneurysm generally implies a more significant expansion carrying higher rupture risk. According to NHLBI, aortic aneurysms often develop silently, which is why surveillance imaging is critical once dilation is documented. The distinction matters because it directly influences how urgently surgery is recommended and which procedure is appropriate for your situation.
How does sinotubular junction dilation cause aortic valve leaks?
The aortic valve is a remarkably elegant structure — three thin leaflets that open fully when the heart pumps blood forward and then fall together to form a tight seal when the heart relaxes. This seal depends on the leaflets meeting at precisely the right height and tension. The sinotubular junction provides the upper geometric frame for this mechanism. When it dilates, the frame widens and the leaflets can no longer reach each other at their central closing point, creating a gap.
Why the leak is called "functional" or "geometric": The leaflets themselves may be perfectly healthy — thin, mobile, and free of calcification or infection. The regurgitation (backward leak) exists not because the valve is diseased but because the supporting structure has changed shape. This is why cardiologists use the term "functional aortic regurgitation." The same principle explains why repairing the aortic root can often restore valve competence without replacing the valve itself.
The volume of the leak depends on how much the junction has dilated and how the leaflets respond. Early on, the leak may be mild and produce no symptoms. As the diameter increases, regurgitation volume grows, and the left ventricle must work harder to accommodate the returning blood. Over months or years, this extra workload can enlarge the ventricle and reduce its pumping efficiency — a process that is often silent until significant damage has accumulated, which is why timing of intervention is so carefully discussed.
What are the symptoms of aortic root enlargement?
Early-stage silence is the norm: Most patients with sinotubular junction dilation experience no symptoms at all. The finding is typically discovered incidentally during an echocardiogram ordered for another reason — a murmur heard during auscultation (listening with a stethoscope), a chest X-ray showing a widened mediastinum, or evaluation of a different valve condition. This asymptomatic window can last years, which is both reassuring and a reason vigilance matters.
When symptoms do appear, they usually reflect either the valve leak that the dilation has produced or the overall strain on the heart. Patients may notice exertional shortness of breath — a sense of breathlessness with activities that previously felt manageable. Some describe palpitations, a pounding sensation in the chest, or an awareness of the heartbeat, especially when lying on the left side. Fatigue, decreased exercise tolerance, and occasionally chest discomfort can also emerge as the left ventricle dilates.
Rarely, the first sign of significant aortic root pathology is more dramatic. If the dilation progresses to a dissection — a tear in the inner lining of the aortic wall — patients experience sudden, severe, tearing chest or back pain that requires emergency attention. This is uncommon with isolated sinotubular junction dilation but underscores why scheduled surveillance imaging and specialist consultation are essential rather than optional for anyone carrying this diagnosis.

How is aortic root dilation diagnosed with echocardiogram?
Transthoracic echocardiography is the primary diagnostic tool for evaluating the aortic root and sinotubular junction. This ultrasound-based test uses sound waves to create real-time images of the heart's structures and measure the diameter of the aorta at multiple levels. The cardiologist measures the aortic annulus, the sinuses of Valsalva, the sinotubular junction itself, and the proximal ascending aorta, comparing each value against established normal ranges adjusted for body surface area.
What measurements mean and how they guide decisions: A sinotubular junction diameter above approximately 3.5 to 4.0 cm in an average adult raises attention, but the decision to intervene is not based on a single number. The rate of growth between scans, the degree of valve regurgitation, the size of the left ventricle, and the patient's underlying connective tissue status all factor in. Serial echocardiograms — repeated at intervals of six to twelve months depending on severity — allow the team to track whether the dilation is stable or progressing, which is often more important than the absolute size at any one visit.
When echocardiographic images are limited by body habitus or when more precise anatomical detail is needed for surgical planning, a CT angiogram or cardiac MRI is obtained. These cross-sectional imaging modalities provide highly accurate measurements of the entire aorta and can detect subtle features such as wall thickening, early dissection, or the presence of atheromatous plaque that might influence the surgical approach. The combination of echocardiography for functional assessment and CT or MRI for anatomical detail gives the surgical team a complete picture before any intervention is recommended.
When to repair aortic root and ascending aorta?
The decision to operate on sinotubular junction dilation is driven by guideline-based thresholds, the presence and severity of valve regurgitation, and individual patient factors. For ascending aorta and root aneurysms in patients without genetic syndromes, surgical intervention is generally recommended when the diameter reaches 5.5 cm. For patients with Marfan syndrome, bicuspid aortic valve, or other connective tissue disorders, the threshold drops to 5.0 cm, and in some cases 4.5 to 5.0 cm if rapid growth or a family history of dissection is present.
Rapid growth is a standalone trigger: Even if the absolute diameter has not reached the surgical threshold, an increase of more than 0.5 cm per year on serial imaging is widely accepted as an indication for operation. This reflects concern that the aortic wall is weakening and that the risk of dissection or rupture is rising faster than the raw numbers suggest. The EuroSCORE II and other risk stratification tools help the surgical team weigh the patient's operative risk against the natural history of the dilation.
Significant aortic valve regurgitation is another independent indication. When the leak caused by sinotubular junction dilation produces symptoms — or when the left ventricle begins to enlarge and its pumping function starts to decline on echocardiogram — surgery is recommended regardless of the aortic diameter. The goal is to intervene before irreversible ventricular damage occurs. Timing the operation in this window, before symptoms become severe, is associated with better long-term outcomes and a more complete recovery, as confirmed by research indexed in PubMed 39537272.
What causes sinotubular junction aneurysm?
The underlying causes of sinotubular junction dilation fall into several categories, and identifying the correct one shapes long-term management. Degenerative changes related to aging and hypertension are among the most common. Chronic high blood pressure places sustained mechanical stress on the aortic wall, gradually weakening the elastic fibers and allowing the vessel to dilate. Over years, this process can produce measurable enlargement at the root level even in patients without any genetic predisposition.
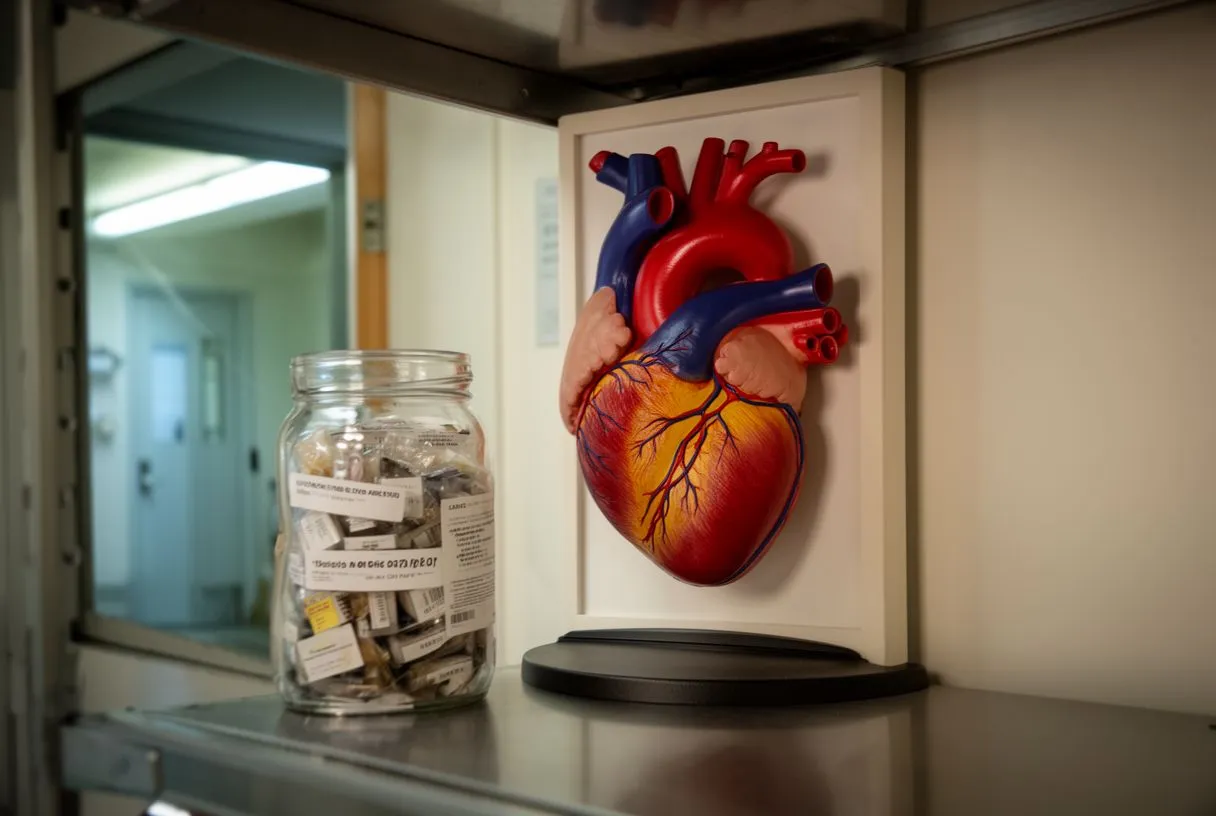
Genetic and connective tissue causes: Marfan syndrome and related fibrillin-related disorders are strongly associated with aortic root dilation that often begins at the sinotubular junction. In these patients, the aortic wall is intrinsically weaker from a structural protein deficiency, so dilation tends to appear earlier in life, progress faster, and occur at smaller starting diameters. Loeys-Dietz syndrome, vascular Ehlers-Danlos syndrome, and Turner syndrome also carry elevated aortic risk. Genetic testing and family screening are often recommended when dilation is diagnosed in younger patients or when the pattern suggests a heritable condition.
Bicuspid aortic valve disease is another major contributor. Approximately half of patients born with a two-leaflet aortic valve develop some degree of aortic dilation over their lifetime, and the sinotubular junction and ascending aorta are frequently involved. The mechanism is partly hemodynamic — altered flow patterns stress the wall — and partly genetic, as the same developmental pathway affects both the valve and the aorta. Inflammatory conditions such as giant cell arteritis, Takayasu arteritis, and certain infections can also produce aortic root pathology, though these are less common and typically accompanied by other systemic symptoms.
How does bicuspid aortic valve dilation affect the aortic root?
Bicuspid aortic valve is the most common congenital heart valve abnormality, affecting roughly one to two percent of the population. Instead of three leaflets, the valve has two, which alters the way blood flows through the aortic root and into the ascending aorta. Over time, these abnormal flow patterns concentrate mechanical stress on specific regions of the aortic wall, and the sinotubular junction is frequently one of the first areas to show measurable dilation.
Why bicuspid valve patients need lifelong aortic surveillance: Even after a bicuspid valve is repaired or replaced, the aorta remains at risk for continued enlargement because the underlying wall abnormality persists. Current guidelines recommend imaging the aorta at regular intervals throughout life, regardless of whether the valve itself has been addressed surgically. The frequency of imaging depends on the current aortic diameter and the rate of growth documented on prior studies, with more frequent monitoring as the diameter approaches surgical thresholds.
When a bicuspid valve patient requires surgery for valve dysfunction, the surgeon simultaneously evaluates the aortic root and ascending aorta. If the sinotubular junction or root exceeds approximately 4.5 cm at the time of valve surgery, concomitant aortic repair or replacement is typically performed to avoid a second operation later. This combined approach reduces overall surgical risk and addresses the full anatomical problem in one setting, which is a principle that experienced cardiac surgeons apply consistently when planning these cases.
What is valve-sparing aortic root replacement (David procedure)?
For patients whose aortic valve leaflets are healthy but whose sinotubular junction dilation has created a significant leak, valve-sparing aortic root replacement offers a surgical solution that addresses the structural problem while preserving the patient's own valve. The David procedure — named after the surgeon who developed it — involves removing the diseased aortic tissue and replacing it with a synthetic graft, while reattaching the native valve leaflets inside the new graft so they function normally within a properly sized frame.
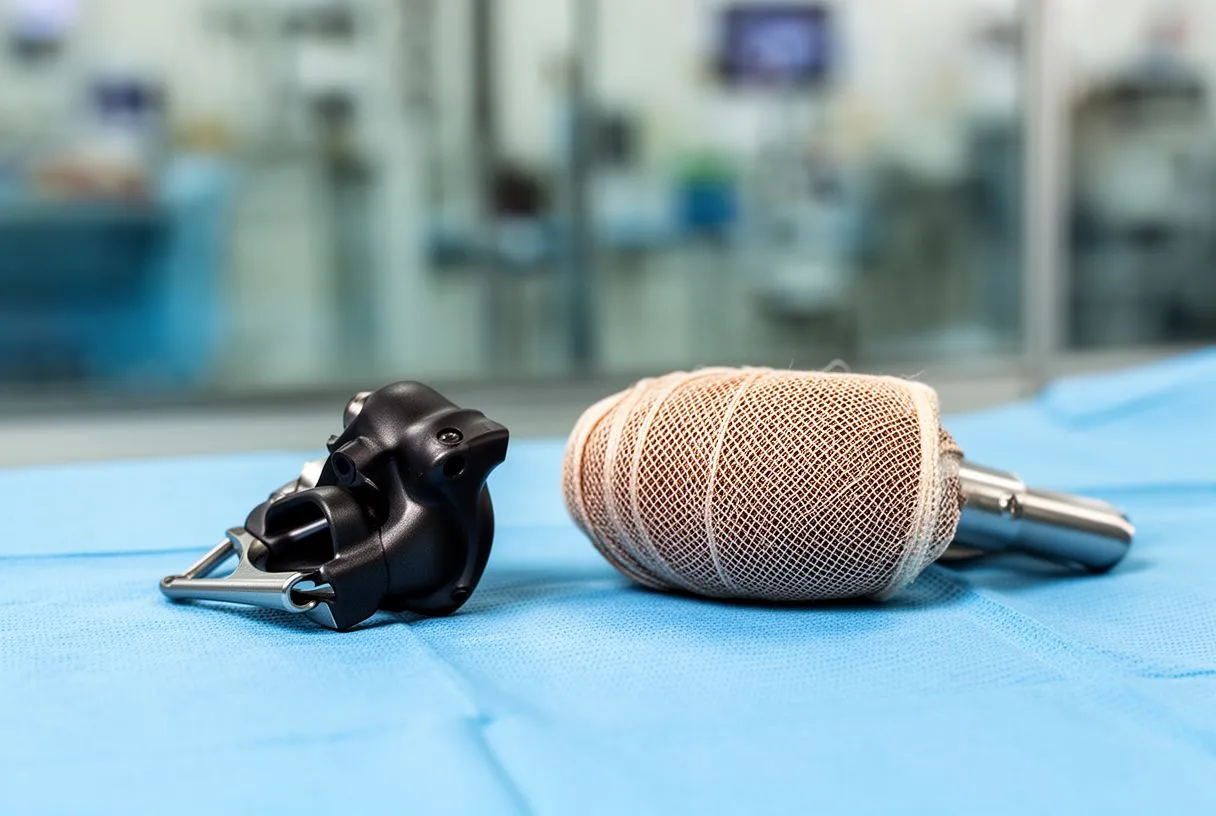
Why sparing the valve matters: A patient's own aortic valve leaflets, when healthy, offer superior durability and hemodynamic performance compared to any prosthetic substitute. Mechanical valves require lifelong blood-thinning medication, and biological tissue valves eventually deteriorate and need reoperation. By preserving the native valve, the David procedure eliminates the need for long-term anticoagulation and avoids the risks of structural valve degeneration, which is especially valuable for younger patients who would otherwise face multiple future surgeries.
The procedure is technically demanding and requires significant surgical expertise, which is why it is performed at specialized centers by surgeons who handle a high volume of aortic root cases. Not every patient is a candidate — the leaflets must be free of significant calcification, infection, or congenital abnormality to function well after reimplantation. When the valve cannot be spared, the surgeon proceeds with a biological or mechanical valve replacement, sometimes using a valved conduit (the Bentall procedure). The choice between approaches is individualized based on valve quality, patient age, and lifestyle considerations, and is discussed thoroughly before surgery.
What is recovery like after STJ dilation surgery?
Recovery from aortic root or ascending aorta surgery follows a structured timeline that patients and families should understand in advance. The operation is performed through a median sternotomy — an incision along the front of the chest — and uses cardiopulmonary bypass, which means the heart is stopped and a machine temporarily takes over circulation. The initial hospital stay typically ranges from five to seven days, with the first one to two days spent in the intensive care unit for close monitoring.
Week-by-week expectations: In the first weeks at home, patients focus on gradual mobilization, wound care, and managing postoperative discomfort. Most people can walk independently within two weeks and resume light daily activities by four to six weeks. Driving is usually restricted for four to six weeks, and lifting anything heavier than approximately five kilograms is avoided during this period to protect the healing sternum. Full recovery, including return to work and moderate exercise, generally occurs within two to three months, though complete bone healing takes longer.

Cardiac rehabilitation is strongly recommended after aortic surgery. This supervised exercise and education program helps patients rebuild cardiovascular fitness safely, monitors for any early complications, and addresses risk factor modification — blood pressure control, lipid management, and smoking cessation where relevant. Long-term follow-up includes annual echocardiograms to confirm the repair remains stable and the aorta shows no new dilation in other segments. For patients with connective tissue disorders or bicuspid valves, this surveillance is lifelong because the underlying tendency to dilate does not disappear after one operation.
When should you seek consultation for aortic valve insufficiency?
If you have been told you have a dilated aortic root, a leaking aortic valve, or a bicuspid aortic valve, the single most important step is establishing care with a cardiac surgery team experienced in aortic root pathology. Even when the current measurements do not meet surgical thresholds, a specialist consultation provides a baseline assessment, confirms the accuracy of your imaging, and creates a surveillance plan tailored to your anatomy and risk profile. Waiting until symptoms become severe is rarely the right approach with aortic disease.
Red flags that warrant prompt evaluation: New or worsening shortness of breath, chest pain, fainting, or a sudden change in exercise tolerance should prompt timely medical attention — not necessarily emergency care, but certainly a cardiology visit within days rather than weeks. If these symptoms are severe or accompanied by sudden tearing pain in the chest or back, emergency evaluation is appropriate, as these can indicate aortic dissection. For stable findings on a routine scan, scheduling a consultation within a few weeks is reasonable and appropriate.
For patients and families considering where to seek this care, Dr Alejandro Molina and the Cirugía de Corazón team in Guadalajara, Querétaro, and Hermosillo provide comprehensive evaluation of aortic root and valve pathology. Every patient's situation is unique — your anatomy, your symptoms, your other health conditions, and your personal priorities all shape the recommendation that is right for you. Rather than self-diagnosing or relying on general information, we encourage you to bring your imaging studies and questions to a consultation where a qualified cardiac surgeon can give you a specific, evidence-based assessment. Book a consultation to discuss your individual case in detail.






