

Transcatheter Mitral Valve Replacement: Who Qualifies
Transcatheter mitral valve replacement candidate guide: learn who qualifies for TMVR, how it works, and what recovery looks like.
Many patients with a leaking or narrowed mitral valve are told they need surgery, but open-heart operations carry real risks for older adults or people with other health problems. A transcatheter mitral valve replacement offers a way to replace the valve without opening the chest, and this guide explains who qualifies, what the procedure involves, and how to decide whether it is the right path for you or a family member.
What Is Transcatheter Mitral Valve Replacement?
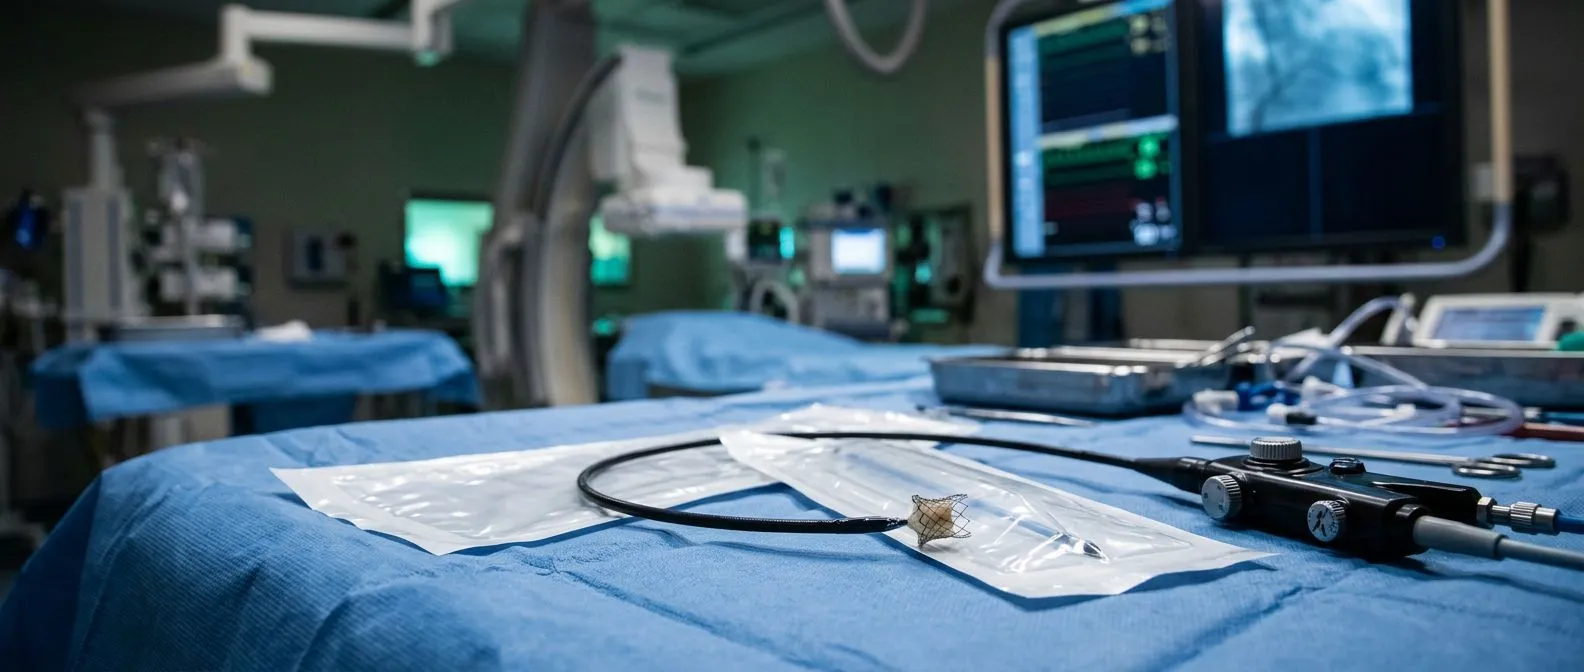
Transcatheter mitral valve replacement (TMVR) is a procedure in which a new valve is delivered to the heart through a thin tube, called a catheter, usually inserted in a blood vessel in the groin. Instead of opening the chest and stopping the heart, the team guides the new valve to the mitral position — the valve between the left atrium and left ventricle — and expands it into place. It is essentially a mitral valve replacement without open heart surgery.
How it differs from surgical replacement is a question patients ask often. In conventional surgery, the surgeon removes the diseased valve and sews in a tissue or mechanical valve through an incision in the chest. In TMVR, the new valve is crimped inside the catheter, travels through the bloodstream, and displaces the old valve rather than removing it. Recovery is measured in days rather than weeks, though not every patient is suitable for it.
The mitral valve itself deserves a word of explanation. It has two delicate leaflets that must open and close with every heartbeat, and it sits in an awkward, saddle-shaped position that is much harder to reach with a catheter than the aortic valve. That is why transcatheter techniques were first perfected on the aortic valve, in a procedure called TAVR, before being adapted to the mitral valve.
Who Is a Transcatheter Mitral Valve Replacement Candidate?
Candidacy starts with the diagnosis. A transcatheter mitral valve replacement candidate is typically a person with severe mitral valve disease — most often severe regurgitation, meaning the valve leaks backward, or significant stenosis, meaning it is stiff and narrowed — whose symptoms persist despite medication. Just as important, the person must be considered high or extreme risk for conventional surgery, because that is the population in which these catheter-based valves have been studied and approved.
Imaging decides most of it. Before any recommendation is made, the team needs an echocardiogram, a computed tomography (CT) scan of the heart, and often a catheterization to look at the coronary arteries. The CT scan measures the size and shape of the mitral annulus — the ring where the valve sits — and checks for calcium deposits. These measurements determine whether a catheter-delivered valve can fit and anchor securely, and they are central to transcatheter mitral valve procedure criteria.
Overall health matters as much as the valve. We review frailty, kidney function, lung disease, and the condition of the access vessels, because a valve is only as good as the patient's ability to recover. Every case in our practice is reviewed by the multidisciplinary team against international practice guidelines before a recommendation is given, and the patient receives a clear proposal with the alternatives, the final decision always remaining theirs.
Severe Mitral Regurgitation Treatment Options Explained
Why the valve leaks in the first place shapes the treatment. In degenerative disease, the valve structure itself is faulty — a condition related to Mitral Valve Prolapse, where the leaflets billow backward. In secondary or functional regurgitation, the leaflets are structurally normal but the heart muscle has stretched, pulling the leaflets apart so they cannot close. These two situations call for very different treatments, which is why severe mitral regurgitation treatment options are never one-size-fits-all.
Medication can steady the situation, especially in secondary regurgitation caused by a weak heart. Drugs that reduce the workload of the heart can lessen the leak's impact and relieve symptoms. But medication does not fix the valve itself, so once symptoms limit daily life despite good medical therapy, intervention becomes the discussion — whether that is repair, surgical replacement, or a catheter-based approach.
For a mitral valve regurgitation interventional treatment, the team weighs three main paths: surgical repair, which remains the gold standard when a patient is fit enough; transcatheter repair with a clip that fastens the leaking leaflets together; and replacement with a catheter-delivered valve when the valve is too damaged to repair. The mitral valve is often called the hardest heart valve to replace precisely because of its anatomy, so choosing between these paths requires careful imaging and honest conversation.
Transcatheter Mitral Valve Repair vs Replacement
Repair keeps your own valve. The best-known transcatheter repair is a clip procedure that grasps the middle of the two leaking leaflets and holds them together, reducing the leak without removing anything. It suits patients with a specific leak pattern — a well-defined jet of regurgitation between the leaflets and leaflets long enough to grasp. When the anatomy fits, repair is often the first catheter-based option considered.
Replacement is reserved for valves beyond repair. In transcatheter mitral valve repair vs replacement discussions, the deciding factors are the amount and location of calcium, the size and mobility of the leaflets, and whether a previous surgical repair or ring has failed. A valve that is heavily calcified, has multiple leak points, or has already been operated on is usually a replacement rather than a repair.
Both are for patients at high surgical risk. Neither approach replaces conventional surgery in a healthy candidate; a younger, fit patient with a repairable valve almost always does better with surgery, because surgical Mitral Valve Repair has decades of durable results. The catheter options exist for people whose age, frailty, or other conditions make open-heart surgery a dangerous proposition — a genuine high risk mitral valve surgery alternative.
Valve-in-Valve and Valve-in-Ring Procedures
A failing surgical valve can sometimes be fixed from inside. When a tissue valve implanted during earlier surgery begins to leak or stiffen, a catheter-delivered valve can be placed inside the old one — a Valve-in-valve procedure. The new valve anchors against the frame of the old one, and the patient avoids a second open-heart operation. This is one of the most established uses of transcatheter technology on the mitral valve.
The same logic applies to failed repairs. If a patient had a mitral ring or band implanted years ago and the valve inside it now leaks severely, a catheter valve can sometimes be seated within that ring. The ring acts as a landing zone, which can make anchoring easier than in a native valve. These valve-in-ring cases are among the more predictable TMVR scenarios.
Not every previous operation helps. Heavy mitral annular calcification — a rock-hard ring of calcium around the valve — is one of the most serious obstacles, because it raises the risk of the new valve displacing or of complications around the implant. A study of 1-Year Outcomes of Transcatheter Mitral Valve Replacement in Patients With Severe Mitral Annular Calcification documented both the feasibility and the elevated risks in this group, which is why we scrutinize the CT scan for calcium before ever offering this option. In our consultation we take the time to explain what the studies actually show, in plain words, and to answer every question before any decision.

Who Is Not a Candidate for Mitral Valve Replacement?
Certain anatomies rule it out. A mitral annulus too large or too small for the available valves, severe calcium in unfavorable positions, leaflets that would obstruct the channel out of the left ventricle, or a left ventricle too small to accept the device all disqualify a patient. This is why heart valve replacement candidacy is decided by imaging first, not by preference.
Certain health conditions do too. An active bloodstream infection, an infection on a Prosthetic Valve Endocarditis history in the recent past, severe unfixable lung disease, or a heart too weak to tolerate the procedure can each make TMVR unsafe. Patients with disease in other valves — for example severe aortic stenosis needing an Aortic Valve Replacement — are usually better served by a single operation addressing everything at once, if they can tolerate surgery.
Being told "no" is not the end of the road. In our practice we encourage second opinions and treat seeking one as a normal part of deciding about heart surgery, because candidacy judgments vary between teams and devices evolve. Elderly mitral valve surgery options have expanded enormously, and a patient turned down at one center may have a viable path — a different device, a different approach, or a combination strategy — at another.
What Happens During the Transcatheter Mitral Valve Procedure?
Access is the first decision. Most commonly the catheter enters through the femoral vein in the groin and is threaded up to the right side of the heart, where a small hole is made between the atria to reach the mitral valve from above. Some cases use a small incision at the chest apex instead. Because transcatheter procedures use percutaneous closure techniques for the access site, bleeding management is a refined part of the operation, as described in case reports such as Achieving Hemostasis Posttranscatheter Aortic Valve Replacement Using Perclose Device — a technique the same principles apply to in TMVR access.
The implant itself is guided by live imaging. Throughout the procedure, the team uses ultrasound of the heart (transesophageal echocardiography) and X-ray fluoroscopy to position the valve millimeter by millimeter. The new valve is advanced, positioned across the diseased mitral valve, and then expanded — either by a balloon or by releasing its self-expanding frame. The team checks immediately that it sits securely, leaks minimally, and does not block the flow out of the left ventricle.
It is a major procedure done in a hybrid operating room. Patients sometimes ask whether catheter-based means "minor." It does not. General anesthesia, a heart-lung backup plan, and a full surgical team are standard, because complications — however uncommon — need to be handled on the spot. In our practice we perform conventional, minimally invasive, robotic and transcatheter procedures, and we recommend the less invasive route only where the evidence supports it for that patient.
Recovery, Life Expectancy and Valve Durability
Recovery is genuinely faster than open surgery. Most patients who undergo a transcatheter mitral procedure walk within a day or two, and many go home within several days, compared with the weeks a full sternotomy demands. Soreness is limited to the access site rather than the chest bone. Cardiac rehabilitation: what it is and who it is for becomes relevant here — a supervised program of exercise and education that helps patients regain strength safely, and which we recommend after nearly every valve intervention.
Life expectancy depends on the whole heart, not just the valve. These procedures are offered to patients who were already high risk, so outcomes reflect that starting point. What the procedures reliably deliver is relief from severe symptoms, fewer hospitalizations, and improved quality of life. For otherwise healthy surgical patients, long-term survival after a Mitral Valve Replacement is typically driven by age, heart function, and other conditions rather than the valve operation itself.
How long does a transcatheter mitral valve last? The honest answer is that these valves are newer than surgical tissue valves, so the longest follow-up data are still maturing. Tissue valves in general degenerate over years — a Porcine Valve, for instance, is made from pig tissue and eventually stiffens. What current evidence shows is that the catheter valves perform well in the years studied, and the Valve-in-valve technique now offers a way to replace a worn transcatheter valve without open surgery, extending the practical lifespan of the treatment.
How Successful Is Transcatheter Mitral Valve Replacement?
Success rates depend on the indication. For valve-in-valve and valve-in-ring cases, the technique is well established and the results are consistently good. For native valves, TMVR remains more complex and is offered at experienced centers with careful selection. Patients often also ask how successful a mitral valve clip is — the repair device — and the answer there is that for the right leak pattern, the clip reduces the leak and improves symptoms in the large majority of properly selected patients, though some patients need a second procedure or still require medication afterward.
The risks are real and should be named plainly. They include bleeding at the access site, stroke, the valve shifting out of position, obstruction of the left ventricular outflow tract — the channel blood takes out of the heart's main pumping chamber — and infection. None of these are common, but all are reasons why candidacy must be judged by imaging and by an experienced team, not by symptom severity alone.
Is TAVR considered a major surgery? It is a major procedure, though not a conventional open-heart operation. The same applies to TMVR. Dr Molina trained in structural cardiology and TAVR at CHU Bordeaux. Patients who understand the risks before the procedure tend to recover with more confidence than those who were simply reassured. We never claim painless or risk-free; we claim a carefully chosen, carefully executed procedure.
Transcatheter Heart Valve Evaluation and Next Steps
A proper transcatheter heart valve evaluation follows a sequence, and knowing it helps families prepare. The goal is a complete picture of the valve, the heart, and the person — assembled before anyone talks you into or out of anything.
- Echocardiogram: shows how badly the mitral valve leaks or narrows, and how the pumping chambers are coping.
- CT scan of the heart: measures the annulus, maps calcium, and checks whether a catheter valve can physically fit and anchor.
- Coronary catheterization: rules out blocked arteries that would need treatment alongside the valve.
- Surgical risk assessment: a scoring of age, frailty, kidney and lung function that determines whether catheter-based or surgical treatment is the safer path.
Questions to bring to any consultation are worth writing down in advance. Ask which treatment the team recommends and why, what the alternatives are, who will perform each part of the procedure, what happens if the valve cannot be delivered safely mid-procedure, and what follow-up looks like over the first year. A team that answers these comfortably is a team you can trust.
If you are considering treatment in Mexico, our consulting rooms in Guadalajara, Querétaro and Hermosillo serve both local and international patients. The first contact is a free video consultation: we get to know the patient, talk through the condition, and say which studies are still needed so no unnecessary ones are ordered; a face-to-face visit follows when the patient decides to go ahead. The mitral valve deserves a deliberate, unhurried decision — and the final word is always yours. To close: a transcatheter mitral valve replacement is neither a cure-all nor an experimental gamble; for the right patient, it is a well-supported way to replace a failing valve without open-heart surgery, and the only way to know whether you are the right patient is to sit down with a qualified cardiac team.






