


Aortic Dissection Repair Recovery: The First Year
Dissection repair recovery in your first year: hospital milestones, blood pressure control, cardiac rehab, returning to work, warning signs, and follow-up care.
The first year after aortic dissection repair is a journey with clear stages — and knowing what to expect at each one makes the road feel far less frightening. A dissection is a tear in the inner layer of the aorta, the large artery that carries blood from the heart to the rest of the body. Repairing it is major surgery, and dissection repair recovery unfolds in weeks and months, not days. This guide walks you through the first year: the hospital stay, the healing milestones, the checks your team will perform, and the warning signs that always deserve a call.
What Is Aortic Dissection Repair?
An aortic dissection happens when the inner lining of the aorta tears. Blood then pushes into the wall of the artery, splitting it into two channels. This is a true cardiovascular emergency, because the weakened wall can rupture or cut off blood flow to vital organs. Repair means replacing or reinforcing the damaged section of the aorta, usually with a synthetic tube, so blood flows through a single, safe channel again.
Why the repair matters: the goal is not just to close the tear. The surgeon protects the heart, the brain, and the spinal cord from the consequences of the dissection, and prevents the aorta from enlarging into a Thoracic Aortic Aneurysm later. Some patients need a Surgical Aortic Valve Replacement at the same time if the valve at the aortic root has been damaged. Every decision is made against the patient's specific anatomy.
Where the surgery happens: the approach depends on which part of the aorta is involved. The ascending aorta, the section closest to the heart, is almost always treated with open surgery. The descending aorta, further down the chest, can often be treated with Endovascular Aneurysm Repair, a catheter-based technique that places a stent-graft through a small incision in the groin. In our practice, every case is reviewed by the multidisciplinary team against international practice guidelines before we recommend an approach, and we choose the less invasive route only where the evidence supports it for that patient.
What Are the Two Types of Aortic Dissection?
Doctors classify dissections into two main types, based on where the tear begins. The distinction drives everything: the urgency, the treatment, and the shape of your recovery.
- Type A Aortic Dissection: the tear involves the ascending aorta, the segment that leaves the heart directly. This is the most dangerous form and almost always requires urgent open surgery, because the risk of rupture, heart attack, or stroke is immediate.
- Type B Aortic Dissection: the tear begins after the arch, in the descending aorta. Many Type B cases are managed first with medication to control blood pressure, and only need surgery or stenting if complications appear — such as continued expansion, organ malperfusion, or a Penetrating Aortic Ulcer.
Why the type matters for your recovery: Type A patients typically face a longer, more demanding recovery because the surgery involves the heart itself, often with a period of deep hypothermia during the operation. Type B patients who undergo endovascular repair may recover faster physically, but still need the same vigilance with blood pressure and follow-up imaging. Knowing your type is the first step in understanding your own timeline.
What Are the Symptoms of a Dissection?
The classic symptom is sudden, severe chest or back pain, often described as tearing or ripping, and different from anything the person has felt before. Pain may move as the dissection extends — from the chest to the back, the abdomen, or the legs. Some patients collapse, or show signs of stroke or limb ischemia if blood flow to those territories is compromised.
Recognizing Acute Aortic Syndrome: dissection belongs to a family of acute aortic conditions that also includes intramural hematoma and penetrating ulcer. The common thread is sudden pain in the chest, back, or abdomen. Hypertensive emergency is a frequent companion: very high blood pressure both triggers and worsens the tear, which is why blood pressure control is central to both prevention and recovery. In our consultation we take the time to explain what each imaging study actually shows, in plain words, so patients and families understand exactly what happened and why.
Who is at risk: the main driver is long-standing high blood pressure, but other factors matter — a bicuspid aortic valve, inherited conditions such as Marfan syndrome, and prior damage from Rheumatic Heart Disease in some populations. Aortic dissection is a true cardiovascular emergency: if you or someone near you experiences sudden tearing pain, call emergency services immediately. Never wait to see if it passes.
How Is a Dissection Surgically Repaired?
Open surgery for Type A: the surgeon replaces the damaged ascending aorta with a synthetic graft, often under deep hypothermic circulatory arrest — cooling the body to protect the brain while the aorta is opened. If the aortic root or valve is involved, the surgeon may perform a Surgical Aortic Valve Replacement or a valve-sparing root repair. Some patients also need coronary artery reimplantation onto the graft.
Endovascular repair for Type B: through a small incision, a catheter delivers a stent-graft that lines the aorta from the inside, sealing the tear and rerouting blood flow through the graft. This is the same principle as Endovascular Aneurysm Repair for Abdominal Aortic Aneurysm, and it avoids opening the chest. Newer research, including work on how the structural helicity of aortic dissection influences endovascular repair outcomes, is helping teams refine which patients do best with this approach (Influences of structural helicity of aortic dissection on endovascular repair).
Choosing the right option: the decision weighs the type of dissection, the patient's age and overall condition, the anatomy of the aorta, and the urgency of the situation. We always give the patient a clear proposal with the alternatives, and the final decision is always theirs — we encourage second opinions and treat seeking one as a normal part of deciding about heart surgery.
Dissection Repair Recovery Timeline: The First Weeks
Days 1–3 in the hospital: after open surgery, you will wake in the intensive care unit with a breathing tube, which is usually removed within the first day. Monitoring is continuous, and a chest tube drains fluid from around the heart and lungs. Some patients need temporary support with an Intra-aortic Balloon Pump to help the heart while it recovers from the operation.
Days 4–10 in the Recovery Room and step-down ward: once stable, you move to a monitored ward. You will sit up, stand, and begin walking a few steps each day. Pain is managed with medication and improves steadily. Bowel function, appetite, and sleep return gradually. The sternum, if opened, is held together with wires and needs several weeks to knit — you will be told to avoid lifting, pushing, or pulling anything heavy.
Weeks 2–6 at home: the sternum healing rules dominate this phase. No driving, no lifting more than a few kilograms, no pushing or pulling. You will walk daily, gradually increasing the distance — this is the single most important activity you can do. Fatigue is profound and normal; your body is healing from a massive operation.
Blood Pressure Management After Dissection Repair
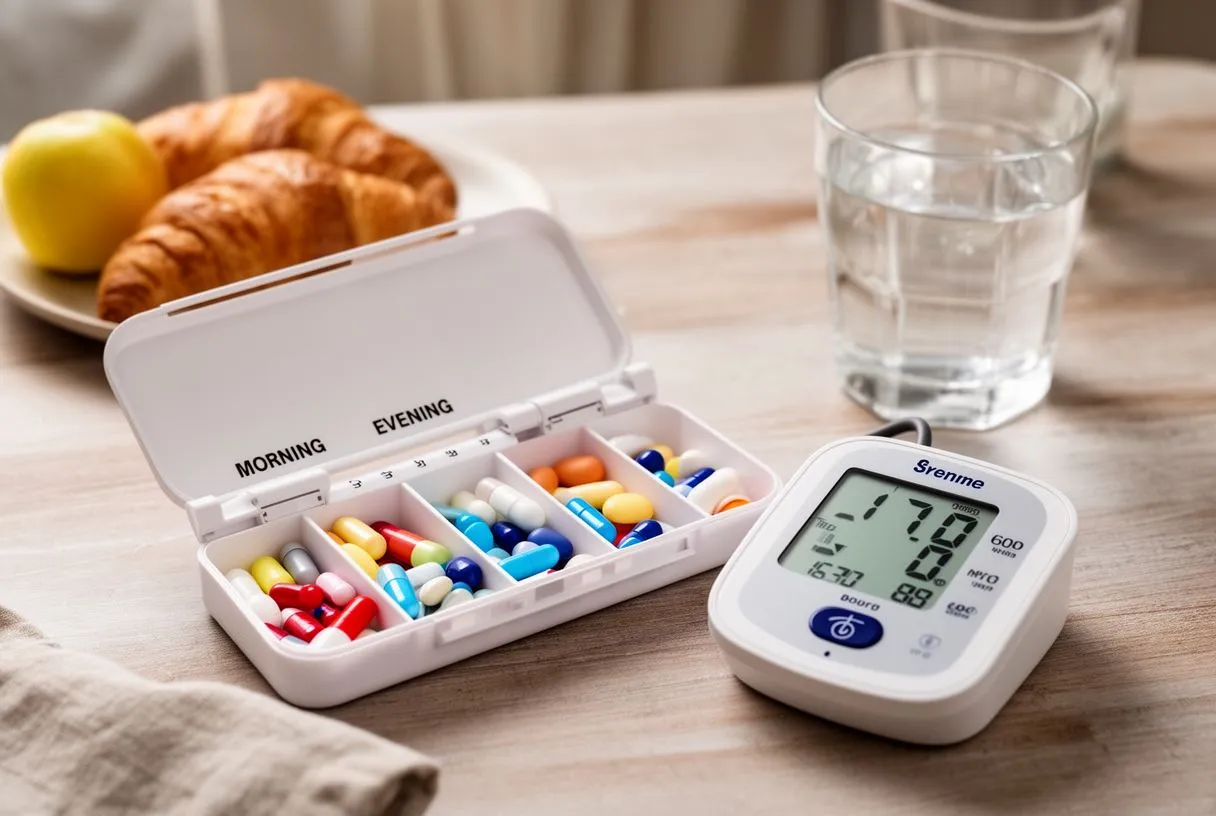
Why blood pressure is the central issue: after a dissection, the rest of the aorta remains vulnerable. High blood pressure stresses the repaired segment and the remaining weakened wall, and it is the single strongest modifiable factor for preventing further problems. The remainder of the aorta can still dilate over years, so pressure control protects the long-term.
Medication after repair: nearly every patient leaves the hospital on multiple blood pressure medications — typically a beta-blocker to slow the heart rate and reduce the force of each beat, plus additional agents to reach target levels. These medications are not optional; they are the foundation of your protection. Your team will adjust doses over the first weeks to reach the individual targets set for your case.
Home monitoring: you will be asked to measure your blood pressure at home, at consistent times, and record the readings. This is not a chore — it is the data your team uses to fine-tune your treatment. Patients who monitor faithfully give their doctors far better information than those who rely on office visits alone. Home readings and imaging are usually reviewed at each follow-up, and any change in the plan should be made with the patient, never over their head.
Cardiac Rehab After Aortic Dissection
What cardiac rehab is: a supervised program of monitored exercise, education, and support that begins a few weeks after surgery and typically continues for several months. It is one of the most evidence-backed interventions in cardiac care, and it is strongly recommended after dissection repair.
What it involves: each session is supervised, with your heart rhythm and blood pressure watched as you exercise on a treadmill or cycle. You progress at a pace set by your own response, not by a fixed calendar. Alongside exercise, the program covers nutrition, stress management, medication understanding, and returning to daily life.
Why it matters for dissection patients: the controlled exercise helps rebuild endurance safely, while the education reinforces the blood pressure habits that protect you long-term. Patients who complete cardiac rehabilitation often recover confidence faster, so ask whether a structured program near your home is suitable for you.

Returning to Work and Driving After Dissection Repair
Driving after aortic dissection surgery: after open surgery through the sternum, most patients are told to wait about 6–8 weeks, ensuring they can react safely and are not restricted by pain or medication. Rules vary by country and insurance, so confirm with your surgical team before getting behind the wheel.
Returning to work: the timeline depends on the kind of work you do.
- Desk work: many patients return around 6–8 weeks, sometimes with reduced hours at first.
- Physical labor: jobs involving lifting, pushing, or heavy machinery usually require 3 months or more, and often a graded return with modified duties.
- Driving for work: professional drivers face longer restrictions, and your team must certify your fitness for the specific requirement.
Planning the return: go back gradually. A phased return — part-time hours, lighter duties, longer breaks — works far better than a full restart. Tell your employer what you can and cannot do, and let your surgical team write a letter if needed. When a patient is preparing to return to work, we sit down with them in the consultation and map out a realistic plan together, because the final decision on pace is always theirs.
Emotional Recovery After Heart Surgery
The experience is real: surviving a dissection is dramatic — often an emergency admission, a sudden operation, and a brush with mortality. Afterward, many patients feel anxious, low, or irritable, and some find sleep difficult or experience vivid memories of the event. These reactions are common and are part of emotional recovery, not a sign that something is wrong with the repair.
What helps: talking openly with family, joining a support group, and asking for professional help if the feelings persist or interfere with daily life. Cardiac rehab programs often include emotional support as part of the structure, which is one more reason to attend. Gentle routine — regular sleep, daily walks, a return to familiar activities — restores the sense of normalcy faster than waiting for it to arrive on its own.
For families: watching a loved one recover from a dissection is also frightening. Families should feel free to ask the surgical team about what they observed, and to seek support themselves. A calm, informed household is one of the strongest predictors of a smooth recovery. In our practice we always make space for the family in the consultation, because the patient's recovery depends on the people around them as much as on the surgery itself.
Warning Signs and Follow-Up Care After Aortic Dissection
Follow-up imaging schedule: after repair, you will need regular imaging — typically CT or MRI scans — to confirm that the repaired segment stays stable and that the rest of the aorta does not enlarge. The first scan usually happens within the first few months, with further scans at intervals your team sets based on the findings. These scans continue for life, and they are the reason early warning of any new problem is possible.
Long-term recovery and life expectancy: patients who survive the initial event and follow up faithfully can live long, full lives. Factors that shape the long-term outlook include whether the remaining aorta stays stable, how well blood pressure is controlled, and whether other conditions — kidney, coronary, or valve disease — are managed. Follow-up scans are usually compared against international practice guidelines, and you should be told plainly what the images show and what, if anything, needs to change.
When to call your doctor after dissection: know the warning signs and act on them without hesitation.
- Sudden, severe chest, back, or abdominal pain: call emergency services immediately — this is the same symptom as the original dissection and must be treated as such.
- Signs of complications after dissection repair: fever, increasing wound redness or drainage, new swelling in the legs, breathlessness at rest, or palpitations — contact your team promptly.
- Uncontrolled blood pressure at home: readings persistently above your targets, or symptoms of very low pressure, deserve a call before they become a crisis.
Life after the first year: by the end of the first year, most patients have returned to normal activities, completed cardiac rehab, and settled into a routine of home monitoring and scheduled imaging. The habit of vigilance becomes part of ordinary life rather than a source of anxiety. The most important takeaway is simple: dissection repair recovery is a partnership between you and your cardiac team, and honest communication at every step is what protects you long-term.
If you or a loved one are facing aortic dissection, or you are recovering from repair and want a clear, plain-language plan for the year ahead, we invite you to book a free video consultation with our team. We are a multidisciplinary team of cardiac surgeons led by Dr Alejandro Molina, with consulting rooms in Guadalajara, Querétaro and Hermosillo, and we will review your situation, explain the studies in plain words, and tell you which studies are still needed — no unnecessary ones, and the final decision always yours.






