


Atherosclerosis Treatment: From Lifestyle to Bypass Surgery
Atherosclerosis treatment spans lifestyle changes, medication, and bypass surgery.
If your cardiologist has mentioned blocked coronary arteries, you have probably heard the phrase heart bypass surgery and wondered what it actually involves. It is one of the most studied and refined operations in modern medicine, yet for patients and families it can feel like a fog of unfamiliar terms. This guide walks you through what the surgery is, how it is performed, what recovery genuinely looks like, what care in Mexico costs, and the questions worth asking before you commit to anything.
When Do You Need Heart Bypass Surgery?
Why blockages form in the first place: Coronary arteries feed the heart muscle itself. Over years, cholesterol and inflammatory cells can build plaque inside these vessels, a process called atherosclerosis. When plaque narrows an artery enough, the heart muscle receives less oxygen-rich blood, causing chest pain or breathlessness. If a plaque ruptures, a clot can form and trigger a heart attack. Johns Hopkins Medicine notes that coronary artery disease is among the leading causes of death worldwide, which is why treatment decisions matter so much.
When medication is enough, and when it is not: Not every narrowing needs surgery. Many patients do well for years with medicines that lower cholesterol, control blood pressure, and reduce clot risk. Surgery enters the picture when blockages are severe, when several vessels are diseased, when the main left artery is critically narrowed, or when symptoms persist despite full medical treatment. Imaging studies and pressure measurements inside the artery guide this decision, not guesswork.
How the decision is actually made: In our practice, every case is reviewed by a multidisciplinary heart team before any recommendation is made. The patient receives a clear proposal with the alternatives explained in plain words, and the final decision is always theirs.
What Is Coronary Artery Bypass Grafting?
The concept in one sentence: Coronary artery bypass grafting, usually abbreviated CABG, is an operation that creates a new route for blood to flow around a blocked coronary artery, much like a detour road built around a collapsed tunnel. The surgeon attaches a healthy blood vessel, called a graft, from another part of your body so blood can reach the heart muscle beyond the blockage.
Where the grafts come from: Surgeons typically use the internal thoracic artery from inside the chest wall, the radial artery from the forearm, or the saphenous vein from the leg. Arterial grafts tend to stay open longer, so the left internal thoracic artery is the preferred conduit for the most important coronary artery in most patients. The body compensates remarkably well after these vessels are borrowed.
Bypass versus stent: A stent is a small mesh tube placed through a catheter to prop an artery open; it treats one or two blockages without surgery. Bypass treats the whole coronary tree at once and is generally favored when there is disease in multiple vessels, in diabetics with complex anatomy, or when the left main artery is involved. Both are legitimate treatments; the right one depends on your specific anatomy, and a good heart team will show you the images and explain why one suits you better.
How Is Heart Bypass Surgery Performed Step by Step?
Preparation: You arrive at the hospital the day before or the morning of surgery. Blood tests, a chest X-ray, and sometimes a CT scan are reviewed. An anesthesiologist places monitoring lines, including an arterial line for continuous blood pressure. You are given general anesthesia and fall asleep knowing the team is watching every number on the screen.
Harvesting the grafts: While the chest is prepared, another part of the team removes the planned vessels. Vein harvesting can be done through small incisions or endoscopically, leaving minimal scarring and reducing leg discomfort afterwards.
The operation itself: The surgeon opens the breastbone to reach the heart. If the heart-lung machine is used, blood is diverted through it so the heart can be temporarily stopped and the delicate suturing done on a still field. The grafts are sewn in place, one end beyond the blockage and the other to the aorta or chest-wall artery. Once the connections are complete, the heart is restarted, the chest is closed with wires, and you are taken to the intensive care unit. The whole operation commonly takes three to five hours.
On-Pump vs Off-Pump Bypass Surgery: Which Is Right for You?
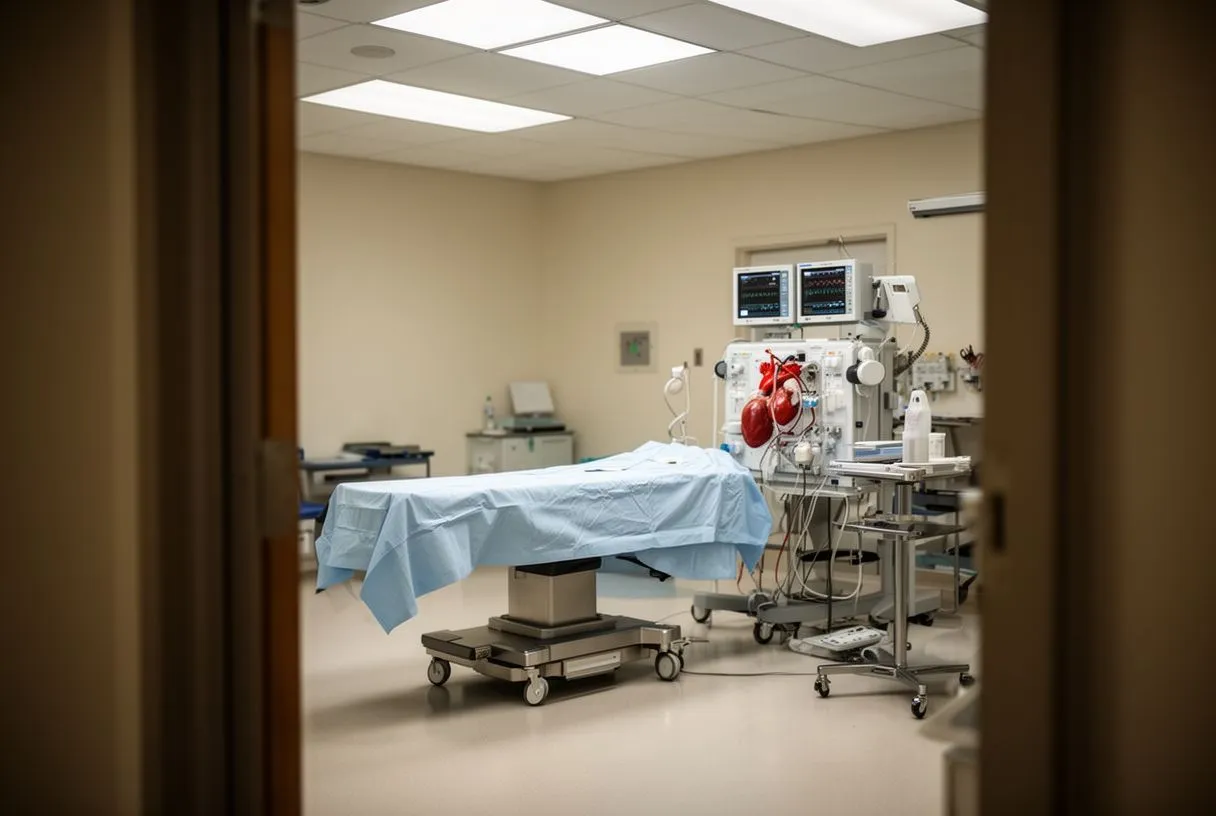
Two established techniques: In on-pump bypass, the heart-lung machine takes over circulation while the heart is stopped, giving the surgeon a motionless, bloodless operating field. In off-pump bypass, the surgeon operates on the beating heart with a stabilizing device, avoiding the machine altogether. The National Heart, Lung, and Blood Institute describes both approaches as accepted standards, and large studies have shown comparable outcomes for most patients.
How the choice is made: Off-pump may be considered for older patients, those with calcified aortas, or people at higher risk from the machine itself, such as patients with kidney disease or previous strokes. On-pump remains the standard for complex multi-vessel cases because the still field allows more precise, complete revascularization. Neither is universally better; the honest answer is that the technique should follow the patient, not the surgeon's habit.
We perform both conventional on-pump and beating-heart off-pump techniques, and we recommend the less invasive route only where the evidence supports it for that specific patient. In the consultation, we explain which approach fits your anatomy and why, in words you can repeat to your family.
What Is Bypass Surgery Recovery Really Like?
The first days: You wake in the intensive care unit with breathing support already removed or coming out within hours, chest tubes draining fluid, and lines monitoring your heart. Most patients sit on the edge of the bed and take their first steps within 24 to 48 hours, which feels impossible and is essential. Walking prevents lung complications and blood clots.
Weeks one through six: Hospital stay is usually five to seven days. At home, fatigue dominates the first few weeks; this is normal, not a setback. The breastbone takes about six to eight weeks to knit, so during that time you must not lift anything heavier than a few kilograms, drive, or push a shopping cart. Cardiac rehabilitation, a supervised program of progressive exercise, is one of the strongest predictors of a good long-term outcome and should be treated as part of the surgery itself, not an optional extra.
Weeks six through twelve: Most patients return to desk work around two to three months. Emotional ups and downs, including tearfulness or low mood, are well documented after open-heart surgery and deserve open conversation with your team rather than silent endurance.
Before discharge, ask for a written day-by-day recovery plan so your family knows what to expect at home and when to call.
What a proper quote includes: A trustworthy estimate should be all-inclusive. Before you commit, ask specifically about:
- surgeon and team fees, including anesthesia and perfusion.
- hospital and intensive care charges, including expected days of stay.
- preoperative studies, graft materials, and disposables.
- how many days you should plan to stay in the city before flying home.
Honesty about the unknowns: No surgeon can promise zero complications, so a serious practice will tell you how an extended ICU stay or an unexpected need would be handled and billed. In consultation, the team reviews each patient's studies and gives a clear proposal with the alternatives.
Travel logistics: Patients usually arrive several days before surgery for final studies and stay roughly two weeks after discharge before flying. Long flights in the first weeks after cardiac surgery carry clot risk, so your team should clear the timing individually. Booking flexible return tickets is a small precaution that removes real stress.
What Does Heart Bypass Surgery Cost in Mexico?
What a proper quote includes: A trustworthy estimate should be all-inclusive. Before you commit, ask specifically about:
- surgeon and team fees, including anesthesia and perfusion.
- hospital and intensive care charges, including expected days of stay.
- preoperative studies, graft materials, and disposables.
- how many days you should plan to stay in the city before flying home.
Honesty about the unknowns: No surgeon can promise zero complications, so a serious practice will tell you how an extended ICU stay or an unexpected need would be handled and billed. In our consultations, we review each patient's studies and give a written, itemized proposal so there are no surprises, and we are happy to explain every line of it.
Travel logistics: Patients usually arrive several days before surgery for final studies and stay roughly two weeks after discharge before flying. Long flights in the first weeks after cardiac surgery carry clot risk, so your team should clear the timing individually. Booking flexible return tickets is a small precaution that removes real stress.
What Are the Risks and Benefits of Bypass Surgery?
The honest risk picture: For elective bypass in reasonably healthy patients, operative mortality in experienced centers is low, but risks are real and include bleeding, infection of the chest wound, irregular heart rhythms such as atrial fibrillation, stroke, and kidney stress. Age, diabetes, lung disease, and emergency status raise these numbers. A good surgeon will quote your individual estimated risk, not a generic brochure figure.
The benefit picture: Bypass reliably relieves angina, improves exercise capacity, and in certain groups, particularly diabetics with three-vessel disease and patients with left main disease, offers a survival advantage over other strategies. The American Heart Association emphasizes that surgery works best when it is paired with lifelong control of cholesterol, blood pressure, and smoking, because the grafts protect you only as well as the habits around them protect the rest of your arteries.
What long-term life looks like: Most patients describe freedom from the chest pain that defined their previous years. Grafts have lifespans: arterial grafts frequently last decades, vein grafts somewhat less. Follow-up with your cardiologist, medication adherence, and cardiac rehabilitation are what turn a successful operation into a successful recovery.
Why Choose a Heart Surgeon in Guadalajara?
Training and credentials you can verify: Guadalajara is home to one of Latin America's strongest cardiac traditions. When comparing surgeons, ask where they trained, how many procedures of your specific type they perform yearly, and whether they are board certified in cardiac surgery. Volume and verified training matter more than marketing.
Dr Alejandro Molina leads a multidisciplinary team in Guadalajara that reviews every case against international practice guidelines, and we encourage second opinions as a normal part of deciding about heart surgery rather than as an insult to anyone.
Communication in your language: For international patients, the difference between a good and a great experience is usually communication: a team that explains the plan in plain language, answers emails before travel, and involves your family in decisions. Ask whether the surgeon personally performs the operation and personally sees you afterwards, or whether an anonymous team does the follow-up.
Second opinions cost nothing but confidence: Any surgeon confident in their plan will welcome your wish to have the recommendation reviewed elsewhere. If a team resists a second opinion or pressures you to decide quickly, treat that as a signal about them, not about you.
Questions to Ask Your Heart Team
Before surgery: Come to your consultation with questions written down; good surgeons expect it and take the time seriously. The most useful ones include:
- How many vessels are blocked, and why do you recommend bypass over a stent for my anatomy?
- What is my individual estimated operative risk, and what are the most likely complications for someone like me?
- Will I need the heart-lung machine, and what is the plan if something changes during surgery?
- What exactly is included in the quoted cost, and what would an unexpected complication change?
After surgery: Ask when you can drive, return to work, resume exercise, and travel by plane. Ask which symptoms at home mean "call today" versus "go to an emergency room." And ask about cardiac rehabilitation; patients who ask this question tend to actually attend the program.
The decision that is genuinely yours: The heart team proposes; you decide. Take the time to understand your images, your risk, and your alternatives. The National Heart, Lung, and Blood Institute offers reliable plain-language material for patients weighing these choices, and a trustworthy surgeon will encourage you to read it. Heart bypass surgery is a major but well-understood operation with decades of evidence behind it; with the right team, a clear plan, and honest conversation about cost and recovery, it remains one of the most effective ways to restore blood flow to the heart and reclaim an active life. If you are considering surgery in Guadalajara or anywhere in Mexico, book a consultation and bring your questions; that conversation, not an internet search, is the right first step.






