

Splinter Haemorrhages: A Nail Sign of Endocarditis
Splinter haemorrhages endocarditis link explained.
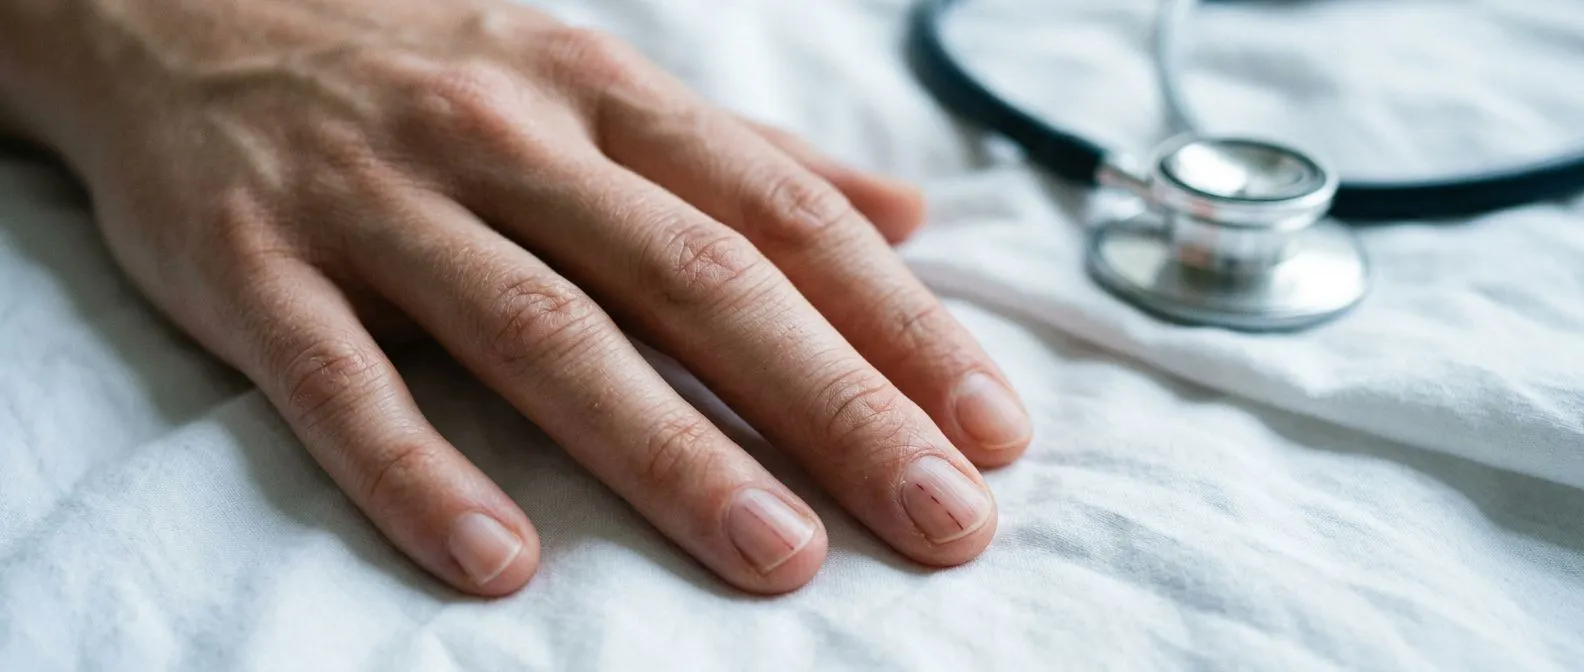
Splinter haemorrhages are thin, dark red or brownish lines that appear beneath the fingernails or toenails, running lengthwise along the nail bed. While many people first notice them after a minor injury or trauma to the nail, these distinctive markings can sometimes signal a deeper medical issue — most notably infective endocarditis, a bacterial infection of the heart's inner lining and valves. Understanding when these nail changes are harmless and when they warrant prompt medical evaluation can make a meaningful difference in early diagnosis and treatment outcomes.
What Are Splinter Haemorrhages in the Nails?
Appearance and location: Splinter haemorrhages look like tiny splinters of wood trapped under the nail, typically measuring one to three millimetres in length. They form in the distal third of the nail plate — the portion furthest from the cuticle — and appear as linear, reddish-brown streaks that do not fade when you press on the nail surface. The colour comes from small amounts of blood leaking from the tiny blood vessels, called capillaries, that run longitudinally through the nail bed.
How they develop: Each nail bed contains a network of microscopic blood vessels arranged in parallel ridges. When a vessel ruptures, blood tracks along these ridges, creating the characteristic splinter-shaped mark. Because the nail grows forward at roughly three millimetres per month, a mark that appears near the cuticle today will gradually migrate toward the fingertip over several weeks, eventually growing out entirely and disappearing.
For most people, a single splinter haemorrhage on one nail is the result of minor trauma — bumping a finger, catching a nail on a door, or even aggressive manicure. These isolated marks are common and almost always benign. However, when multiple marks appear simultaneously across several nails, especially in someone with no history of recent nail injury, the clinical significance shifts and further investigation becomes warranted.
How Do Splinter Haemorrhages Connect to Endocarditis?
The endocarditis link: Infective endocarditis occurs when bacteria — most commonly streptococci or staphylococci — enter the bloodstream and settle on the heart's valves or inner lining. As the bacteria multiply, they form vegetations: clusters of bacteria, blood cells, and protein debris that cling to valve tissue. These vegetations are fragile and periodically break off, sending small fragments called emboli into the circulation, where they can lodge in small blood vessels throughout the body, including those in the nail beds.
When an embolus from an infected heart valve reaches the narrow capillaries of the nail bed, it blocks blood flow and causes the vessel to rupture. The resulting haemorrhage produces exactly the kind of linear streak we recognise as a splinter haemorrhage. Because endocarditis continually sheds emboli, multiple nails are often affected over a short period — a pattern that distinguishes endocarditis-related marks from the single, trauma-induced mark most people experience. According to WebMD, this systemic embolisation is one of several classic peripheral signs of infective endocarditis that clinicians look for during physical examination.
It is important to understand that splinter haemorrhages are not always present in endocarditis, and their absence does not rule out the diagnosis. In fact, they appear in only a minority of confirmed cases. When they do occur alongside other signs — such as a new heart murmur detected on auscultation, persistent fever, and unexplained weight loss — they form part of what clinicians call the clinical picture that points toward a heart valve infection requiring urgent investigation.
What Other Conditions Cause Splinter Haemorrhages?
Non-cardiac causes: While endocarditis is the cardiac cause most people associate with splinter haemorrhages, several other conditions can produce identical nail findings. Trauma remains the single most common cause, but among systemic illnesses, conditions that damage blood vessels or increase their fragility are the leading culprits. Vasculitis — inflammation of the blood vessels — can weaken vessel walls throughout the body, including the delicate capillaries of the nail bed, leading to repeated micro-haemorrhages.
Several medications can also contribute. Long-term use of blood thinners, including aspirin taken at cardiovascular doses, may make capillaries more prone to minor leakage. Patients undergoing chemotherapy or taking certain immunosuppressive drugs sometimes notice multiple splinter haemorrhages as a side effect of reduced platelet function. Additionally, conditions such as chronic kidney disease can alter blood vessel integrity and produce nail-bed bleeding that mimics the appearance of endocarditis-related marks.
A fascinating and rare cause involves connective tissue disorders and congenital vascular abnormalities. For instance, Williams syndrome — a genetic condition affecting elastin production in blood vessels — can lead to arterial narrowing and unusual vascular findings from an early age. A case documented in A Case of William's Syndrome in a Ugandan Child illustrates how congenital cardiovascular anomalies can manifest with surprising vascular signs even in low-resource settings where advanced imaging is not readily available.
Splinter Haemorrhages Symptoms Beyond the Nail Bed
Accompanying cardiac symptoms: When splinter haemorrhages are related to endocarditis, they almost never appear in isolation. Patients typically describe a constellation of symptoms that developed over days to weeks, including persistent low-grade fever, night sweats, fatigue, and a general sense of being unwell. These systemic symptoms reflect the body's response to bacteria circulating in the bloodstream and the ongoing inflammatory process on the heart valves.
Some patients also notice changes in their breathing or heartbeat. A new or worsening heart murmur — detected when a clinician listens to the chest with a stethoscope — is one of the most significant findings, as it suggests a valve is no longer closing or opening properly due to vegetations. In some cases, arrhythmias such as atrial flutter, a rapid and irregular rhythm originating in the upper chambers of the heart, can develop when infection irritates the heart's electrical conduction system. Patients may sense this as palpitations or a racing pulse.
Other peripheral signs of endocarditis can accompany splinter haemorrhages. These include Janeway lesions — small, painless red spots on the palms or soles — and Osler nodes, which are tender bumps on the finger pads. Some patients develop microscopic blood in the urine when emboli damage the kidneys, or small retinal haemorrhages visible only on eye examination. Together, these findings help clinicians distinguish endocarditis from benign causes of nail-bed marks.
How Are Splinter Haemorrhages and Endocarditis Diagnosed?
The diagnostic process: When a patient presents with multiple splinter haemorrhages and suspicious symptoms, the diagnostic pathway begins with a thorough clinical history and physical examination. The clinician will ask about recent dental work, intravenous drug use, pre-existing heart valve disease, prosthetic valves, and any history of congenital heart conditions — all factors that raise the likelihood of endocarditis. The examination includes careful listening to the heart for murmurs and assessment of other peripheral signs.
If endocarditis is suspected, blood cultures form the cornerstone of diagnosis. At least three sets of blood samples are drawn from different sites over a period of hours to identify the specific organism causing the infection. An echocardiogram — an ultrasound of the heart — is performed to visualise the valves directly and look for vegetations. Transthoracic echocardiography is performed first, but if images are inadequate or clinical suspicion remains high, transoesophageal echocardiography provides more detailed views of the valves and any attached growths.
In complex or unusual presentations, additional imaging may be necessary. A case reported in Frontiers in Cardiovascular Medicine describes a rare coronary anomaly initially presenting with ventricular arrhythmias — a reminder that cardiac symptoms can stem from unexpected structural abnormalities rather than classic valve infection. This underscores why a systematic, stepwise diagnostic approach matters: jumping to conclusions based on nail findings alone can lead to both missed diagnoses and unnecessary anxiety.
When Should Splinter Haemorrhages Prompt a Cardiac Evaluation?
Red flags that warrant urgent attention: Not every splinter haemorrhage requires a trip to the cardiologist, but certain combinations of findings should prompt immediate medical evaluation. The key distinction lies in context: a single mark on one nail after a known injury is almost always benign, while multiple new marks appearing across several nails without trauma — especially with fever or other systemic symptoms — demands prompt assessment.
- Multiple new marks: Several splinter haemorrhages appearing on different nails within a short period, without any remembered trauma.
- Persistent fever: A temperature above 38°C that does not resolve within 48 hours, especially with night sweats or chills.
- New heart murmur: A sound detected by a clinician that was not present on previous examinations, suggesting valve involvement.
- Breathing changes: New shortness of breath, especially with exertion, or a noticeable decrease in exercise tolerance.
Patients with pre-existing heart valve conditions, prosthetic valves, or a history of endocarditis should treat any new splinter haemorrhages with heightened vigilance. The same applies to individuals who have recently undergone procedures that can introduce bacteria into the bloodstream. In these higher-risk groups, even a few nail marks accompanied by mild symptoms can represent early endocarditis, and the threshold for seeking evaluation should be correspondingly lower. Early treatment dramatically improves outcomes, whereas delayed intervention increases the risk of permanent valve damage and embolic complications.
What Is the Treatment for Splinter Haemorrhages Endocarditis?
Antibiotic therapy as first-line treatment: When endocarditis is confirmed, treatment begins immediately with intravenous antibiotics, typically administered in hospital for four to six weeks. The specific antibiotic regimen depends on the organism identified in blood cultures, whether the infection involves a native or prosthetic valve, and the patient's overall health. Splinter haemorrhages themselves require no direct treatment — they resolve gradually as the underlying infection is controlled and no new emboli are shed from the valve.
In some cases, antibiotics alone are insufficient. Surgery becomes necessary when vegetations are large enough to pose a high risk of embolisation, when infection has destroyed valve tissue causing heart failure, when the infection does not respond to antibiotics, or when complications such as abscess formation extend beyond the valve into surrounding heart structures. Surgical options range from valve repair to valve replacement, and in some patients, procedures such as balloon angioplasty may be needed to address concurrent coronary artery disease that becomes apparent during the diagnostic workup.
Recovery from endocarditis is a long process that extends well beyond the hospital stay. Patients typically complete their antibiotic course through a peripherally inserted central catheter, with regular blood tests to monitor inflammation markers. Follow-up echocardiograms track valve function over months. Some patients need long-term aspirin or other blood-thinning medication, particularly if they have a prosthetic valve. The cardiac team will also address any underlying conditions — such as dental disease — that contributed to the infection, to reduce the risk of recurrence.
Are Splinter Haemorrhages Always a Sign of Heart Infection?
Putting risk in perspective: The short answer is no — the vast majority of splinter haemorrhages are entirely benign. Most people who notice these marks have simply injured a nail without remembering the specific event. Activities as routine as opening a tight jar, gripping a steering wheel for a long drive, or playing certain sports can generate enough micro-trauma to produce a visible nail-bed bleed. When a single mark appears on a single nail and no other symptoms are present, the likelihood of endocarditis is extremely low.
Even among patients hospitalised with confirmed endocarditis, splinter haemorrhages appear in only a fraction of cases — and when they do, they are accompanied by other clear signs of serious illness. While peripheral signs like splinter haemorrhages, Osler nodes, and Janeway lesions are traditionally taught as hallmarks of endocarditis, their actual sensitivity is limited and they should never be used as standalone diagnostic evidence. The clinical context, not the nail mark alone, determines whether further investigation is warranted.
The practical takeaway for patients and families is one of proportionate response. If you notice a splinter haemorrhage and feel well, with no fever, no fatigue, no breathing changes, and no other unexplained symptoms, monitoring the mark over the following days is reasonable. If it grows out normally and no new marks appear, reassurance is appropriate. However, if multiple marks develop simultaneously, if they are accompanied by any systemic symptoms, or if you have a known heart condition, seeking professional evaluation is the responsible course.
Can You Prevent Splinter Haemorrhages and Heart Valve Infections?
Prevention through good valve health: Preventing endocarditis — and by extension the splinter haemorrhages it can cause — centres on reducing the entry points for bacteria into the bloodstream. For most people, routine dental hygiene is the single most effective preventive measure. Regular brushing, flossing, and professional cleanings keep gums healthy and prevent the bacteria that live in the mouth from entering the bloodstream through inflamed or bleeding gum tissue.

- Maintain excellent dental hygiene: Brush twice daily, floss once daily, and schedule professional cleanings every six months to prevent gum disease that can allow oral bacteria to enter the bloodstream.
- Ask about antibiotic prophylaxis: If you have a prosthetic valve, prior endocarditis, or certain congenital heart conditions, discuss whether a single preventive antibiotic dose before dental procedures is appropriate for you.
- Avoid intravenous drug use: This is one of the most common pathways for bacteria to enter the bloodstream and attack heart valves, particularly the tricuspid valve on the right side of the heart.
- Keep up with cardiac follow-up: If you have known valve disease, regular echocardiograms and clinical reviews ensure changes are detected early before complications develop.
For patients at higher risk, guidelines recommend a single dose of preventive antibiotics before specific dental and medical procedures. This prophylaxis is not recommended for everyone and should be discussed with your cardiologist, who will weigh your individual risk against the potential side effects. Maintaining good overall cardiovascular health — managing blood pressure, avoiding smoking, and keeping conditions like diabetes well controlled — supports the integrity of heart valves and blood vessels, reducing susceptibility to infection.
Recovering From Endocarditis: Long-Term Outlook With Splinter Haemorrhages
What to expect after treatment: For patients who have undergone treatment for endocarditis, the long-term outlook depends on how quickly the infection was diagnosed and treated, whether valve damage occurred, the type of organism involved, and the patient's overall cardiovascular health. Many patients recover fully with no lasting valve damage, particularly when treatment begins early and the infection responds well to antibiotics. Splinter haemorrhages that were present during the acute illness gradually grow out with the nail and disappear entirely within a few months.
Some patients, however, are left with permanent valve damage that requires ongoing management. A narrowed or leaking valve may need eventual surgical repair or replacement, and prosthetic valves come with their own long-term considerations, including the need for lifelong blood thinners and regular monitoring. Patients who have had endocarditis once are at higher risk of a second episode, which means vigilance about any new symptoms — including new splinter haemorrhages — becomes a permanent part of their health awareness. The atrium and valve structures, once damaged by infection, may not fully recover their original strength and function.
If you or a family member have noticed splinter haemorrhages and are concerned about the possibility of endocarditis or another heart condition, the most important step is to speak with a qualified cardiac team. Nail findings, while sometimes informative, are only one small piece of a much larger clinical picture. A thorough evaluation — including history, examination, and appropriate testing — provides the clarity needed to either offer reassurance or guide treatment. We encourage you to book a consultation with our team to discuss your specific situation rather than relying on self-diagnosis. Every patient's cardiac history, risk factors, and symptoms are unique, and decisions about further investigation should always be made in partnership with experienced cardiac professionals.






