Total Anomalous Pulmonary Venous Drainage: Surgical Repair
Total anomalous pulmonary venous drainage repair explained by Guadalajara heart surgery specialists.
What Is Total Anomalous Pulmonary Drainage
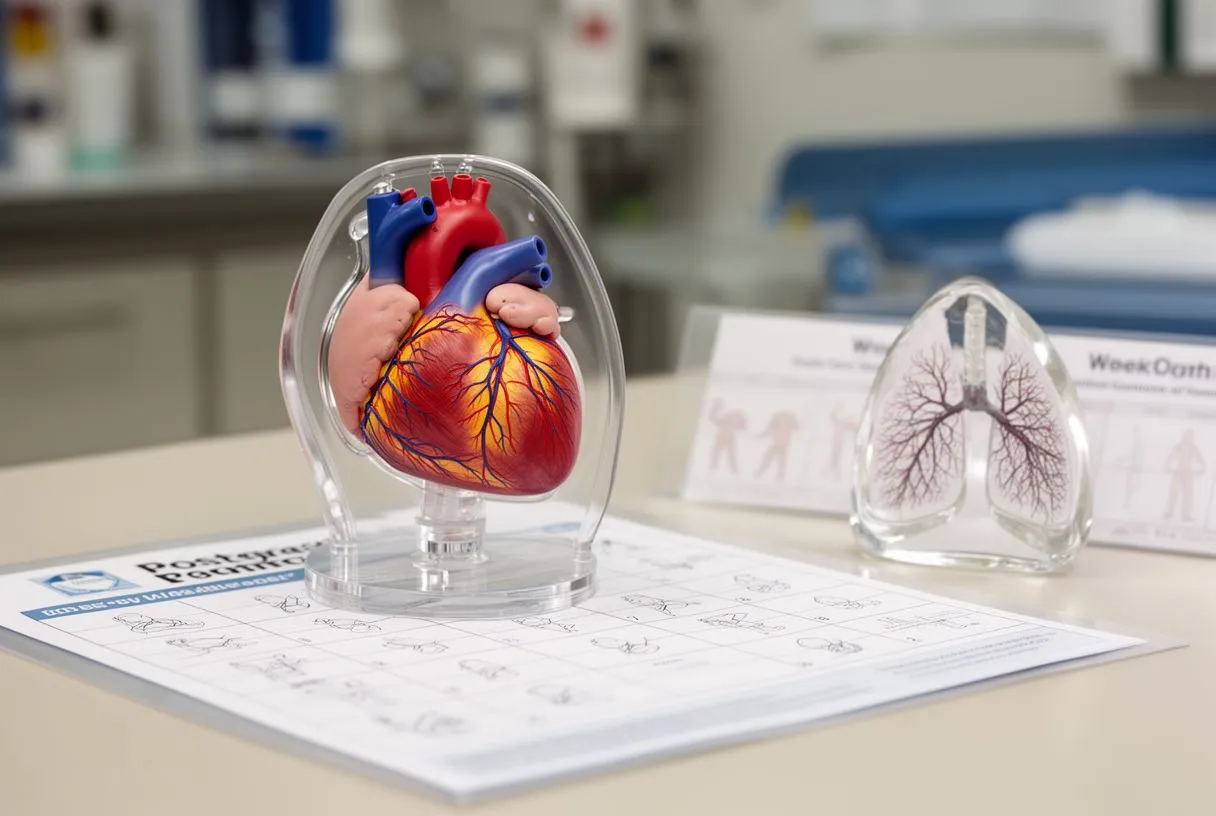
Total anomalous pulmonary venous drainage is a rare congenital heart defect in which all four pulmonary veins — the vessels that should carry oxygen-rich blood from the lungs back to the left atrium — instead connect abnormally to other parts of the circulation. Instead of draining into the left side of the heart, the pulmonary veins route oxygenated blood into the systemic venous system, meaning it returns to the right atrium or nearby vessels. This creates a situation where oxygen-rich blood mixes with oxygen-poor blood, and the left side of the heart receives less blood than it should. Anatomical root cause: during fetal development, the pulmonary veins fail to connect normally to the left atrium, so they remain attached to vestigial venous channels that drain elsewhere in the body.
Babies born with this condition typically show signs within hours or days of birth. The most common symptoms include rapid breathing, a bluish tint to the lips and skin called cyanosis, poor feeding, and lethargy. The severity depends largely on whether the abnormal venous pathway is obstructed — when blood flow from the lungs is blocked, the condition becomes a surgical emergency. When the pathway is unobstructed, the baby may appear stable for weeks, though still requiring planned surgical correction. Clinical evaluation begins with careful auscultation, listening for heart murmurs, and confirming anatomy with echocardiography.
For families receiving this diagnosis, the news can feel overwhelming. It helps to understand that total anomalous pulmonary venous drainage repair is a well-established operation that redirects blood flow back to its correct pathway. The condition is sometimes associated with other complex cardiac anomalies, such as Tetralogy of Fallot or atrial septal defects, which the surgical team will evaluate during planning. Understanding the anatomy and what the surgery corrects is the first step toward informed decisions.
How TAPVR Repair Surgery Works
The goal of TAPVR repair is to re-route oxygen-rich blood from the lungs directly into the left atrium, where it can then be pumped to the body through the aorta. Surgeons achieve this by creating a new connection between the pulmonary veins and the left atrium, then closing off the abnormal venous pathway that had been carrying blood to the wrong destination. Surgical reconnection principle: the operation essentially rewires the pulmonary venous return so it follows normal anatomy, allowing the heart's left side to fill properly and deliver oxygenated blood to the body.
The procedure requires open-heart surgery with cardiopulmonary bypass, meaning the patient's blood is circulated through a heart-lung machine while the surgeon works on a still heart. An arterial cannula is placed to maintain circulation, and the ascending aorta is clamped to create a bloodless surgical field. In some cases, deep hypothermic circulatory arrest may be used — cooling the body to very low temperatures to reduce metabolic demand and protect the brain while circulation is briefly stopped. These techniques allow the surgeon to perform the delicate anastomosis — the surgical joining — between the pulmonary veins and the left atrium with precision.
Families often ask what the surgeon actually does inside the chest. The specific approach varies with the type of TAPVR: supracardiac, cardiac, infracardiac, or mixed. In each variant, the principle is the same — identify where the pulmonary veins currently drain, create an opening into the left atrium, connect the veins to that opening, and ligate or divide the abnormal drainage channel. The technical details are intricate, but the concept is straightforward: restore normal blood flow from lungs to left heart to body. Ongoing research continues to refine surgical techniques and outcomes, with some centers participating in studies registered on clinicaltrials.gov.
Types of TAPVR and Their Surgical Approach
Total anomalous pulmonary venous drainage is classified into four anatomical types, each defined by where the pulmonary veins drain instead of the left atrium. The surgical approach must be tailored to the specific drainage pattern identified on preoperative imaging. Understanding these types helps families grasp why the operation differs from child to child.
- Supracardiac TAPVR: the pulmonary veins join a vertical vein that drains upward into the superior vena cava or innominate vein — the most common form.
- Cardiac TAPVR: the pulmonary veins drain directly into the coronary sinus or right atrium, requiring redirection within the heart itself.
- Infracardiac TAPVR: the pulmonary veins converge into a descending vein that passes through the diaphragm to drain into the portal or hepatic venous system — frequently obstructed and the most urgent.
- Mixed TAPVR: pulmonary veins drain to two or more different locations, making the repair more complex and highly individualized.
The supracardiac form accounts for roughly half of cases. The surgeon opens the left atrium and creates a wide anastomosis between the posterior left atrium and the confluence of pulmonary veins, then divides the vertical vein to eliminate the abnormal drainage. For cardiac TAPVR, the surgeon may re-route blood from the coronary sinus into the left atrium through an intra-atrial baffle — a patch that channels flow in the correct direction. Each type requires a different incision plan and different structural modifications, which is why preoperative echocardiography and sometimes cardiac MRI are essential for mapping the exact anatomy before surgery begins.
TAPVR Repair Procedure Steps
Understanding the step-by-step flow of TAPVR repair can demystify what happens in the operating room and help families feel more prepared. The procedure follows a logical sequence that begins with preparation and ends with verifying that blood flows through the corrected pathway.
Preparation and access: the surgeon makes an incision through the sternum to access the heart. Cannulas are placed for cardiopulmonary bypass — one in the right atrium or vena cava to drain blood out, and an arterial line to return oxygenated blood to the body. The heart-lung machine takes over circulation, and the aorta is clamped to stop blood flow through the heart. A cardioplegia solution is delivered to arrest the heart in diastole, protecting the myocardium during the repair.
Creating the anastomosis: the surgeon identifies the pulmonary venous confluence — the collecting chamber where the pulmonary veins merge. An incision is made in the back wall of the left atrium, matching it to the opening of the venous confluence. The two are sewn together, creating a direct pathway from the pulmonary veins into the left atrium. The abnormal drainage channel — whether a vertical vein, the coronary sinus, or a descending vein — is then ligated or divided to prevent continued flow into the wrong location.
Completing the repair: any atrial septal defect is closed, the heart is de-aired, and the aortic clamp is removed. The heart resumes beating, and the team gradually weans the patient off cardiopulmonary bypass. Transesophageal echocardiography is used in the operating room to confirm that pulmonary venous blood now flows into the left atrium without obstruction. The chest is typically left open initially in newborns with obstructed TAPVR and closed in a second procedure days later, allowing time for the heart to recover from acute distension.
TAPVR Repair Recovery Timeline
Recovery after TAPVR repair unfolds in stages, beginning in the cardiac intensive care unit and progressing to home over weeks to months. The timeline varies with the child's age at surgery, the presence of obstruction before repair, and any associated cardiac defects. ICU phase (days 1–5): the child remains intubated and on a ventilator initially, with continuous monitoring of heart rhythm, oxygen saturation, and venous pressures. Medications support heart function, control pain, and manage fluid balance.
Once the child is stable — typically within the first several days — the team begins reducing ventilator support and intravenous medications. Chest tubes placed during surgery drain residual fluid and are removed as output decreases. Feeding usually starts through a nasogastric tube and transitions to oral feeds as the child recovers. Step-down and ward phase (days 5–14): the focus shifts to weight gain, feeding tolerance, and wound healing. Parents are encouraged to participate in care — changing diapers, holding the child, and learning medication schedules — to build confidence before discharge.
Most children go home one to two weeks after an uncomplicated repair, though those with obstructed TAPVR or associated defects may stay longer. Discharge planning includes echocardiographic follow-up, wound care instructions, and signs to watch for at home. The first outpatient echo is typically scheduled within a week or two of discharge. Full recovery — return to normal activity and feeding patterns — usually takes several weeks, with the sternum healing over six to eight weeks. Parents should avoid lifting the child under the arms during this period to protect the sternal incision.
Risks and Complications of TAPVR Repair
All cardiac surgery carries risk, and TAPVR repair is no exception. Being informed about potential complications does not mean they are likely — it means families can recognize problems early and understand what the surgical team is monitoring for. The risk profile depends on the child's condition at the time of surgery, the anatomical type of TAPVR, and whether pulmonary venous obstruction is present.
Pulmonary venous obstruction: the most significant concern after repair is narrowing of the anastomosis between the pulmonary veins and the left atrium. This stenosis can develop weeks to months after surgery and may require reoperation or catheter-based interventions. Regular echocardiographic surveillance detects this early. Arrhythmias: manipulation of atrial tissue can cause rhythm disturbances such as atrial flutter, which may require medication or, rarely, catheter ablation. Low cardiac output: the heart may need time to adapt to the new volume load on the left side, and inotropic medications support this transition.
Other risks include bleeding requiring re-exploration, infection at the sternal wound, phrenic nerve injury affecting breathing, and the general risks of cardiopulmonary bypass including stroke or kidney injury. Children with obstructed infracardiac TAPVR face higher perioperative risk because their lungs have been subjected to high pressure before surgery. The surgical team will discuss the specific risk profile based on the individual child's anatomy and condition. No surgery is without risk, but delaying repair of an obstructed lesion carries far greater danger, which is why urgent intervention is recommended in those cases.
TAPVR Surgical Outcomes and Prognosis
Outcomes after TAPVR repair have improved significantly over recent decades, driven by advances in surgical technique, neonatal intensive care, and postoperative monitoring. Most children who undergo uncomplicated repair in infancy go on to live healthy, active lives with normal heart function. The key predictor of long-term outcome is whether pulmonary venous obstruction develops after the initial repair.
Children without postoperative venous obstruction typically require no further surgery and are followed with periodic echocardiograms. Those who develop anastomotic stenosis face a more complex course, sometimes requiring multiple reoperations or catheter interventions. The literature on this topic continues to evolve, and case reports such as one documenting Total Anomalous Pulmonary Venous Drainage contribute to the understanding of varied presentations and management strategies.
Long-term follow-up addresses not only cardiac function but also growth, neurodevelopment, and quality of life. Most repaired children attend normal schools and participate in typical activities, though competitive sports may need individualized assessment. The psychological impact on families is also an important consideration — many parents benefit from connecting with support networks or counseling. The surgical team will outline expected follow-up schedule and milestones specific to each child's situation, emphasizing that every patient's journey is unique.
When Is TAPVR Repair Urgent
The urgency of TAPVR repair depends primarily on whether the abnormal venous drainage is obstructed. Obstruction — most commonly seen in infracardiac TAPVR — prevents blood from leaving the lungs, causing pulmonary congestion and severe oxygen deprivation. This is a life-threatening situation that requires surgical intervention within hours of diagnosis. Obstructed TAPVR signs: profound cyanosis unresponsive to oxygen, rapid respiratory distress, and metabolic acidosis visible on blood tests within the first day of life.
In these cases, the child is stabilized with prostaglandin infusion to maintain ductal patency, mechanical ventilation, and correction of acid-base balance, then taken to surgery as quickly as possible. There is no role for delayed repair when obstruction is present — the condition will not improve on its own. Some unusual presentations have been documented in the literature, including an incidental finding of supra cardiac total anomalous pulmonary venous connection with Tetralogy of Fallot, demonstrating that TAPVR can sometimes coexist with other defects and be discovered unexpectedly during evaluation for a different condition.
Unobstructed TAPVR, while still requiring surgery, allows for a more planned approach. These children have an atrial septal defect that permits mixing of blood, maintaining adequate — though not normal — oxygen levels. Surgery is typically scheduled within the first weeks of life rather than emergently. The distinction between obstructed and unobstructed forms is made on echocardiography and determines the entire clinical pathway, from timing of surgery to preoperative stabilization strategy.
TAPVR Repair Considerations in Mexico
For families considering cardiac surgery in Mexico, several practical factors shape the experience. Families traveling from outside these cities — or from abroad — need to plan for preoperative consultation, the hospital stay, and postoperative follow-up.
Preoperative evaluation: a thorough assessment includes echocardiography, review of any prior imaging, and discussion of surgical approach. Families should bring all available medical records, imaging studies, and a complete list of medications. Logistics and accommodation: families may need to stay near the hospital for the duration of the child's admission and initial recovery. The team can provide guidance on nearby accommodations and approximate length of stay. Insurance and cost discussion: every case is unique, and costs depend on the complexity of the repair, length of ICU stay, and any associated anomalies. These details should be discussed directly with the practice during consultation.

Choosing where to have congenital heart surgery is one of the most important decisions a family will make. The right team combines surgical expertise, dedicated pediatric cardiac intensive care, and a commitment to clear communication with anxious families. Families should ask the treating team about their child's specific anatomy, the surgical plan, and the expected recovery process. Self-diagnosis is never appropriate for a condition this complex — a qualified cardiac team must evaluate each case individually.
Life After TAPVR Repair: Long-Term Outlook
Most children who undergo successful TAPVR repair grow up with hearts that function normally or near-normally. The pulmonary veins, once reconnected to the left atrium, typically maintain good flow long-term, allowing the heart to pump oxygenated blood efficiently to the body. Growth and development: repaired children usually follow normal growth curves and reach developmental milestones on schedule. Some may have been behind before surgery due to their heart condition and catch up rapidly after repair.
Ongoing cardiology follow-up is essential, even in children who feel well. Echocardiograms monitor the pulmonary venous anastomosis for any sign of narrowing, and the cardiologist checks heart rhythm and function at each visit. The frequency of visits decreases over time — typically annually after the first few years if everything remains stable. Any new symptoms such as exercise intolerance, palpitations, or breathing changes should prompt evaluation rather than waiting for a scheduled appointment.
Families often wonder whether their child will need restrictions. In most cases, repaired children can participate fully in school, sports, and normal activities. The goal of surgery is not just survival but a full life. Some children may require a prophylactic aspirin regimen or other medications for a period, and scar tissue from the sternal incision will fade over time. The long-term outlook is best understood as a partnership between the family, the cardiologist, and the surgical team — each playing a role in monitoring and supporting the child's heart health for years to come. We encourage every family to maintain that relationship and to bring any concerns to their cardiac team rather than navigating this journey alone.