

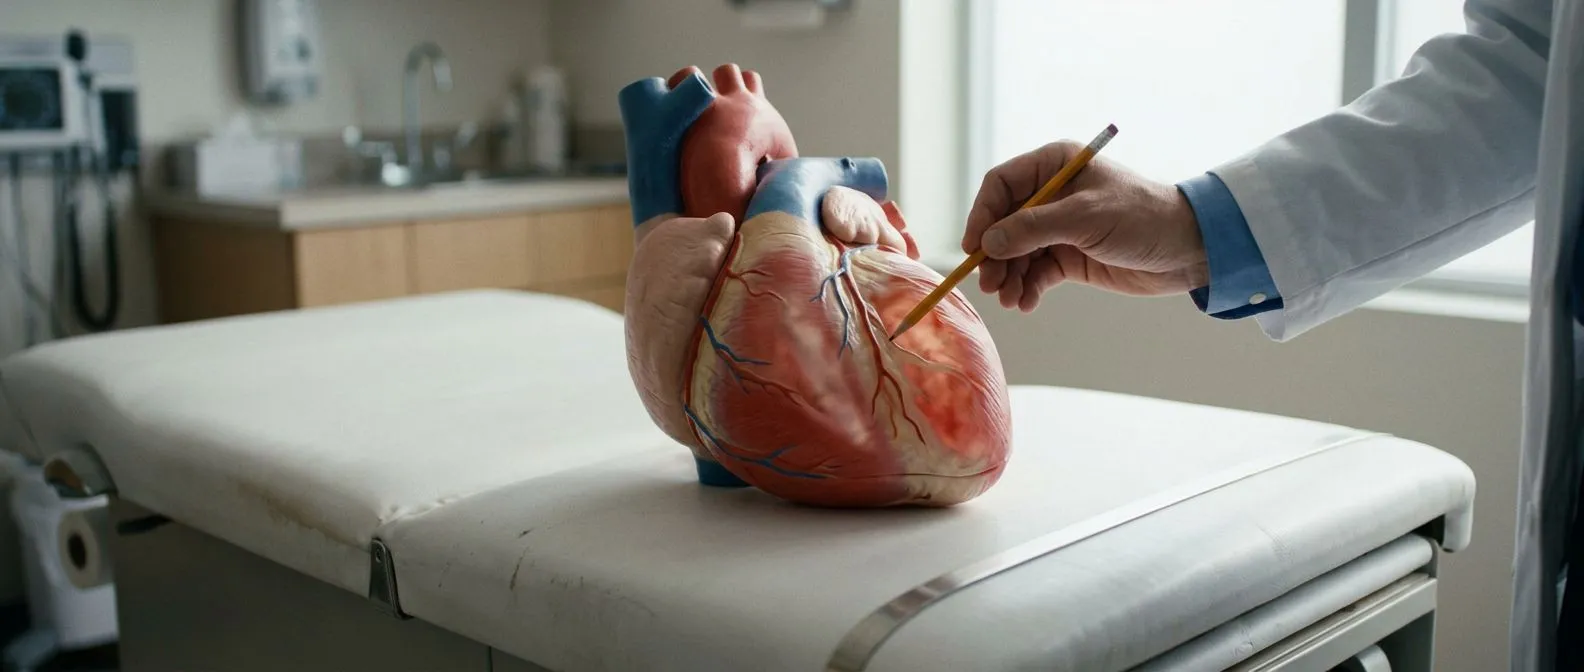
Ventricular Dilatation: When the Heart Enlarges
Ventricular dilatation causes explained by heart specialists.
Learning that a heart chamber has grown larger than it should be is frightening, especially when you have never heard the term before. Understanding ventricular dilatation causes is the first step toward taking control of the situation, because an enlarged ventricle is almost always a sign of something else that can be found and treated. This guide walks through what the condition means, why it happens, how it is detected, and what the realistic treatment options are — including when surgery or a catheter-based procedure enters the picture.
What Is Ventricular Dilation?
Ventricular dilation is the medical description of a heart chamber that has stretched beyond its normal size. The heart has four chambers; the two lower chambers, the ventricles, do the heavy pumping work. The left ventricle pushes blood to the whole body, while the right ventricle sends blood to the lungs. When either chamber enlarges, its walls stretch and thin, and the muscle becomes less efficient at squeezing blood forward.
Think of a balloon that has been inflated many times. It holds more air but the rubber is weaker, and it no longer springs back the way it used to. A dilated ventricle behaves similarly. It may hold more blood, but each contraction moves less blood out with real force, which is why ventricular dilation heart failure often develops slowly over months or years as the chamber struggles to keep up.
Dilation is different from hypertrophy, where the heart wall thickens. In ventricular dilatation cardiomyopathy, the walls are often thin and the chamber is round rather than its usual oval shape. Both changes can coexist, and doctors use measurements from an echocardiogram — an ultrasound scan of the heart — to tell them apart and decide what is driving the enlargement.
What Causes Ventricular Dilatation?
The most common causes fall into two broad groups: conditions that make the heart work against too much pressure, and conditions that make it pump too much volume, or blood, around. A leaky or narrowed valve forces the ventricle to handle extra blood with every beat. High blood pressure forces it to push against stiff arteries. Over time, either workload stretches the chamber.
Other causes include damage from a previous heart attack, where part of the muscle is replaced by scar tissue that cannot contract and stretches under load. Viral infections of the heart muscle — myocarditis — can leave it weakened. Alcohol excess, certain chemotherapy drugs, thyroid disease, and inherited genetic conditions all play a role too.
- Volume overload: leaky valves (especially the mitral or aortic valve), severe anemia, or abnormal connections between vessels flood the ventricle with extra blood.
- Pressure overload: long-standing hypertension, narrowed valves, or lung disease force the ventricle to push against resistance.
- Muscle injury: heart attacks, myocarditis, toxins, and genetic disease damage the muscle itself, so it stretches under normal load.
In our practice, every case is reviewed by the multidisciplinary team against international practice guidelines before a recommendation is given, because the underlying cause determines the whole treatment plan — a valve problem, a rhythm problem, and a muscle problem each need a different approach.
Left Ventricular Dilatation Causes
Left ventricular dilatation causes are the ones most patients encounter, because the left ventricle bears the greatest workload. The most frequent culprit is coronary artery disease: when a heart attack damages part of the muscle, the remaining muscle stretches to compensate. Aortic valve regurgitation — a valve that leaks blood backward into the ventricle with every heartbeat — is another classic cause, as is mitral regurgitation.
Uncontrolled hypertension deserves special mention. Years of high blood pressure first thicken the wall, then, when the muscle can no longer cope, the chamber begins to dilate. This progression is why blood pressure control is one of the most powerful forms of ventricular enlargement prevention available to anyone.
Dilated cardiomyopathy, often genetic or idiopathic (meaning no clear cause is found), is another major pathway. Researchers have linked many cases to mutations in genes that build the heart's structural proteins. A landmark analysis of global causes of death published in The Lancet underscores how heavily cardiovascular disease contributes to worldwide mortality, which is precisely why identifying an enlarged ventricle early matters so much.
Our work covers valve disease, coronary disease, the aorta and structural heart conditions, and we recommend the less invasive route only where the evidence supports it for that patient — a principle that applies just as much to deciding on surgery for a dilated left ventricle as to anything else we treat.
What Causes Right Ventricular Dilatation?
Right ventricular dilatation causes are a different family of problems. The right ventricle is a thin-walled, low-pressure pump, and it enlarges mainly when the lungs or the connections between the lungs and heart make its job harder. Pulmonary hypertension — high pressure in the lung arteries — is the leading cause. Congenital (present from birth) abnormalities of the pulmonary valve, or of the arrangement of the heart itself, can also produce it.
Arrhythmogenic right ventricular cardiomyopathy is a rarer, inherited condition where muscle is gradually replaced by fat and fibrous tissue. It can cause dangerous rhythm disturbances and deserves specialist attention. Chronic clots in the lung arteries (chronic thromboembolic disease) and severe lung disease such as COPD are further contributors.
Distinguishing which of these is at work is a genuine diagnostic puzzle — so much so that imaging specialists have written extensively about the echocardiographic differential diagnosis of right ventricular enlargement. The pattern of wall motion, the shape of the chamber, and the direction of the septum (the wall between the ventricles) each give clues that point toward one cause or another.
Ventricular Dilatation Symptoms
Early ventricular dilatation symptoms are often subtle, which is exactly why the condition can go unnoticed for years. The first complaints tend to be fatigue during activity that used to be easy, a sensation of breathlessness climbing stairs, or a vague awareness of the heartbeat. As the ventricle stretches further, blood backs up and the symptoms grow more concrete.
What is right-sided heart failure and what are its symptoms? When the right ventricle fails, blood backs up in the veins returning from the body. Patients notice swelling of the ankles and legs, abdominal fullness, an enlarged liver, and weight gain from fluid. When the left ventricle fails, fluid backs up into the lungs, producing breathlessness when lying flat, waking at night gasping, and a cough with frothy sputum.
What causes fluid retention in heart failure? The failing heart cannot pump forward adequately, so the kidneys perceive lower blood flow and retain salt and water, trying to boost volume. That retained fluid then leaks into tissues and the lungs. This is why diuretics — "water pills" — are a cornerstone of heart failure treatment: they help the body release the excess fluid while the underlying problem is addressed.
If you experience new breathlessness, leg swelling, or palpitations, seek medical assessment rather than waiting for it to resolve. Rhythm disturbances such as Ventricular Tachycardia can arise in a dilated ventricle and sometimes announce themselves before other symptoms do.
Ventricular Dilatation and Cardiomyopathy
Dilated cardiomyopathy is the formal name for the condition in which a ventricle is dilated and the muscle contracts weakly, with no valve disease or coronary blockage to explain it. It can be inherited, triggered by a virus, linked to alcohol or certain medications, or appear during or after pregnancy in a small number of women (peripartum cardiomyopathy).
Is it the same as an enlarged heart? Not quite. "Cardiomegaly" is the umbrella term for any enlarged heart seen on a chest X-ray, and it can reflect thickening, dilation, or fluid around the heart. Dilated cardiomyopathy specifically describes stretched, weakened ventricles. The distinction matters because the outlook and treatment differ — what is the life expectancy of someone with cardiomegaly? depends entirely on the underlying cause, how early it is caught, and how well it responds to therapy, so no single answer exists.
Can you live a long life with an enlarged heart? Many people can, particularly when the cause is treatable — a correctable valve, controlled blood pressure, or cardiomyopathy that responds well to modern medications. In our consultation we take the time to explain what the studies actually show, in plain words, and to answer every question before any decision, because an honest picture of prognosis is the foundation of a good decision.
We encourage second opinions and treat seeking one as a normal part of deciding about heart surgery — a dilated ventricle with a weak pump is precisely the kind of situation where a second view of the evidence helps.
Dilated Ventricle Risk Factors
Dilated ventricle risk factors overlap heavily with general cardiovascular risk, and knowing them lets you act before enlargement begins. Some risks you cannot change — family history, age, and certain genetic conditions. Many others you can.
- Blood pressure: sustained hypertension is the single most common driver of heart enlargement worldwide.
- Coronary disease: prior heart attacks leave scarred muscle that stretches.
- Valve disease: a leaking aortic or mitral valve quietly overloads the ventricle for years.
- Alcohol and drugs: heavy drinking and some chemotherapy agents directly injure heart muscle.
- Sleep apnea and lung disease: these strain the right ventricle specifically.
Acquired versus inherited. Most ventricular enlargement in adults is acquired — built up over decades of pressure, valve leak, or muscle injury. Congenital ventricular dilatation is present from birth, whether from an abnormal valve, a shunt (a hole letting blood flow where it should not), or a primary muscle condition. Adults with congenital heart disease need lifelong surveillance of their right ventricle in particular, and dedicated imaging follows the chamber's size and function over time.
Recognizing risk early is the quiet win here. A patient whose blood pressure is controlled, whose valve leak is monitored and repaired at the right moment, and who drinks moderately has substantially reduced their chances of ever meeting this condition in the first place.
How Is Ventricular Dilatation Diagnosed?
The echocardiogram is the workhorse test. It is painless, uses no radiation, and measures the chamber dimensions, wall thickness, and pumping function — the ejection fraction, which is the percentage of blood the left ventricle pushes out with each beat. A normal value is roughly 50% or higher; lower numbers signal a weakened pump.
Additional tests complete the picture. An electrocardiogram detects rhythm problems and signs of past injury. Cardiac MRI gives the most precise measurement of ventricular volumes and can identify scar tissue, inflammation, or the fatty replacement seen in some inherited conditions. Blood tests check thyroid function, iron levels, and markers of heart strain. In selected patients, a coronary angiogram — a dye study of the heart arteries — establishes whether coronary disease is the driver.
The first contact with our team is a free video consultation: we get to know the patient, talk through the condition, and say which studies are still needed so no unnecessary ones are ordered — a face-to-face visit at the consulting rooms follows when the patient decides to go ahead.
One warning worth passing on: in a dilated ventricle, the heart's electrical system can be unstable, and some studies of patients with chest pain and structurally normal-ish hearts have shown how intraventricular pressure gradients — differences in pressure within the chamber itself — can provoke ischemia and rhythm trouble during exercise, as documented in research published in Cardiovascular Ultrasound. This is why exercise testing is sometimes done carefully, with continuous monitoring, rather than casually.
Ventricular Dilatation Treatment
Ventricular dilatation treatment always begins with the cause. If a leaky valve is stretching the ventricle, repairing or replacing that valve can halt and sometimes improve the dilation. If coronary disease is the problem, opening or bypassing the blocked arteries protects the remaining muscle. If it is cardiomyopathy, modern medication regimens reduce the workload and help the muscle recover function.
Medications used for the dilated, weak ventricle include ACE inhibitors or ARBs (which lower the pressure the heart pumps against), beta-blockers (which slow the heart and reduce strain), aldosterone antagonists, and newer agents such as SGLT2 inhibitors. These drugs, used together and adjusted over time, have genuinely changed the trajectory of heart failure. Diuretics manage fluid retention but do not treat the muscle itself.
When does surgery or a device come in? If the cause is a valve, surgical repair — conventional through the breastbone, minimally invasive, robotic, or transcatheter — is considered once the evidence supports operating, ideally before the ventricle has dilated too far. For rhythm risk, an implantable defibrillator may be recommended. In advanced cases, mechanical circulatory support such as a Left Ventricular Assist Device can bridge patients to transplantation or serve as long-term therapy. Ventricular Septal Defect, a hole between the ventricles, is another structural cause that surgical closure can address before dilation becomes irreversible.
Dr Molina trained in cardiac, minimally invasive, robotic and structural surgery at the University of Montreal and in structural cardiology and TAVR at CHU Bordeaux, and he performed the first robotic mitral valve repair in the Ángeles Health System — experience we bring to choosing the lowest-risk approach for each patient's specific anatomy.

Can an Enlarged Ventricle Be Reversed?
Can an enlarged right ventricle be reversed? Sometimes, yes — and the left ventricle too — but the honest answer depends on cause and timing. When the driver is removed early enough: a severely leaky valve is repaired, blood pressure is brought under control, alcohol is stopped, or a reversible toxin is eliminated, ventricular function often improves measurably. Cardiologists call this "reverse remodeling," and it is a well-documented phenomenon.
Timing is everything. A ventricle that has been dilated for years, with walls that are thin and muscle that is heavily scarred, rarely returns to normal even after excellent treatment. That is the argument for acting at the stage when the chamber is only mildly enlarged — the window in which reversal is realistic rather than hopeful.
What helps recovery along? Consistent medication use, controlled blood pressure, moderate activity as advised by your cardiologist, limiting salt and alcohol, and treating sleep apnea all support the remodeling process. Cardiac rehabilitation programs — supervised exercise and education after a cardiac event or diagnosis — have solid evidence behind them. Resources such as Johns Hopkins Medicine offer accessible patient education on dilated cardiomyopathy and heart function that can supplement what your own team explains.
In the consultation we take the time to explain what the studies actually show, in plain words, and to answer every question before any decision — including the honest question of whether your particular ventricle is likely to recover or needs a structural fix.
When to Seek Help for an Enlarged Heart
Red-flag symptoms demand urgent attention. Breathlessness at rest or when lying flat, fainting, chest pain, rapid pounding palpitations, or sudden weight gain of several pounds in days from fluid retention — any of these warrants same-week evaluation, and fainting or chest pain warrants emergency care.
Early, non-urgent signs still matter. If you have a family history of cardiomyopathy or sudden cardiac death, a known heart murmur, long-standing hypertension, or a history of a heart attack, ask your doctor whether a baseline echocardiogram makes sense for you. It is a simple test that answers the enlargement question directly.
Our multidisciplinary team of cardiac surgeons, led by Dr Alejandro Molina, reviews every case together against international practice guidelines, and the patient receives a clear proposal with the alternatives — the final decision is always theirs.

Conclusion: Understanding Ventricular Dilatation Causes
An enlarged ventricle is a signal, not a sentence. The ventricular dilatation causes that matter most — leaky valves, blocked coronary arteries, uncontrolled blood pressure, and muscle disease — are conditions we can identify, and many of them we can treat effectively, sometimes before the heart has lost the ability to recover. The key is catching the enlargement early, treating the cause rather than just the symptoms, and choosing the least invasive option that the evidence supports for your specific situation.
If you or a family member has been told the heart is enlarged, or if the symptoms described here sound familiar, the most useful next step is a conversation with a qualified cardiac team rather than self-diagnosis. Bring your existing studies, ask what the measurements actually mean, and ask what the treatment options would be — and whether a second opinion would help you decide. We are glad to talk through any of it in a free video consultation before any commitment is made.






